
This page provides general information for patients of Dr Borshch, an orthopaedic surgeon consulting in Hamilton, Brisbane, who are being assessed for or considering ACL reconstruction surgery. If you have injured your knee playing sport and it now feels unstable, seeing a knee surgeon in Brisbane can clarify whether reconstruction or rehabilitation alone is the better path for you.
Your individual injury and treatment plan may be different, so this information should be used alongside advice from your surgeon and treating team.
What is ACL Reconstruction Surgery?
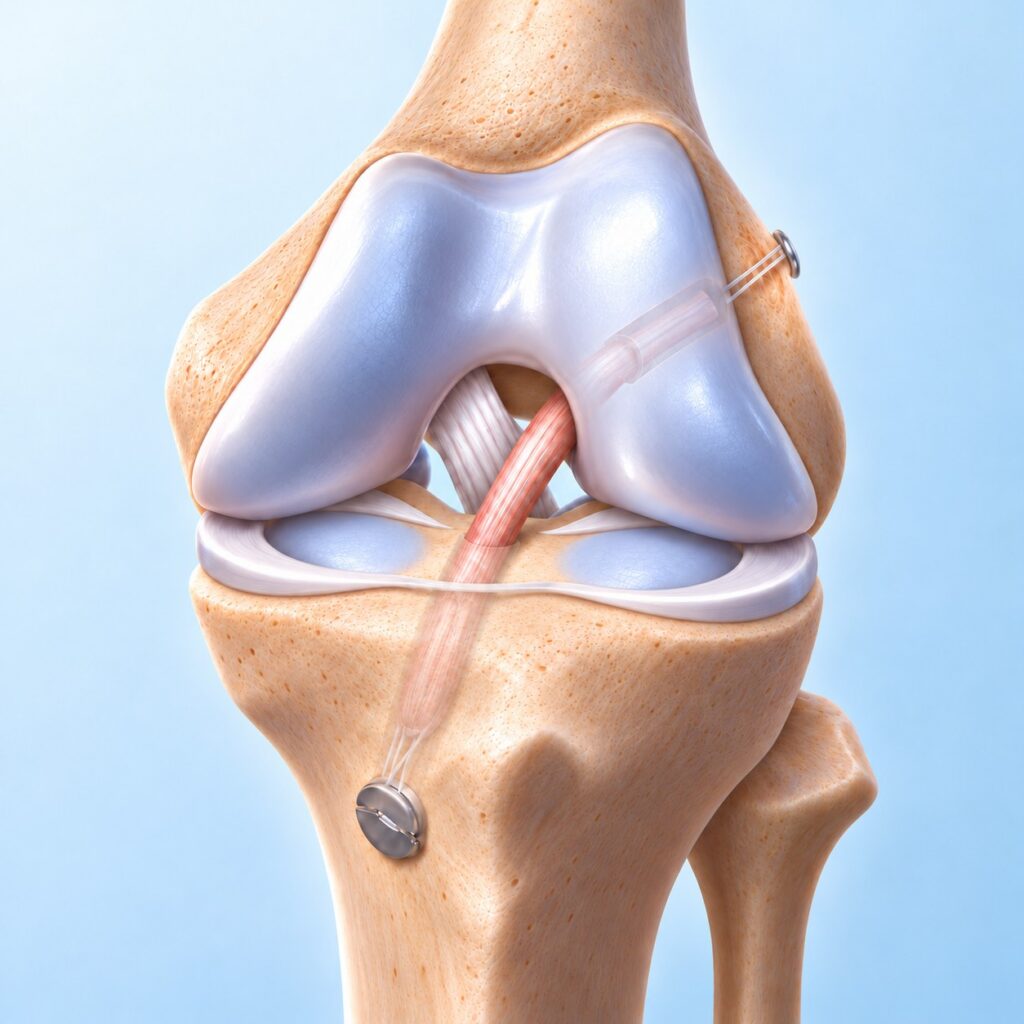
The anterior cruciate ligament (ACL) is one of the major stabilising ligaments inside the knee.
It connects the femur (thigh bone) to the tibia (shin bone) and helps control forward movement and rotation of the knee.
ACL injuries commonly occur during activities involving:
- sudden changes of direction
- pivoting
- landing from a jump
- rapid deceleration
- awkward twisting of the knee
- direct contact or collision
Some patients describe hearing or feeling a “pop”, followed by pain and rapid swelling. Others have relatively little pain once the initial injury settles but subsequently notice that the knee feels unstable or unexpectedly “gives way.”
An ACL tear does not automatically require surgery.
Some patients can return to their desired activities with structured rehabilitation alone.
When surgery is required, the usual operation is an ACL reconstruction. Rather than simply stitching the damaged ACL back together, a tendon graft is used to create a new ligament.
Over the following months, the body gradually remodels the tendon graft into tissue that resembles a normal ligament. This process is called ligamentisation (PMID 21515806).
The aim is to restore knee stability and allow the patient to return to appropriate everyday, recreational and sporting activities.
ACL reconstruction is a common knee operation in Australia. National hospital data recorded 197,557 primary ACL reconstructions between 2000 and 2015, and the yearly rate rose by 43% over that time, with the largest increase in people younger than 25 (PMID 29669497).
Why is ACL Reconstruction Surgery Done?

The decision to undergo ACL reconstruction depends on considerably more than the appearance of the ACL on an MRI scan. A thorough clinical examination by a specialist and modern imaging helps confirm the diagnosis and shows any associated meniscus, cartilage or other ligament injury.
Surgery may be considered when there is:
- recurrent giving way or symptomatic instability
- a desire to return to sports or activities involving pivoting, cutting or rapid changes of direction
- instability affecting work or everyday activities
- associated meniscus or cartilage injury
- another ligament injury contributing to knee instability
- failure to achieve acceptable stability and function despite appropriate rehabilitation
Does every ACL tear need surgery?
No.
In a randomised trial of young, active adults with acute ACL tears, early ACL reconstruction was not superior at two years to structured rehabilitation with the option of later reconstruction. The rehabilitation-first strategy also substantially reduced the number of reconstructions performed (PMID 20660401).
At five years, the same trial again found no difference in patient-reported outcomes between early reconstruction and initial rehabilitation with the option of later surgery (PMID 23349407).
However, these results do not mean that surgery is unnecessary for everyone.
Some patients continue to experience instability despite rehabilitation, while others have sporting, occupational or associated knee injuries that make reconstruction more appropriate.
Why does instability matter?
Repeated episodes of the knee giving way can interfere with sport, work and everyday activities.
There is also concern that recurrent instability can expose the meniscus and cartilage to additional injury. A systematic review found preliminary evidence that repeated episodes of giving way may be associated with increased odds of damage to the medial meniscus (PMID 30057927).
The objective of ACL reconstruction is therefore not simply to make an MRI look normal. It is to provide functional stability to a knee that requires it.
How is ACL Reconstruction Surgery Performed?

ACL reconstruction is a minimally invasive operation. It is performed using arthroscopy (keyhole surgery) together with small additional incisions.
Anaesthetic
The operation is performed under anaesthetic, which your anaesthetist will discuss with you. Local anaesthetic or nerve blocks may also be used to help with pain relief.
Arthroscopy
A small camera is inserted into the knee.
This allows the joint to be carefully assessed, including:
- the ACL
- the menisci
- the cartilage surfaces
- other structures within the knee
Associated injuries can often be treated during the same operation.
Meniscus injuries
Meniscus tears frequently occur together with ACL injuries.
When a meniscus tear is suitable for repair, I generally prefer to preserve and repair the meniscus rather than remove it where reasonably possible.
Preserving meniscal tissue is important because the meniscus distributes load across the knee and contributes to joint stability. In a meta-analysis of meniscal repairs performed with ACL reconstruction, tears near the outer edge of the meniscus, which has a better blood supply, were 2.5 times more likely to heal than tears further in (PMID 35072757).
Choosing the ACL graft
The torn ACL is reconstructed using a graft.
Common graft options include:
Each has potential advantages and disadvantages.
Patellar tendon grafts provide strong bone-to-bone fixation but can be associated with pain at the front of the knee or discomfort when kneeling.
Hamstring grafts avoid the patellar tendon but can affect hamstring strength and have their own graft-specific considerations.
Quadriceps tendon grafts provide another strong autograft option and are increasingly used in ACL reconstruction.
A systematic review and meta-analysis comparing quadriceps tendon with hamstring and patellar tendon grafts found comparable graft survival, function and stability, with fewer donor-site problems after quadriceps tendon grafts (PMID 34494906).
There is therefore no single graft that is ideal for every patient.
I consider age, sporting activity, occupation, kneeling requirements, previous surgery, associated injuries and individual anatomy when discussing graft choice.
Creating the new ACL
Small tunnels are created in the tibia and femur at the attachment sites of the ACL.
The graft is passed through these tunnels and secured using specialised fixation devices.
The position and tension of the graft are checked before completing the procedure.
Additional stabilisation procedures
Some patients have a greater degree of rotational instability or particular risk factors for recurrent ACL injury.
In selected patients, an additional procedure on the outside of the knee, such as a lateral extra-articular tenodesis (LET), may be performed together with ACL reconstruction.
This is not required for every ACL reconstruction.
In the STABILITY randomised trial of young patients at increased risk of graft failure, adding a lateral extra-articular tenodesis to a hamstring ACL reconstruction significantly reduced graft rupture and persistent rotational instability at two years (PMID 31940222).
The decision to add an extra-articular procedure is therefore based on the individual patient's instability pattern and risk factors, rather than being routinely required for every ACL reconstruction.
Closing the knee
Once the reconstruction and any associated procedures are complete, the incisions are closed and dressings are applied.
What are the benefits of ACL reconstruction?
For appropriately selected patients, ACL reconstruction restores stability to the knee and helps many people return to sport.
ACL reconstruction restores the stability of the knee. A meta-analysis of studies with more than five years of follow-up found that patients who had a reconstruction had better objective knee function and needed fewer later meniscectomies (operations to remove torn meniscus) than patients treated without surgery (PMID 34929763).
Most people return to sport. In a systematic review and meta-analysis of 69 studies including 7,556 participants, 81% of people returned to some form of sport after ACL reconstruction and 65% returned to their pre-injury level of sport (PMID 25157180).
The operation also gives an opportunity to repair an associated meniscus tear. In a meta-analysis of 758 meniscal repairs performed at the same time as ACL reconstruction, 78% of the repairs healed (PMID 35072757).
What are the risks of ACL reconstruction?

Most patients do well, but complications can happen, and a reconstructed knee is not necessarily the same as a knee that has never been injured.
Another ACL injury. The new graft can tear, and the ACL in the other knee can also be injured. A meta-analysis found an overall second ACL injury rate of 15% (7% in the reconstructed knee and 8% in the other knee), rising to 23% in athletes younger than 25 who returned to sport (PMID 26772611). A torn graft may need a revision ACL reconstruction.
Not returning to the same level. Not everyone returns to their previous sport or level. In the review described above, 55% of people returned to competitive-level sport (PMID 25157180).
Arthritis. ACL reconstruction has not been shown to prevent arthritis. A meta-analysis found no difference in the development of knee osteoarthritis, in patient-reported knee scores or in activity level at five and ten years compared with non-operative treatment (PMID 34929763). Meniscus and cartilage injuries at the time of reconstruction, and removal of meniscus, increase the risk of later knee osteoarthritis (PMID 41521732).
Infection. Infection is uncommon but serious. A meta-analysis of 469,441 ACL reconstructions found a surgical-site infection rate of approximately 1%, with symptoms starting on average about 17 days after surgery. Hamstring grafts, smoking, diabetes and obesity were among the factors linked with a higher risk (PMID 36517215).
Stiffness. Some knees lose movement after surgery because of scar tissue (arthrofibrosis). In a meta-analysis of 46 studies, 4% of patients needed a further operation to treat loss of knee movement (PMID 41242397).
Blood clots. A clot can form in the deep veins of the leg (deep vein thrombosis) or travel to the lungs (pulmonary embolism). In a database study of 11,977 patients, 1.22% had a symptomatic clot within 90 days of surgery (PMID 33970293). English national data showed rates of 0.30% for deep vein thrombosis and 0.18% for pulmonary embolism within 90 days (PMID 21216599).
Graft harvest site. Taking the graft can cause symptoms where the tendon was harvested, such as pain at the front of the knee or with kneeling. Donor-site problems were more common after patellar tendon and hamstring grafts than after quadriceps tendon grafts (PMID 34494906).
Preparing for ACL Reconstruction Surgery in Brisbane

ACL reconstruction is usually not an emergency operation.
This provides an opportunity to prepare the knee and the rest of the body before surgery.
Rehabilitation before surgery
I generally encourage patients to undergo pre-operative rehabilitation or “prehabilitation” before ACL reconstruction.
The goals include:
- reducing swelling
- regaining full knee extension
- restoring knee movement
- improving quadriceps strength
- improving walking
- preparing for postoperative rehabilitation
Operating on a very swollen and stiff knee can make postoperative rehabilitation more difficult.
A review found that 4–6 weeks of prehabilitation before surgery can improve early to mid-term strength and knee movement, and can improve the timing and likelihood of returning to sport (PMID 35141537).
Health preparation
Before surgery:
- stop smoking or vaping if possible
- maintain good nutrition
- maintain general fitness where possible
- tell us about medications and supplements
- tell us about previous blood clots or anaesthetic problems
- optimise other medical conditions
- arrange physiotherapy for postoperative rehabilitation
Preparing your home
Arrange transport and some assistance during the first few days after surgery.
Remove obvious trip hazards and make sure commonly used items are easy to access.
Because Brisbane has a warm and humid climate, particularly during summer, consider making sure you have access to a cool, comfortable and preferably air-conditioned environment during early recovery. Apart from making recovery more comfortable, a large meta-analysis found an association between warmer weather and higher rates of surgical-site infection (PMID 34422523). Keeping yourself comfortable and your surgical dressings clean and dry is therefore particularly important during Brisbane's warmer months.
What to Expect After ACL Reconstruction

Rehabilitation is a major part of ACL reconstruction.
The operation creates the new ligament, but strength, movement, balance, confidence and sporting function need to be rebuilt progressively over the following months.
First 2 weeks
Early priorities generally include:
- controlling pain and swelling
- regaining full knee extension
- progressively improving knee flexion
- activating the quadriceps
- walking safely
- protecting any associated meniscus or cartilage procedure
Crutches are commonly used initially.
Weight-bearing instructions may be modified if a meniscus repair, cartilage procedure or other additional surgery has been performed.
2–6 weeks
Rehabilitation progressively focuses on:
- normalising walking
- restoring knee movement
- improving quadriceps and hamstring strength
- reducing swelling
- balance and movement control
Many patients are walking comfortably without crutches during this period, although recovery varies.
6 weeks–3 months
Strengthening becomes increasingly important.
Rehabilitation progresses according to function rather than simply the number of weeks since surgery.
Exercises may include:
- progressive resistance training
- single-leg control
- balance and proprioception
- cardiovascular conditioning
- increasingly complex movement patterns
3–6 months
Running and more demanding exercises may gradually be introduced when appropriate strength, movement and control have been achieved.
The knee should not progress simply because a particular date has been reached.
6–12 months and return to sport
Returning to pivoting sport is one of the most important stages of ACL rehabilitation.
Return should consider:
- time since surgery
- quadriceps and hamstring strength
- hopping and functional testing
- movement quality
- absence of significant swelling
- knee stability
- psychological readiness
- the demands of the particular sport
In a prospective cohort study of athletes after ACL reconstruction, returning to high-level knee-demanding sport increased the reinjury rate more than fourfold over two years. The reinjury rate fell by 51% for each month that return to sport was delayed, up to nine months after surgery (PMID 27162233).
For this reason, return to sport should generally be criteria-based as well as time-based, rather than determined by the calendar alone.
Things to Look Out for After ACL Reconstruction

Contact our office, your GP, physiotherapist, or seek urgent medical attention if you develop:
Possible infection
- increasing redness or warmth around the wounds
- increasing pain after initially improving
- persistent wound leakage
- pus or unusual discharge
- fever, chills or feeling significantly unwell
Possible blood clot
Seek medical attention for:
- new calf pain or tenderness
- significant one-sided leg swelling
- sudden shortness of breath
- chest pain or coughing blood
Sudden breathing symptoms require emergency assessment.
Increasing stiffness
Regaining full knee extension is particularly important after ACL reconstruction.
If the knee is becoming increasingly stiff or you are struggling to regain extension despite rehabilitation, this should be assessed.
Persistent swelling
Some swelling is expected during recovery.
Repeated significant swelling after exercise may indicate that rehabilitation is progressing faster than the knee can currently tolerate.
Giving way or another injury
A significant new twisting injury, sudden giving way, new large swelling or a new “pop” should be assessed.
Difficulty progressing rehabilitation
Recovery does not occur at exactly the same speed for every patient.
However, persistent pain, weakness, swelling or difficulty progressing through rehabilitation should be discussed with your treating team.
Summary
ACL reconstruction is an effective operation for people whose knee remains unstable after an ACL tear, or who want to return to sports that involve pivoting and changes of direction. It is usually recommended when the expected benefits outweigh the risks for that person, and some people do well with rehabilitation alone. Please discuss your symptoms, your goals (including plans for sport and work) and your scans with your knee surgeon so that the options, including structured rehabilitation, are considered together.
In this section
- Patellar Tendon Graft
- Hamstring Graft
- Lateral Tenodesis (LET)
- One-Stage ACL Revision
- PCL Reconstruction
- Posterolateral Corner (PLC)
- Quadriceps Graft
- Two-Stage ACL Revision
Articles in this section
General information only. The information on this page is general in nature and does not replace individual medical advice. All surgery carries risks, and results vary between patients. Please discuss your own circumstances with your treating practitioner.
ACL Reconstruction Surgery

Dr Alexey Borshch is a specialist orthopaedic surgeon in Brisbane with a particular clinical focus on surgery of the knee, hip, ankle and lower limb.
His practice as a Brisbane knee surgeon includes the assessment and treatment of ACL injuries, meniscus tears, cartilage injuries, patellar instability and other sporting and traumatic conditions of the knee.
Not every ACL tear requires reconstruction. Assessment includes the patient's symptoms, knee stability, sporting and occupational requirements, associated meniscus or cartilage injuries and response to rehabilitation.
When ACL reconstruction is appropriate, graft selection and any additional procedures are tailored to the individual knee rather than using the same reconstruction for every patient.
Dr. Borshch completed his medical degree at the University of Queensland before undertaking specialist orthopaedic training in Queensland. He completed the Australian Orthopaedic Association training program and the Royal Australasian College of Surgeons Fellowship Examination in Orthopaedic Surgery. He obtained specialist registration in Orthopaedic Surgery in 2022 and is a Fellow of the Australian Orthopaedic Association.
He offers consultations in Hamilton, Brisbane, and conducts private orthopaedic surgery at Brisbane Private Hospital.