
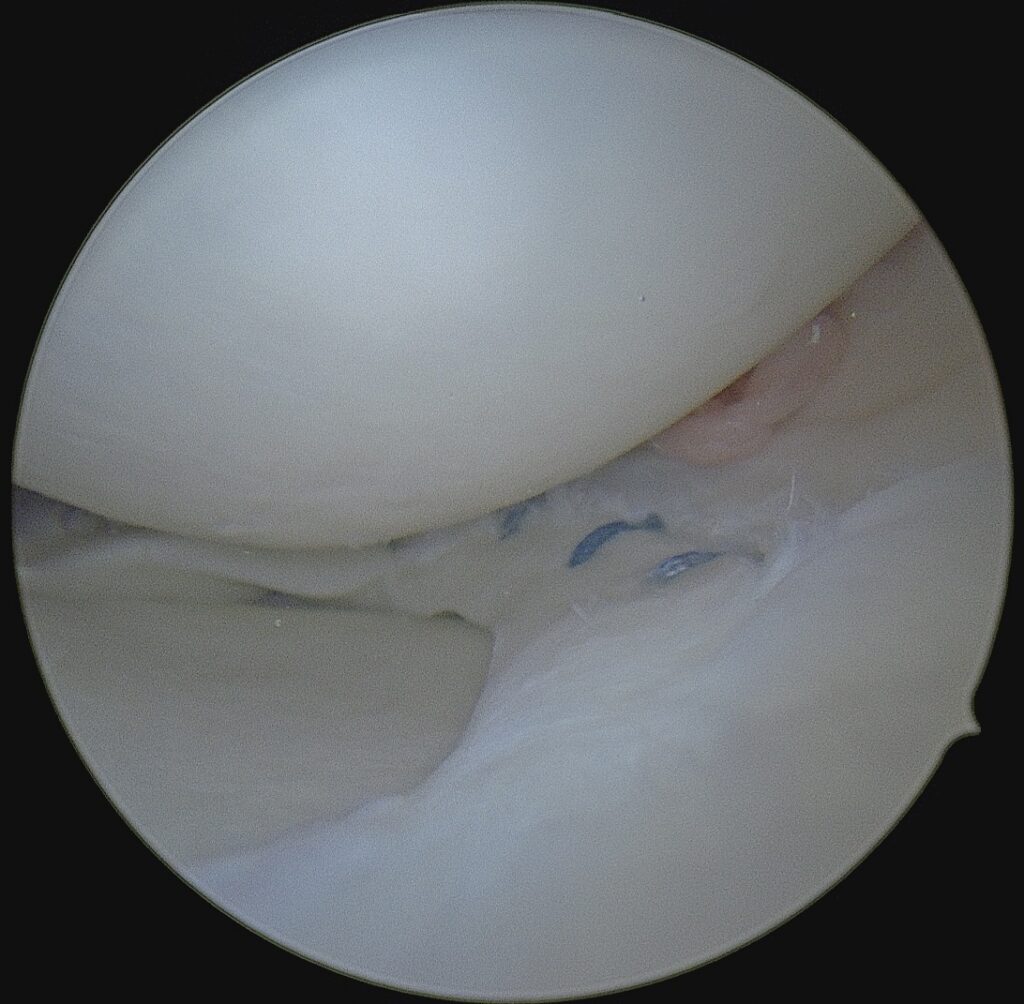
Most meniscus tears are assessed first and treated according to the tear, the knee and the person; repair, where it is possible, aims to preserve the meniscus rather than remove it.
This page provides general information for patients of Dr Borshch, an orthopaedic surgeon consulting in Hamilton, Brisbane, who are being assessed for or considering meniscus repair surgery. Not every meniscus tear needs an operation. An assessment with a Brisbane knee surgeon helps work out whether your tear is likely to settle or whether repair is worth considering.
Your individual condition and treatment plan may be different, so this information should be used alongside advice from your surgeon and treating team.
Meniscus tears: assessment and treatment options
The menisci are two crescent-shaped pads of cartilage that cushion and stabilise the knee. A tear can follow a twisting injury during sport or a fall, or develop gradually as the tissue wears with age. Pain along the joint line, swelling that comes and goes, and catching, clicking or locking of the knee are the usual symptoms, but an MRI showing a tear does not by itself mean an operation is needed. Assessment brings together how the tear happened, your symptoms, examination of the knee and the imaging, and considers the type and position of the tear and whether there is arthritis or a ligament injury alongside it.
Treatment is matched to the tear and to you. Many degenerative tears, and some smaller traumatic tears, settle with physiotherapy, activity modification and time. Where surgery is appropriate, it is done by knee arthroscopy, and the choice is between repairing the tear with sutures, which is described in detail on this page, and trimming the damaged portion (partial meniscectomy) when the tissue cannot heal. Tears that occur with an ACL injury are usually treated at the same time as the ACL reconstruction. Dr Borshch consults in Hamilton, Brisbane, and an assessment with a knee surgeon is the starting point for working out which of these options applies to your knee.
What is Meniscus Repair Surgery?

The meniscus is an important shock absorber and stabiliser inside the knee.
Each knee contains two menisci: the medial meniscus on the inside and the lateral meniscus on the outside.
These strong, flexible structures sit between the femur (thigh bone) and tibia (shin bone). They help:
- distribute forces across the knee
- absorb shock
- contribute to knee stability
- protect the articular cartilage
The menisci are vital for the normal function and long-term health of the knee (PMID 25125315). A meniscus tear can upset the way load is shared across the joint, and this can lead to faster wear of the joint (articular) cartilage (PMID 35947336).
A meniscus can tear during a twisting or sporting injury. Tears can also develop gradually as the meniscus changes with age.
Meniscus repair is a minimally invasive operation in which the torn edges of the meniscus are stitched back together with sutures so that the tear can heal. Only the outer 10–25% of the meniscus has a blood supply (PMID 7081532), so tears in or close to this outer zone have the best chance of healing after repair.
Not every meniscus tear requires surgery.
When surgery is appropriate, there are two broad options: repair the torn meniscus, or remove the damaged portion with a partial meniscectomy.
Where a tear has a reasonable opportunity to heal, I generally prefer to preserve and repair the meniscus rather than remove it.
Why is Meniscus Repair Surgery Done?

When is meniscus repair considered?
Symptoms of a meniscus tear can include:
- pain along the joint line
- swelling
- catching or clicking
- pain with twisting or squatting
- difficulty returning to sport
- locking of the knee
However, an MRI showing a meniscus tear does not automatically mean that surgery is required.
A thorough clinical examination by a specialist and modern imaging, usually an MRI scan, help confirm the diagnosis and show the type and position of the tear.
Some tears can be managed successfully with physiotherapy, activity modification and time.
The decision to operate considers:
- symptoms
- tear pattern
- tear location
- tissue quality
- age of the tear
- patient age and activity
- knee stability
- associated ACL injury
- cartilage and arthritis elsewhere in the knee
Meniscus repair is particularly attractive when there is a traumatic tear in otherwise useful meniscal tissue.
A recent systematic review and meta-analysis examining the timing of meniscus repair found that earlier repair after injury was associated with a lower risk of repair failure in some of the time intervals analysed, although the underlying evidence was mostly lower-level observational research (PMID 39846803).
How is Meniscus Repair Surgery Performed?
Most meniscus repairs are performed by minimally invasive arthroscopic (keyhole) surgery, with sutures placed across the tear.
Anaesthetic
Meniscus repair is performed under anaesthetic, and local anaesthetic is also used for pain relief. Your anaesthetist will discuss the anaesthetic with you before surgery.
Arthroscopy
A small camera (arthroscope) is inserted into the knee through small incisions, usually 5–7 mm long. This is called knee arthroscopy.
This allows me to assess:
- the meniscus tear
- cartilage surfaces
- ACL and other ligaments
- the remainder of the knee
The final decision about whether a meniscus can be repaired is sometimes made during arthroscopy, because the quality and stability of the actual tissue can be assessed directly.
Preparing and repairing the meniscus
When the tear is repairable, the torn edges are brought back together.
Depending on the location and pattern of the tear, different repair techniques can be used, including:
- all-inside repair devices
- inside-out sutures
- outside-in sutures
- combinations of techniques
Inside-out repairs use an additional small incision at the side of the knee so that the nerves and blood vessels can be protected while the sutures are tied.
The aim is to achieve a stable repair while preserving as much healthy meniscus as possible.
The biological environment around the tear may also be stimulated to encourage healing.
What if the meniscus cannot be repaired?
Unfortunately, not every tear can heal.
If part of the meniscus is severely damaged, fragmented or has poor tissue quality, repair may not be reliable.
In this situation, the unstable damaged portion may need to be trimmed while preserving as much healthy meniscus as reasonably possible.
Meniscus repair with ACL reconstruction
Meniscus tears commonly occur together with ACL injuries.
When both injuries require surgery, the meniscus can often be repaired during the same operation as the ACL reconstruction. In a meta-analysis of 3,829 patients, repairs performed at the same time as ACL reconstruction had a lower failure rate than repairs in knees without a reported ACL injury (8.5% compared with 14%) (PMID 37022676).
What are the benefits of meniscus repair?
A successful repair preserves the meniscus, so that it can keep protecting the knee.
Meniscus repair saves meniscal tissue rather than removing it. In a meta-analysis of 20 studies including 31,783 patients, meniscus repair was associated with lower progression to advanced knee osteoarthritis and to knee replacement than partial meniscectomy over several years of follow-up (PMID 37812251).
A systematic review comparing repair with partial meniscectomy for traumatic tears found that, in the studies with long-term follow-up, repair was associated with better knee function scores and less wear of the joint on X-rays (PMID 21820843).
Good results can last. A systematic review of studies with at least 7 years of follow-up reported good to very good clinical scores after meniscus repair, and six of the studies found only minor wear on X-rays that differed little from the other knee (PMID 33913009).
Most people return to sport. In a systematic review of athletes, 81% to 88.9% returned to sport after meniscus repair (PMID 29023273), and in another review 71.2% to 100% of patients returned to play across 13 studies (PMID 33615271).
What are the risks of meniscus repair?
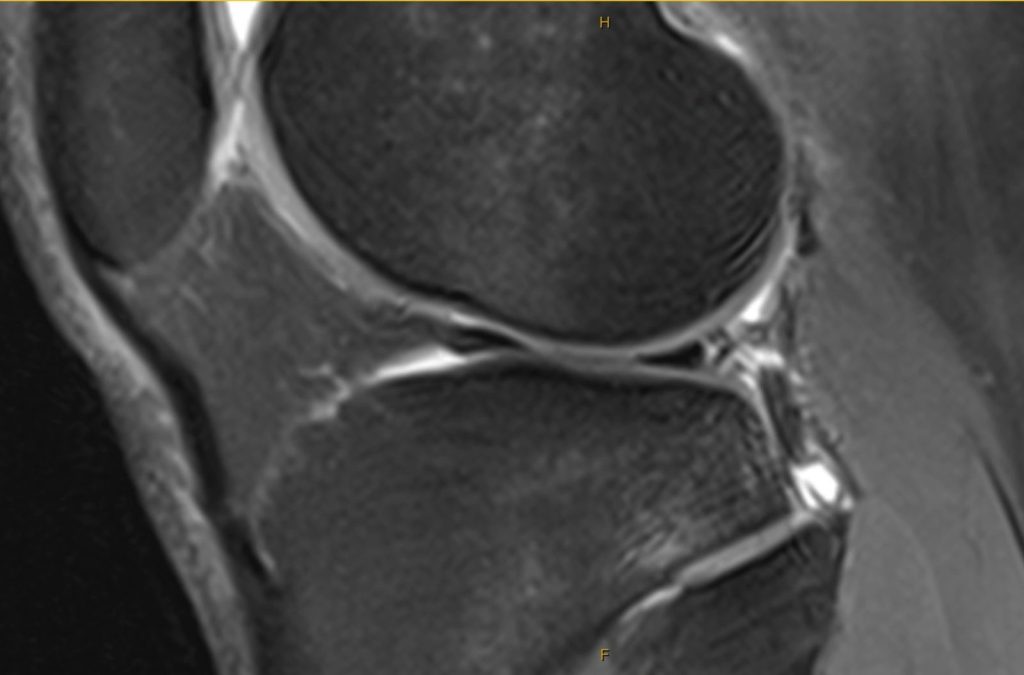
A repaired meniscus can fail to heal or tear again, and recovery is slower than after trimming the meniscus.
Recovery takes longer than after partial meniscectomy (trimming). In a systematic review of athletes, most returned to their pre-injury activity 7 to 9 weeks after partial meniscectomy, while return to sport took on average 5.6 months after isolated meniscus repair (PMID 29023273).
Some repairs do not heal or tear again. A meta-analysis of 3,829 patients reported an overall failure rate of 14.8% between two and five years after surgery (PMID 37022676). A meta-analysis of studies with at least five years of follow-up reported an overall failure (revision) rate of 19.1%, and 36% of failures occurred after the second year (PMID 34671817).
Further surgery is more likely after repair than after trimming. A systematic review found long-term reoperation rates of 20.7% after isolated meniscus repair and 3.9% after partial meniscectomy (PMID 21820843). In a Swedish cohort followed for up to 10 years, patients aged 15 to 40 had a 4.3 times higher risk of any further knee operation after meniscus repair than after partial meniscectomy (PMID 40686041).
Nerve injury can occur. In a meta-analysis comparing techniques, nerve injury was more common after inside-out repair than after all-inside repair (PMID 33482623).
Stiffness can occur, particularly when the repair is combined with ACL reconstruction. In a series of 101 meniscus repairs, arthrofibrosis (excessive scar tissue causing stiffness) occurred in 10% of repairs performed with ACL reconstruction (PMID 8291641).
As with any surgery, there are general risks such as infection and blood clots. A repair does not undo damage that the original injury may have caused to the cartilage, ligaments or other structures, and repairing a meniscus has not been proven to prevent arthritis completely.
These figures describe groups of patients. They cannot predict whether an individual repair will heal.
Preparing for Meniscus Repair Surgery in Brisbane

A good pre-operative knee makes early rehabilitation easier.
Where possible, preparation focuses on reducing swelling and maintaining:
- full knee extension
- good knee movement
- quadriceps strength
- normal walking
- general fitness
Before surgery:
- stop smoking or vaping if possible
- maintain good nutrition
- optimise diabetes and other medical conditions
- provide a complete list of medications and supplements
- tell us about previous blood clots or anaesthetic problems
Preparing your home
Because meniscus repair needs time to heal, you may require crutches and sometimes a brace after surgery.
Arrange transport and consider how you will manage stairs, work and everyday activities.
Because Brisbane has a warm and humid climate, particularly during summer, consider making sure you have access to a cool, comfortable and preferably air-conditioned environment during early recovery. Apart from making recovery more comfortable, a large meta-analysis found an association between warmer weather and higher rates of surgical-site infection (PMID 34422523). Keeping your surgical dressings clean and dry is therefore particularly important during Brisbane's warmer months.
What to Expect After Meniscus Repair Surgery

Rehabilitation protects the repair and restores movement, strength and activity.
Rehabilitation after meniscus repair is different from rehabilitation after simply trimming a meniscus.
The repaired tissue needs time to heal.
First 2 weeks
Early priorities usually include:
- controlling pain and swelling
- protecting the repair
- regaining appropriate knee movement
- maintaining full knee extension
- activating the quadriceps
- using crutches as instructed
Some patients can place weight through the leg relatively early, while others require restricted weight-bearing.
2–6 weeks
Your exact rehabilitation depends on the tear that was repaired.
A systematic review of rehabilitation after meniscus repair found substantial variation between protocols and reported that accelerated programs allowing early movement and weight-bearing were not associated with higher failure rates in the available studies (PMID 29682310).
However, this does not mean every meniscus repair should follow an accelerated program.
A small vertical tear can behave very differently from a large complex, radial or root tear.
I therefore tailor restrictions to the tear pattern, repair stability and associated procedures.
6 weeks–3 months
As healing progresses, rehabilitation increasingly focuses on:
- normalising walking
- restoring full movement
- quadriceps and hamstring strength
- hip and core strength
- balance and proprioception
- progressive cardiovascular exercise
3–6 months and return to sport
Running, pivoting and sport are reintroduced progressively.
A systematic review of 88 studies examining rehabilitation and return to play after isolated meniscus repair found considerable variation in protocols, with six months being the most commonly used return-to-play time point (PMID 33615271).
Another systematic review of athletes reported an average return to sport at 5.6 months after isolated meniscus repair (PMID 29023273).
Return to sport should be based on healing, strength, movement, knee control and the demands of the particular sport, rather than simply reaching a particular date.
Things to Look Out for After Meniscus Repair

Some pain and swelling are normal, but worsening symptoms should be assessed.
Contact our office, your GP or seek medical attention if you develop:
Possible infection
- increasing redness or warmth around the incisions
- worsening pain after initially improving
- persistent wound leakage or pus
- fever or feeling significantly unwell
Possible blood clot
Seek medical attention for:
- new calf pain or tenderness
- significant one-sided leg swelling
- sudden shortness of breath
- chest pain or coughing blood
Sudden breathing symptoms require emergency assessment.
Increasing stiffness
Some stiffness is expected early after surgery.
Progressive loss of movement or difficulty regaining full knee extension should be discussed with your treating team.
Recurrent locking or catching
Occasional sensations during early recovery do not necessarily mean the repair has failed.
However, recurrent mechanical locking, significant joint-line pain or repeated swelling after the knee had been improving should be assessed.
A new injury
A significant twist, fall or sporting injury can potentially damage a healing meniscus repair.
A new episode of sharp pain, swelling, locking or loss of function should be reviewed.
Common questions about meniscus tears
Does a torn meniscus need surgery?
Often not. For degenerative tears in people over 45 without a locked knee, randomised trials have shown that a structured physiotherapy programme gives similar knee function to arthroscopic surgery over one to two years of follow-up, and that many patients avoid an operation altogether (PMID 30285177; PMID 23506518). Surgery is more likely to help when the knee locks or will not straighten, when a traumatic tear occurs in a young or active person, or when the tear is one that can be repaired. A meniscus tear found alongside knee arthritis is usually part of the arthritis rather than a separate problem to operate on.
Can a meniscus tear heal without surgery?
Some can. Only the outer 10–25% of the meniscus has a blood supply, so tears near the rim have the capacity to heal while tears in the inner, avascular part do not (PMID 7081532). Even a tear that does not heal can become painless as the knee settles, which is why symptoms rather than the scan guide treatment. If a tear in the vascular zone is repairable, early repair gives it the best chance of healing, so a traumatic tear in a younger knee should be assessed promptly rather than left for months. You can read more in Can a meniscus tear heal on its own?
How long is recovery after meniscus surgery?
It depends on what was done. After a partial meniscectomy (trimming), most people walk without crutches within days and return to everyday activity within a few weeks. After a repair, the tissue needs time to heal, so crutches, movement limits and a graded rehabilitation programme are used for the first six weeks, with running and sport reintroduced over three to six months as described above. Dr Borshch sets the timetable to the tear and the repair rather than to a fixed date.
Do I need a referral to see a meniscus surgeon in Brisbane?
Yes. A current referral from your GP or another specialist is needed for a specialist consultation and for Medicare rebates. Bring any MRI or X-rays you already have; if imaging is needed it can be arranged after the consultation. See seeing a knee surgeon in Brisbane or request an appointment.
Summary
Meniscus repair aims to save a torn meniscus so that it can keep protecting the knee. It is usually recommended when the expected benefits outweigh the risks for that person, which depends on the tear, the quality of the tissue and the rest of the knee, and many tears settle without surgery. Please discuss your symptoms, your goals (including plans for sport and work) and your scans with your knee surgeon so that the options, including physiotherapy, meniscus repair and partial meniscectomy, are considered together.
In this section
Articles in this section
General information only. The information on this page is general in nature and does not replace individual medical advice. All surgery carries risks, and results vary between patients. Please discuss your own circumstances with your treating practitioner.
Meniscus Repair Surgery

Dr Alexey Borshch is a specialist orthopaedic surgeon in Brisbane with a particular clinical focus on surgery of the knee, hip, ankle and lower limb.
His practice as a Brisbane knee surgeon includes the assessment and treatment of meniscus tears, ACL and PCL injuries, cartilage injuries, patellar instability and other sporting and traumatic knee conditions.
Not every meniscus tear requires surgery, and not every tear can be repaired. When surgery is appropriate, the decision between meniscus repair and partial meniscectomy depends on the tear pattern, location, tissue quality, associated injuries and individual patient.
Where there is a reasonable opportunity for healing, my preference is to repair and preserve useful meniscal tissue rather than remove it.
Dr. Borshch completed his medical degree at the University of Queensland before undertaking specialist orthopaedic training in Queensland. He completed the Australian Orthopaedic Association training program and the Royal Australasian College of Surgeons Fellowship Examination in Orthopaedic Surgery. He obtained specialist registration in Orthopaedic Surgery in 2022 and is a Fellow of the Australian Orthopaedic Association.
He consults in Hamilton, Brisbane, and performs private orthopaedic surgery at Brisbane Private Hospital.