
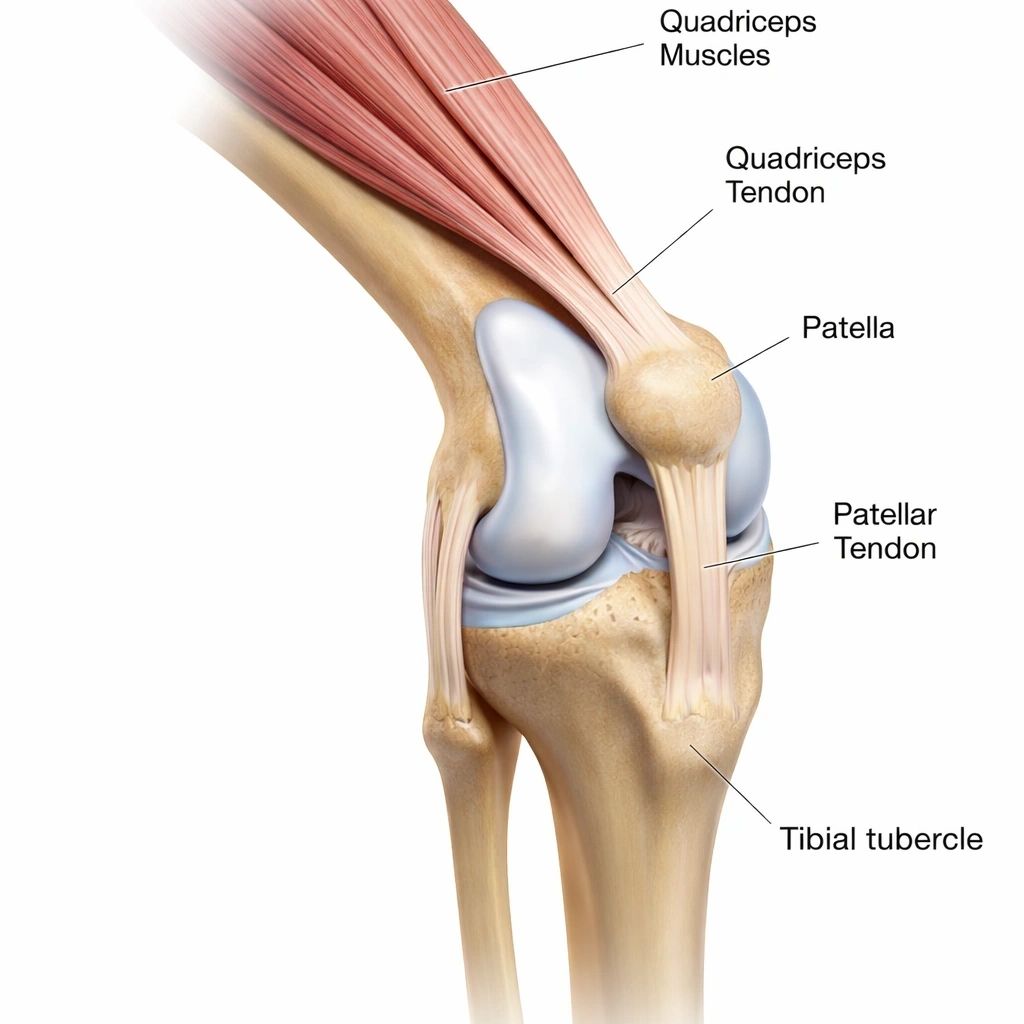
This page provides general information for patients of Dr Borshch, an orthopaedic surgeon consulting in Hamilton, Brisbane, who are being assessed for or considering patella stabilisation surgery for kneecap instability. Recurrent kneecap dislocation is one of the common reasons people see a knee surgeon in Brisbane. Assessment looks at why the kneecap is unstable before any treatment is proposed.
Your individual condition and treatment plan may be different, so this information should be used alongside advice from your surgeon and treating team.
What is Patella Stabilisation Surgery?

Patella stabilisation treats a kneecap that repeatedly slips or dislocates.
The patella (kneecap) normally sits within a groove at the front of the femur called the trochlea. As the knee bends and straightens, the patella moves within this groove.
Patellar instability occurs when the kneecap moves too far out of its normal position, usually laterally (to the outside). This may involve:
- subluxation – the kneecap partially slips out
- dislocation – the kneecap completely leaves the groove
- repeated episodes of instability
- apprehension or fear that the kneecap is about to dislocate
Kneecap dislocation is most common in teenagers. A 21-year population-based study found an overall annual incidence of 23.2 per 100,000 people, rising to 147.7 per 100,000 in adolescents aged 14 to 18 years (PMID 28795924).
The medial patellofemoral ligament (MPFL) is an important ligament on the inner side of the knee that helps prevent the patella moving excessively towards the outside. In a laboratory study of knee specimens, cutting the MPFL increased the sideways movement of the kneecap by 50%, and repairing it restored the balance (PMID 9584380). The MPFL is commonly injured when the kneecap dislocates.
A dislocation can also damage the joint surfaces. In an MRI study of first-time dislocations, 43% of knees had an injury to the cartilage, including osteochondral fractures (a piece of cartilage and bone breaking off) in 18% (PMID 36749375).
However, patellar instability is not always simply a torn ligament. Other contributing factors can include:
- trochlear dysplasia – a shallow or unusually shaped groove
- patella alta – a relatively high kneecap
- increased lateral pull through the patellar tendon
- rotational or alignment differences in the leg
- generalised ligament laxity
A systematic review and meta-analysis of recurrence after a first-time dislocation found that younger age, open growth plates, trochlear dysplasia, patella alta and an increased tibial tubercle–trochlear groove distance (a measure of how far to the outside the patellar tendon pulls on the kneecap) were associated with recurrent instability (PMID 31825650).
For this reason, patella stabilisation is not one operation. Surgery should address the particular factors causing instability in the individual knee.
Why is Patella Stabilisation Surgery Done?
Surgery is mainly considered for recurrent or ongoing symptomatic kneecap instability.
Not every patellar dislocation requires surgery.
A first-time dislocation can often be treated with physiotherapy, progressive strengthening, activity modification and sometimes temporary bracing.
Surgery may be considered when there is:
- recurrent patellar dislocation
- repeated subluxation or giving way
- persistent instability despite appropriate physiotherapy
- significant apprehension limiting sport or everyday activity
- an associated cartilage or osteochondral injury
- anatomical factors creating substantial ongoing instability
Even after a first dislocation, the risk of it happening again varies considerably. A systematic review reported an overall recurrence rate of 33.6%, rising to 70.4% to 78.5% when three anatomical risk factors were present (PMID 31825650).
A thorough clinical examination by a specialist and modern imaging, such as X-rays, CT scans and MRI scans, help identify these factors and any cartilage damage.
The decision to operate should therefore consider how often the kneecap is unstable, symptoms, anatomy, cartilage damage, activity requirements and response to rehabilitation, rather than simply the appearance of an MRI scan.
How is Patella Stabilisation Surgery Performed?

Surgery is tailored to the damaged ligament, kneecap alignment and shape of the knee.
The exact operation depends on why the patella is unstable. Some patients require only a ligament reconstruction, while others benefit from a combination of soft-tissue and bony procedures.
Anaesthetic
The operation is performed under anaesthesia. Local anaesthetic is often added to help with pain relief afterwards.
Assessing the knee
A knee arthroscopy (a minimally invasive keyhole examination through small incisions) may be performed to assess:
- cartilage on the patella
- cartilage within the trochlea
- loose cartilage or bone fragments
- menisci
- other structures inside the knee
Cartilage or osteochondral injuries can sometimes be treated during the same operation (see cartilage repair).
MPFL reconstruction
Medial patellofemoral ligament reconstruction is commonly used for recurrent lateral patellar instability.
A tendon graft is used to recreate the damaged MPFL between the inner side of the patella and the femur.
The aim is not to tightly hold the kneecap in one position. The graft is positioned and tensioned to provide stability while allowing the patella to move naturally within the trochlea as the knee bends.
Tibial tubercle osteotomy
The tibial tubercle is the bony attachment of the patellar tendon on the upper shin bone.
In some patients, its position contributes to abnormal lateral pull on the kneecap or a high-riding patella.
A tibial tubercle osteotomy (TTO) involves carefully cutting this piece of bone, moving it to a more appropriate position and fixing it with screws while it heals.
Depending on the problem, the tubercle can be moved:
- towards the inside of the knee to alter the direction of pull (tibial tubercle medialising osteotomy)
- forwards to reduce pressure on selected damaged cartilage
- downwards in selected patients with significant patella alta (tibial tubercle distalising osteotomy)
Not everyone undergoing MPFL reconstruction needs an osteotomy.
A systematic review of 806 knees found similar knee function scores and redislocation rates after isolated MPFL reconstruction and after MPFL reconstruction combined with a tibial tubercle osteotomy, although the patients who had the combined operation had a greater outward pull on the kneecap before surgery (PMID 38044955). This is why the operation is chosen according to the individual knee.
Trochleoplasty
Some patients have severe trochlear dysplasia, where the groove in which the kneecap should travel is very shallow or abnormally shaped.
In selected patients with severe dysplasia and recurrent instability, trochleoplasty may be considered to reshape the trochlea.
This is a specialised procedure and is not required for most patients.
Closing the knee
Once the reconstruction is complete, the deeper tissues and the incisions are closed and dressings are applied.
A knee brace may be used depending on the procedure performed.
What are the benefits of patella stabilisation surgery?

The main benefit is a more stable kneecap, so that the knee can be used with more confidence.
MPFL reconstruction lowers the chance of the kneecap dislocating again. A network meta-analysis found that MPFL reconstruction led to fewer redislocations and better knee function scores than MPFL repair or non-operative treatment (PMID 34604425). In a meta-analysis of randomised trials after a first dislocation, recurrent instability occurred in 3.92% of patients after MPFL reconstruction, compared with 33.33% after non-operative treatment (PMID 41496495).
Most people return to sport. In a meta-analysis of 930 patients, 92.8% returned to sport after MPFL reconstruction and 71.3% returned to or exceeded their previous level, at a mean of 6.7 months after surgery (PMID 33720789). In another review of 1,278 patients, 85.1% returned to play, 68.3% returned to the same level, and average pain scores fell from 4.3 to 1.6 (PMID 32866030).
Good results can last. A systematic review of studies with at least five years of follow-up (a mean of 98 months) found significant improvements in knee function and activity scores after MPFL reconstruction (PMID 40190990).
When an additional bony procedure is needed, it also helps. A tibial tubercle osteotomy, performed alone or with MPFL reconstruction, reliably improved knee function scores in a meta-analysis of 1,733 knees (PMID 40995414). In a meta-analysis of 1,571 knees with trochlear dysplasia, redislocation was rare after MPFL reconstruction, trochleoplasty or both combined (a mean of 0.7%) (PMID 39755951).
What are the risks of patella stabilisation surgery?
Like all surgery, patella stabilisation carries risks, and the kneecap can still become unstable again.
Complications are not rare. A systematic review of 629 knees after MPFL reconstruction reported complications in 26.1%, ranging from minor to major. They included patellar fracture, recurrent instability, loss of knee bending, wound problems and pain, and 4.1% of patients needed a further operation (PMID 22679297). Treatment-related complications are more likely after MPFL reconstruction than after non-operative treatment (PMID 34604425).
The kneecap can become unstable again after surgery. Recurrent instability occurred in 1.9% of patients in one meta-analysis (PMID 33720789) and in 5.4% in another review, in which 31.7% of patients did not return to the same level of sport (PMID 32866030).
A tibial tubercle osteotomy adds the risks of a bone operation. In a meta-analysis of 1,733 knees, minor complications occurred in 9% and major complications in 3%, recurrent instability in 3% to 8%, and 16% of patients had a further operation, most often to remove screws (PMID 40995414).
Trochleoplasty is a larger operation. In a meta-analysis of 1,000 trochleoplasties, stiffness occurred in 7%, patellofemoral arthritis in 27% and further surgery in 17% (PMID 34365023).
Other risks include infection, blood clots, stiffness, and problems with the incisions or nearby nerves. Some patients continue to experience pain at the front of the knee despite improved stability, particularly when cartilage damage was already present.
These figures describe groups of patients and cannot predict the outcome for an individual patient.
Does patella stabilisation prevent arthritis?
This has not been established.
Patellar dislocation itself can injure the cartilage. In an MRI study of 20 patients followed for about eight years after a first dislocation treated without surgery, all showed some deterioration of the patellofemoral cartilage (PMID 28298062). In a population-based study of 609 patients, 9.5% had developed patellofemoral arthritis at a mean of 12.3 years after a dislocation, compared with 1.3% of matched people without a dislocation (PMID 28005405).
However, this does not prove that stabilisation surgery prevents future arthritis. The primary purpose of surgery is to treat symptomatic instability and address relevant anatomical factors.
How Should I Prepare for Patella Stabilisation in Brisbane?

Preparing your knee, health and home can make early rehabilitation easier.
Prehabilitation
Where possible, physiotherapy before surgery aims to:
- reduce swelling
- restore full knee extension
- maintain knee flexion
- strengthen the quadriceps
- strengthen the hip and gluteal muscles
- improve balance and movement control
The aim is to arrive at surgery with the knee as mobile, strong and settled as reasonably possible.
Health preparation
Before surgery:
- stop smoking or vaping if possible
- maintain good nutrition
- optimise diabetes and other medical conditions
- provide a complete list of medications and supplements
- tell us about blood-thinning medications
- tell us about previous blood clots or anaesthetic problems
Preparing your home
You will generally require crutches during early recovery, and some patients also require a brace.
Arrange transport and some assistance with shopping, meals and everyday activities if required. Remove loose rugs and other trip hazards and consider how you will manage stairs.
Because Brisbane has a warm and humid climate, particularly during summer, consider making sure you have access to a cool, comfortable and preferably air-conditioned environment during early recovery. Apart from making recovery more comfortable, published research has found an association between warmer weather and higher rates of surgical-site infection (PMID 34422523).
Keeping yourself comfortable and your surgical dressing clean and dry is therefore particularly important during Brisbane's warmer months.
What Should I Expect After Patella Stabilisation Surgery?

Recovery progresses from protecting the reconstruction to rebuilding strength and confidence.
Rehabilitation depends on the operation performed. Recovery after an isolated MPFL reconstruction is different from recovery after MPFL reconstruction combined with an osteotomy or cartilage procedure.
After the operation
Pain is managed using several different approaches. A physiotherapist will help you begin moving safely and teach you how to use crutches.
First 2 weeks
Early priorities include:
- controlling pain and swelling
- protecting the reconstruction
- regaining appropriate knee movement
- activating the quadriceps
- keeping the incisions clean and dry
- walking safely with crutches
Weight-bearing and knee-bending instructions depend on the operation performed.
2–6 weeks
Physiotherapy progressively focuses on knee movement, quadriceps activation and walking.
Patients who have undergone a tibial tubercle osteotomy generally require additional protection while the bone heals compared with patients having an isolated soft-tissue reconstruction.
A systematic review of rehabilitation after MPFL reconstruction with and without a tibial tubercle osteotomy found no agreed rehabilitation programme, although most programmes restricted weight-bearing and knee bending only in the early weeks after surgery (PMID 35701590).
6 weeks–3 months
As healing progresses, rehabilitation increasingly focuses on:
- restoring knee movement
- quadriceps strength
- hip and gluteal strength
- balance
- single-leg control
- normal walking
- cardiovascular fitness
Driving can resume when you can safely control the vehicle, are no longer impaired by pain medication and can confidently perform an emergency stop.
3–12 months
Running, jumping, pivoting and sport-specific exercises are progressively introduced once sufficient healing, strength and movement control have returned.
Return to sport should consider strength, stability, movement quality, confidence and the particular operation performed, rather than simply reaching a particular date.
Things to Look Out for After Patella Stabilisation

Worsening redness of the incisions, severe swelling, instability or breathing symptoms require assessment.
Contact our office, your GP or seek medical attention if you develop:
Possible infection
- increasing redness or warmth around the incisions
- worsening pain after initially improving
- persistent leakage or pus from the incisions
- fever or feeling significantly unwell
Possible blood clot
Seek medical attention for new calf pain or significant one-sided leg swelling.
Sudden shortness of breath, chest pain or coughing blood requires emergency assessment.
Increasing stiffness
Some stiffness is expected during early recovery.
Progressive loss of movement or difficulty regaining knee flexion or extension should be discussed with your treating team.
Incision, nerve or circulation problems
Persistent leakage, an incision opening, rapidly increasing swelling, a cold or pale foot, or new significant weakness requires assessment.
Recurrent instability
Some apprehension around the kneecap can occur while strength and confidence recover.
However, a definite episode where the kneecap significantly slips or dislocates should be assessed.
New injury
A significant fall, twist or sporting injury can potentially damage a healing reconstruction or osteotomy.
New severe pain, swelling, instability or loss of function should be reviewed.
Summary
Patella stabilisation surgery aims to stop the kneecap dislocating, so that the knee can be used with confidence. It is usually recommended when the expected benefits outweigh the risks for that person, which depends on how often the kneecap is unstable, the shape and alignment of the knee and any cartilage damage, and many first-time dislocations settle with physiotherapy. Please discuss your symptoms, your goals (including plans for sport and work) and your scans with your knee surgeon so that the options, including physiotherapy, MPFL reconstruction and any additional bony procedures, are considered together.
In this section
Articles in this section
General information only. The information on this page is general in nature and does not replace individual medical advice. All surgery carries risks, and results vary between patients. Please discuss your own circumstances with your treating practitioner.
Patella stabilisation

Dr Alexey Borshch is a specialist orthopaedic surgeon in Brisbane with a particular clinical focus on surgery of the hip, knee and lower limb.
His practice as a Brisbane orthopedic surgeon focuses on the assessment and treatment of knee injuries, as well as performing ACL reconstruction surgery, PCL reconstruction, Multi-ligament reconstruction and patella stabilisation surgery.
Dr. Borshch completed his medical degree at the University of Queensland before undertaking specialist orthopaedic training in Queensland. He completed the Australian Orthopaedic Association training program and the Royal Australasian College of Surgeons Fellowship Examination in Orthopaedic Surgery. He obtained specialist registration in Orthopaedic Surgery in 2022 and is a Fellow of the Australian Orthopaedic Association.
He offers consultations in Hamilton, Brisbane, and conducts private orthopaedic surgery at Brisbane Private Hospital.