
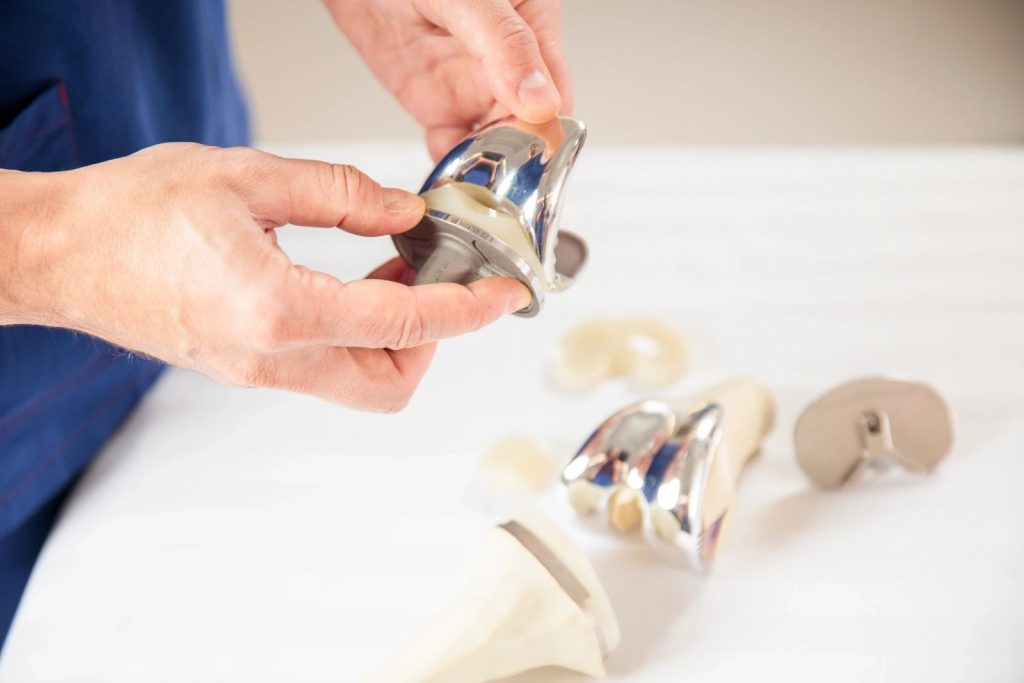
Knee Replacement Surgery - Brisbane & Hamilton
Full knee replacement, also known as Total knee arthroplasty, is an operation used to treat advanced knee arthritis when pain, stiffness and loss of function remain significant despite appropriate non-surgical treatment. Dr Alexey Borshch provides knee replacement assessment and surgery in Brisbane, with consultations in Hamilton. Patients considering surgery for knee arthritis can arrange an assessment with a knee surgeon in Brisbane to discuss whether replacement, or continued non-surgical care, is the right next step.
Your individual condition and treatment plan may be different, so this information should be used alongside advice from your surgeon and treating team.
What is Total Knee Replacement Surgery?
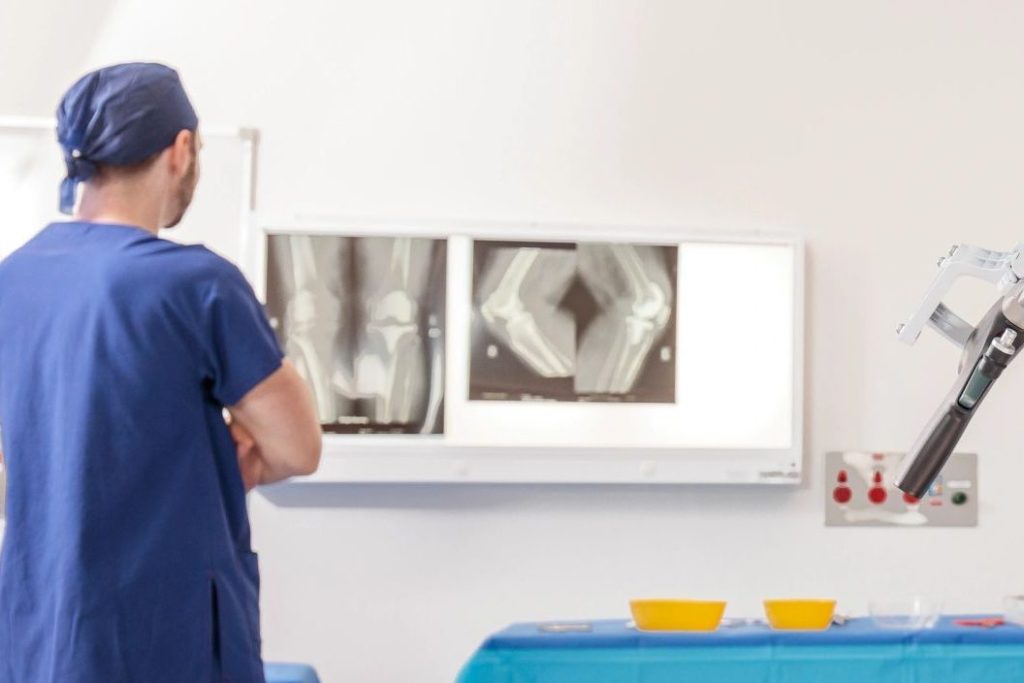
A Knee Replacement swaps the damaged knee joint surfaces with metal and polyethylene surfaces.
Knee replacement is one of the most commonly performed and cost-effective operations in orthopaedics. Its main purpose is to treat painful knee osteoarthritis that limits function and quality of life (PMID 30496082).
The aim of Total Knee Replacement is to:
- reduce knee pain
- improve walking and everyday activities
- correct significant bow-legged or knock-kneed deformity
- improve knee stability and function
- improve quality of life
The operation does not replace the entire knee. Rather the surface layer of damaged bone and cartilage is removed from the ends of the femur (thigh bone) and tibia(shin bone) and replaced with artificial surfaces.
Although "Full knee replacement" and "Total knee replacement" describe the same surgery, an important distinction is that in a Total knee replacement the surface of the tibia and the femur are replaced, but the undersurface of the kneecap may be left intact or also be replaced with a plastic component. The decision on whether to replace the patella (kneecap) surface depends partly on the condition of the remaining cartilage, the cause of arthritis (inflammatory or infective) and sometimes patient age. Resurfacing the kneecap reduces the chance of needing a further operation, but has not been shown to make a clinically meaningful difference to knee scores (PMID 42834409). A Partial knee replacement only replaces one or two of the knee articulations (medial, lateral, patellofemoral).
Why is Total Knee Replacement Done?

TKR may be considered when advanced knee arthritis causes ongoing pain and loss of function.
The most common reason for knee replacement surgery is advanced osteoarthritis of the knee. Osteoarthritis causes progressive loss of the smooth cartilage covering the joint. As this cartilage becomes thin or disappears, the underlying bone becomes exposed and can become painful.
A knee replacement may be considered when:
- knee pain affects walking, stairs, sleep, work or recreation
- the knee has become significantly stiff
- arthritis has caused bow-legged or knock-kneed deformity
- the knee feels unstable because of advanced arthritis
- non-surgical treatments are no longer adequately controlling symptoms
Not everyone with knee arthritis needs a knee replacement. Treatment may initially include exercise, physiotherapy, weight management, medications, injections and activity modification.
The decision to proceed with surgery should therefore be based on a combination of your symptoms, examination, X-rays, general health, previous treatment and goals.
How is Total Knee Replacement Surgery Performed?

The damaged knee is resurfaced with carefully positioned knee replacement components.
Exact techniques vary, but my total knee replacements generally involve the following steps.
1. Anaesthetic
A spinal or general anaesthetic may be used, together with additional methods of pain relief around the knee.
2. Accessing the knee
An incision is made at the front of the knee. The kneecap is carefully moved aside and the joint is exposed.
3. Preparing and aligning the knee
A small amount of damaged bone and cartilage is removed from the femur and tibia.
The aim is not simply to insert new components, but to position them so that the leg has appropriate alignment and the knee is stable and balanced throughout its range of movement.
I use computer navigation or robotic assistance during knee replacement surgery to assist with measurement, alignment and positioning of the components.
4. Placing the knee replacement
Metal components are attached to the femur and tibia, commonly using bone cement.
A highly durable plastic insert is placed between the metal components. This creates the new bearing surface of the knee.
5. Closing the knee
The deeper tissues are repaired using strong sutures and the incision is closed in several layers with absorbable sutures.
I generally close the skin with a fine absorbable suture underneath the skin and use a glued mesh over the incision. This provides additional support while the skin heals.
What are the benefits of a total knee replacement?
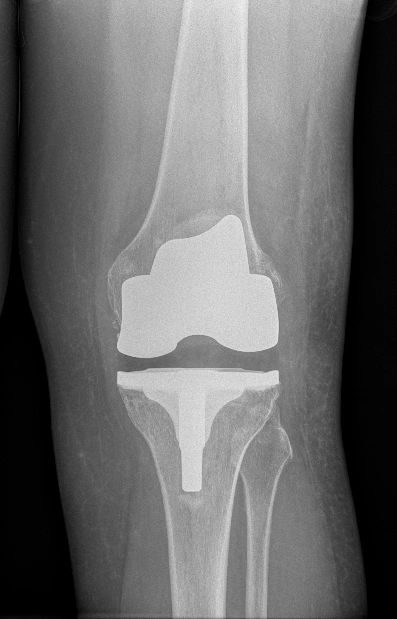
For appropriately selected patients, knee replacement reduces pain, improves function and lasts for many years.
Total knee replacement reduces pain and improves function in people with advanced knee arthritis. In a randomised trial, people who had a knee replacement followed by a 12-week programme of exercise and education improved about twice as much at 12 months as those who had the programme alone (32.5 compared with 16.0 points on a combined score of pain, symptoms, daily activities and quality of life) (PMID 26488691).
Most patients are satisfied with the result. A systematic review of studies including more than 95,000 patients found that 83% of the studies reported satisfaction above 80%, with pain relief and better function being the main reasons for satisfaction (PMID 29983663).
Modern knee replacements are durable. Pooled national joint replacement registry data show that 82.3% of total knee replacements were still working without revision 25 years after surgery (PMID 30782341).
What are the risks of a total knee replacement?
Knee replacement is major surgery. Most patients do well, but complications can happen and not every knee feels normal afterwards.
A knee replacement does not give everyone a pain-free or “normal” knee. In the best-quality studies, about 20% of people reported an unfavourable long-term pain outcome after knee replacement (PMID 22357571). A more recent review found an average dissatisfaction rate of 10%, mainly due to complications, unmet expectations, persistent pain and stiffness (PMID 36252743).
Like any major operation, knee replacement carries a risk of complications. In the randomised trial above, there were more serious adverse events in the knee replacement group than in the non-surgical group (24 compared with 6) (PMID 26488691). Despite preventive treatment, 1.09% of people developed a symptomatic blood clot in the leg or lungs before leaving hospital (PMID 22253396). Infection of the joint replacement is uncommon but serious and usually needs further surgery; in a large study of older patients in the United States it occurred in 1.55% of patients within two years of surgery (PMID 19669386).
Other possible problems include stiffness, numbness of the skin on the outer side of the incision, wound problems, injury to nearby nerves or blood vessels, and loosening or wear of the components over time, which may need a revision knee replacement. In the registry data above, 17.7% of knee replacements had been revised by 25 years (PMID 30782341). There are also risks from the anaesthetic, which your anaesthetist will discuss with you.
This is why it is important for us to discuss the reason for surgery beforehand, optimise treatment before surgery and establish realistic expectations about recovery and long-term outcomes. The warning signs to look out for after surgery are listed below.
Preparing for Knee Replacement Surgery in Brisbane

Preparation focuses on health, strength, medications and planning for recovery.
Good preparation can reduce the risk of complications and make recovery easier.
Health optimisation
Before surgery:
- stop smoking or vaping if possible
- optimise diabetes and blood sugar control
- work on general fitness and weight where appropriate
- maintain good nutrition
- tell us about previous blood clots, sleep apnoea, heart or lung problems
- provide a complete list of medications and supplements
Exercise before knee replacement
Maintaining knee movement and strengthening the muscles around the knee before surgery can make early rehabilitation easier.
You do not need to make an arthritic knee pain-free before surgery. The aim is to arrive at surgery as mobile, strong and medically healthy as reasonably possible.
Preparing your home
Arrange help with shopping, meals and transport for the early recovery period. Remove trip hazards and consider where you will sleep, shower and perform your exercises.
Your treating team will also advise which medications should be continued or temporarily stopped.
What to Expect After Total Knee Replacement

Recovery involves early mobilisation followed by progressive rehabilitation and strengthening.
In hospital
Hospital stay is commonly around 1–3 days, although some suitable patients may go home earlier.
You can expect:
- a combination of different types of pain relief
- early walking with physiotherapy
- exercises to restore movement
- measures to reduce the risk of blood clots
First 2–6 weeks
Your first review is primarily to check the incision, pain control and early progress.
Walking usually progresses from a frame or crutches to a stick and eventually independent walking.
Swelling is very common and can remain noticeable for several months. Physiotherapy focuses on restoring movement, strength and a normal walking pattern.
We generally aim for at least 90 degrees of knee flexion by approximately six weeks, although recovery varies between patients.
Driving is commonly avoided for approximately six weeks or until you have adequate strength and control to operate the vehicle safely.
6 weeks to 3 months
You will have a further review to assess your movement and overall recovery.
Pain, walking and everyday activities should progressively improve. Some swelling, warmth and stiffness can still be normal at this stage.
3 to 12 months
Strength, confidence, movement and the appearance of the knee can continue improving for 12 months or longer.
Things to Look Out for After Total Knee Replacement
Increasing pain, wound problems, fever, swelling or breathing symptoms need medical review.
Contact our office, your GP, or seek urgent medical attention if you develop:
Possible infection
- increasing redness or warmth around the incision
- increasing pain after initially improving
- persistent wound leakage or pus
- fever or feeling significantly unwell
Joint replacement infection is uncommon but potentially serious and should be assessed promptly.
Possible blood clot
Seek medical attention for:
- new calf pain or tenderness
- significant one-sided leg swelling
- sudden shortness of breath, chest pain or coughing blood
Sudden breathing symptoms require emergency assessment.
Knee stiffness
If the knee is becoming progressively stiffer or you are struggling to regain movement despite physiotherapy, contact us. Early assessment can be important.
Wound problems
Please contact us for persistent leakage, opening of the incision or rapidly increasing swelling or bruising.
Nerve or circulation problems
Increasing weakness or numbness, a cold or pale foot, or severe escalating pain requires urgent assessment.
Common questions about knee replacement
When do I need a knee replacement?
There is no X-ray threshold that decides this. Knee replacement is worth discussing when arthritis pain limits walking, work, sleep or the activities you value despite a fair trial of exercise, weight management, medication and, where appropriate, injections, and when the X-rays show arthritis advanced enough to explain the symptoms. In a randomised trial, knee replacement followed by non-surgical treatment gave greater pain relief and function at 12 months than non-surgical treatment alone, but with more serious adverse events, which is why the decision is made carefully and together (PMID 26488691). Waiting while the knee is manageable rarely makes the operation harder, so there is usually time to decide. Read more about knee arthritis and when to consider replacement.
What are the alternatives to a total knee replacement?
Before surgery, a structured exercise programme, weight management and medication remain the core treatments, and a corticosteroid injection can help a flare (PMID 31278997). Arthroscopic "clean-out" surgery does not help knee arthritis and is not an alternative (PMID 24369076). If arthritis is confined to one compartment, a partial knee replacement or, in younger active patients with a malaligned leg, a high tibial osteotomy or distal femoral osteotomy may be suitable. For people who are not fit for surgery, radiofrequency ablation of the genicular nerves is an option for pain relief.
How much does a knee replacement cost in Brisbane?
The cost depends on your health fund, your level of cover and the hospital, so it is quoted individually rather than published. If surgery is recommended, you will receive a written estimate of Dr Borshch's fee before you decide, with the Medicare item numbers, so that you can check your rebate with Medicare and your health fund. Hospital, anaesthetist and surgical assistant charges are billed separately by those providers, and the implant is usually covered by your health fund. DVA and WorkCover patients are covered under their schemes. The fees and rebates page explains how this works and what to ask your fund.
How long is recovery after a knee replacement?
Recovery is staged over several months rather than weeks. The rehabilitation after knee replacement page sets out what to expect at each stage, from the day of surgery to a year.
Summary
Total knee replacement is an effective operation for advanced knee arthritis that has not responded to non-surgical treatment. It is usually recommended when the expected benefits outweigh the risks for that person. Please discuss your symptoms, your goals and your X-rays with your knee surgeon so that the options, including non-surgical care and partial knee replacement, are considered together.
In this section
Articles in this section
- Am I Too Young for a Knee Replacement?
- Can a Good Knee Replacement Still Hurt?
- Do Modern Knee Replacements Feel More Natural?
- Do Orthopaedic Implants Stay in Forever?
- Full knee replacement vs Partial. Which is best?
- Jiffy Knee Replacement: Claims, Evidence and Questions
- Numbness After Knee Replacement: is it normal?
- Travelling with Orthopaedic Implants: Navigating Airport Security
General information only. The information on this page is general in nature and does not replace individual medical advice. All surgery carries risks, and results vary between patients. Please discuss your own circumstances with your treating practitioner.
Total Knee Replacement Surgery

Dr Alexey Borshch is a specialist orthopaedic surgeon in Brisbane with a particular clinical focus on surgery of the hip, knee and lower limb.
His practice as a Brisbane Orthopaedic surgeon focuses on the assessment and treatment of knee arthritis, as well as performing knee replacement surgery, which includes both total knee arthroplasty and partial knee replacement.
Dr. Borshch completed his medical degree at the University of Queensland before undertaking specialist orthopaedic training in Queensland. He completed the Australian Orthopaedic Association training program and the Royal Australasian College of Surgeons Fellowship Examination in Orthopaedic Surgery. He obtained specialist registration in Orthopaedic Surgery in 2022 and is a Fellow of the Australian Orthopaedic Association.
He offers consultations in Hamilton, Brisbane, and conducts private orthopaedic surgery at Brisbane Private Hospital.