

DAA hip replacement accesses the joint from the front while preserving major muscle attachments.
This page provides general information for patients of Dr Borshch, an orthopaedic surgeon consulting in Hamilton, Brisbane, who are being assessed for or considering Direct Anterior Approach (DAA) hip replacement surgery. Whether the anterior approach suits your hip depends on your anatomy and the state of the joint, which is one of the things a hip surgeon assessment in Brisbane looks at.
I use the Direct Anterior Approach for most suitable primary hip replacements, but not every patient or hip is best treated through this approach.
Your individual treatment should therefore follow advice from your surgeon and treating team.
What is Direct Anterior Approach Hip Replacement?
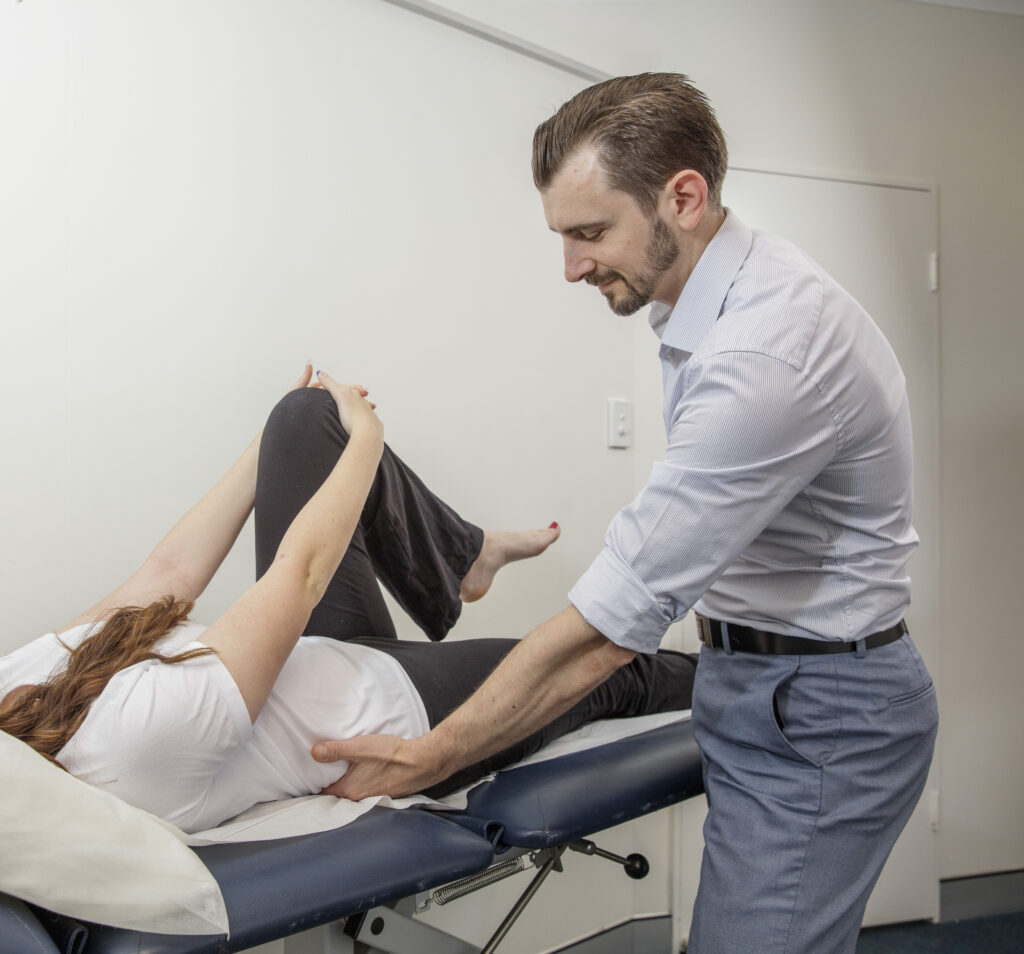
DAA is a way of performing a total hip replacement through the front of the hip.
A total hip replacement, also called total hip arthroplasty (THA), replaces the damaged ball and socket of the hip with artificial joint surfaces.
There are several established ways for an orthopaedic surgeon to reach the hip joint. These include anterior, lateral and posterior approaches.
The Direct Anterior Approach (DAA) reaches the hip through an incision at the front of the joint.
Rather than routinely detaching the major muscles around the hip, the surgeon works through an anatomical interval between muscles to reach the joint. For this reason, DAA is sometimes described as an intermuscular or muscle-sparing approach.
Most established approaches to the hip give similar overall results, and the choice depends mainly on the surgeon’s experience and on the individual patient’s anatomy and health (PMID 36719679).
The anterior approach is now widely used. In Australia, more than 48,000 hip replacements for osteoarthritis were performed through the anterior approach between 2015 and 2022 (PMID 38735543).
The hip replacement itself is not fundamentally different. It still generally consists of:
- a metal socket inserted into the pelvis
- a durable plastic or ceramic liner
- a metal stem inserted into the femur
- a ceramic or metal ball attached to the stem
The difference is primarily how the surgeon reaches the hip to perform the replacement.
Why is the Direct Anterior Approach Used for Hip Replacement?

DAA may aid early recovery, but long-term results are similar to other established approaches.
The main reason for hip replacement is usually advanced hip arthritis causing significant pain, stiffness and loss of function despite appropriate non-operative treatment.
The Direct Anterior Approach is one way of performing that operation.
A potential advantage of DAA is that the hip can be accessed without routinely detaching the major muscles and tendons behind or beside the joint. This may reduce some of the soft-tissue disruption associated with surgery and can contribute to earlier functional recovery in some patients.
A thorough clinical examination by a specialist and modern imaging, such as X-rays, help confirm that hip arthritis is the cause of the symptoms and show the shape of the hip, which also guides the choice of approach.
Is the anterior approach suitable for everyone?
I try to use the Direct Anterior Approach for most patients undergoing primary total hip replacement when I believe it is appropriate.
However, the objective is not to perform every hip replacement through the same incision. The objective is to perform the most appropriate reconstruction for the individual hip.
Factors that can influence the choice of approach include:
- unusual hip or femoral anatomy
- severe deformity
- previous surgery and scars
- retained plates, screws or other metalwork
- significant bone loss
- some fractures around the hip
- complex or revision hip replacement
- the type of specialised implant required
- body shape and soft-tissue distribution
Wound healing is also relevant when selecting an approach. Obesity increases the risk of infection after hip replacement with any approach, and in people with a higher BMI the anterior approach may carry additional wound and infection risk (PMID 34978509).
If I believe another approach provides better access or a more appropriate way to reconstruct the hip, I will recommend that approach instead.
How is Direct Anterior Hip Replacement Surgery Performed?
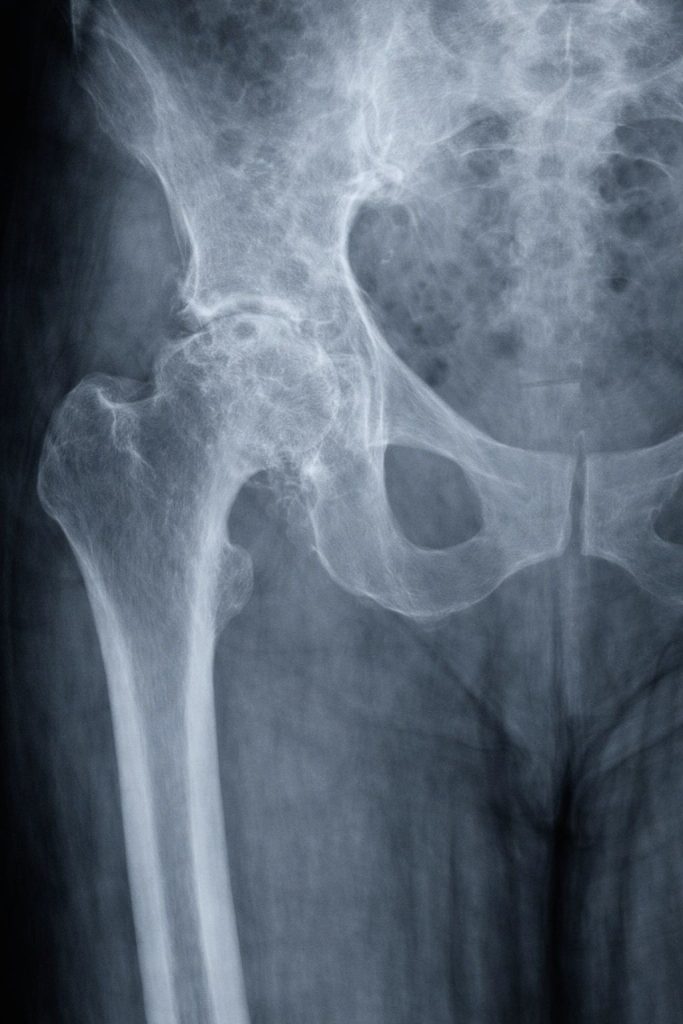
The hip is replaced through an interval between muscles at the front of the joint.
Anaesthetic
An anaesthetic is given, together with additional methods of pain relief around the hip.
Accessing the hip
An incision is made at the front of the hip.
The surgeon carefully works between the muscles to reach the capsule surrounding the hip joint.
This provides access to the arthritic ball and socket without routinely detaching the major muscle groups surrounding the hip.
Removing the damaged hip joint
The damaged femoral head is removed.
The natural hip socket is then prepared to accept the new acetabular component.
Replacing the hip socket
A metal shell is inserted into the pelvis, usually using a press-fit technique.
A highly durable plastic or ceramic liner is placed inside the shell to create the new socket.
Replacing the femoral head
The femur is carefully prepared and a metal stem is inserted into the thigh bone.
A ceramic or metal ball is attached to the stem and placed into the new socket.
The hip is checked for:
- stability
- movement
- implant position
- appropriate leg length
- muscle tension
Closing the incision
The deeper tissues are closed with absorbable sutures.
I generally close the skin with a fine absorbable suture underneath the skin and use a glued mesh over the incision to support the skin during healing.
What are the benefits of anterior hip replacement?

For suitable patients, the anterior approach can make the first weeks of recovery easier, while the new hip gives the long-term benefits of a total hip replacement.
Like any total hip replacement, an anterior hip replacement aims to relieve the pain of advanced hip arthritis and improve walking and everyday function. Hip replacements are long-lasting: national registry data suggest that about 58% of total hip replacements are still working without revision 25 years after surgery (PMID 30782340).
The main advantage of the anterior approach is in early recovery. A meta-analysis of randomised trials found less pain in the first two days and better hip function scores at 6 weeks after anterior compared with posterior hip replacement (PMID 32487060). A 2025 meta-analysis of 17 randomised trials (1,575 patients) similarly found less pain on the first day after surgery and better hip function at 1 month (PMID 41013681).
Patients may also get back on their feet sooner. In a meta-analysis of randomised trials, patients stopped using walking aids earlier after anterior than after posterior hip replacement (PMID 32558261). Two large meta-analyses found a slightly shorter hospital stay than after posterior hip replacement, by 0.31 to 0.33 days on average (PMID 37010580; PMID 40607318).
These early gains come without an increase in the major complications of hip replacement. A 2025 meta-analysis of more than 44,000 patients found similar rates of revision, dislocation and fracture with the anterior and posterior approaches, and a shorter incision with the anterior approach (PMID 40607318).
What are the risks of anterior hip replacement?

Anterior hip replacement carries the risks of any hip replacement, plus some that are specific to the approach, particularly altered skin sensation and wound problems.
An anterior hip replacement is still a total hip replacement, so it carries the general risks of that operation, including infection, blood clots, dislocation, fracture, leg-length difference and ongoing pain. These are explained on the total hip replacement page.
The early advantages do not lead to a better hip in the long term. In a randomised trial with an average of 7.5 years of follow-up, there were no clinically meaningful differences in outcomes, complications, reoperations or revisions between anterior and mini-posterior hip replacement (PMID 38735544). Hip function scores from 3 months onwards were also similar in a meta-analysis of randomised trials (PMID 32487060).
The operation takes longer. On average, anterior hip replacement took 13.74 to 17.38 minutes longer than posterior hip replacement in meta-analyses of randomised trials (PMID 32487060; PMID 37010580).
Numbness or altered sensation
A sensory nerve called the lateral femoral cutaneous nerve passes near the anterior surgical approach.
Irritation or injury to this nerve can produce:
- numbness
- tingling
- burning sensations
- altered sensation over the outer thigh
This generally affects sensation rather than muscle strength.
It is the most common complication specific to the anterior approach. In studies that looked specifically for it, between 14.8% and 81% of patients (31% on average) had symptoms from this nerve after surgery (PMID 33962046). Nerve injury was more common after anterior than after posterior or lateral hip replacement in meta-analyses of randomised trials (PMID 32558261; PMID 41013681).
Symptoms may improve over time, although an area of altered sensation can persist in some patients.
Wound problems
The anterior incision is located near the hip crease, so wound care is particularly important. A systematic review of 35,300 anterior hip replacements found superficial wound opening or leakage in 1.41%, superficial wound infection in 1.34% and delayed wound healing in 1.15% of patients, and most of these were managed with local wound care (PMID 42224471). Obesity and female sex were the most frequently reported risk factors.
Fracture
Fracture of the thigh bone (femur) can occur during any hip replacement. Preparing the femur through an anterior approach is technically demanding, particularly during a surgeon’s learning curve or in difficult anatomy. In Dutch registry data, the risk of revision was 64% higher for a surgeon’s first 50 anterior hip replacements, and levelled off after about 100 operations (PMID 36173140).
The choice of approach should therefore consider patient anatomy as well as surgeon experience.
How Should I Prepare for DAA Hip Replacement in Brisbane?

Optimising your health, strength and home can make early recovery easier.
Health preparation
Before surgery:
- stop smoking or vaping if possible
- optimise diabetes and blood sugar control
- improve general fitness and weight where appropriate
- maintain good nutrition
- provide a complete list of medications and supplements
- tell us about blood-thinning medications
- tell us about previous blood clots, heart or lung conditions and sleep apnoea
- tell us about previous operations or injuries around the hip
Prehabilitation
Maintaining general fitness and strengthening the muscles around the hips and legs can help prepare you for recovery.
You do not need to make an arthritic hip pain-free before surgery. The aim is to arrive at surgery as mobile, strong and medically healthy as reasonably possible.
Preparing your home
Arrange help with shopping, meals and transport during early recovery. Remove loose rugs and other trip hazards and make sure frequently used items are easy to reach.
Because Brisbane has a warm and humid climate, particularly during summer, consider making sure you have access to a cool, comfortable and preferably air-conditioned environment during early recovery. Apart from making recovery more comfortable, published research has found an association between warmer weather and higher rates of surgical-site infection (PMID 34422523).
Keeping yourself comfortable and your surgical dressing clean and dry is therefore particularly important during Brisbane's warmer months.
What Should I Expect After Direct Anterior Hip Replacement?
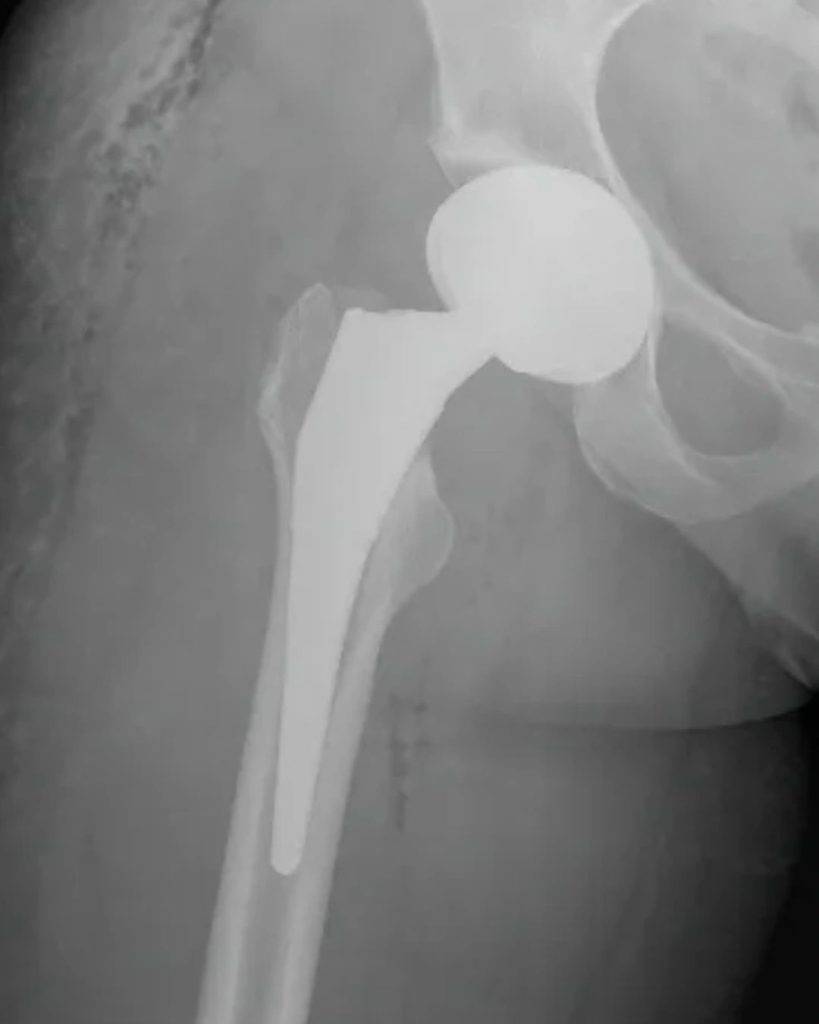
Walking starts early, while strength and endurance continue improving for months.
In hospital
One of the priorities following hip replacement is early mobilisation.
You can expect:
- several different forms of pain relief
- standing and walking with physiotherapy
- exercises to restore strength and movement
- measures to reduce blood-clot risk
- a frame or crutches initially where required
First 2 weeks
Walking generally begins immediately and progresses according to comfort, strength and confidence.
Swelling and bruising around the hip and thigh are common.
Physiotherapy focuses on safe walking and simple strengthening exercises. The incision should be kept clean and dry while it heals.
2–6 weeks
Walking aids can progressively be reduced as strength and confidence improve.
Do not rush to stop using a walking aid if this causes a significant limp.
Driving should resume only when you can safely control the vehicle, perform an emergency stop and are no longer affected by medication that impairs driving.
6 weeks–3 months
Most patients notice substantial improvement in everyday activities.
Strength and endurance continue to improve.
The early recovery differences reported between surgical approaches become less apparent over time, and hip function scores at later follow-up are similar (PMID 32487060).
3–12 months
Strength, balance, endurance and confidence can continue improving for many months.
The long-term objective is not simply to have an “anterior hip replacement”, but a stable, comfortable and well-functioning hip replacement.
Things to Look Out for After Anterior Hip Replacement

Worsening wounds, severe pain, leg swelling or sudden loss of function require assessment.
Contact our office, your GP or seek medical attention if you develop:
Possible infection
- increasing redness or warmth around the incision
- worsening pain after initially improving
- persistent wound leakage or pus
- fever or feeling significantly unwell
Possible blood clot
Seek medical attention for new calf pain or significant one-sided leg swelling.
Sudden shortness of breath, chest pain or coughing blood requires emergency assessment.
Wound problems
Persistent leakage, opening of the incision or increasing redness should be assessed.
Keeping the anterior incision clean and dry, particularly within the hip crease, is important during early healing.
Hip dislocation
Dislocation can occur after any hip replacement.
Sudden severe hip pain, inability to move the leg or a leg appearing shortened or abnormally rotated requires urgent assessment.
Nerve symptoms
Some altered sensation around the outer thigh can occur following DAA.
Please let us know if numbness, burning pain or other nerve symptoms are severe or worsening.
Nerve or circulation problems
Increasing muscle weakness, extensive new numbness, a cold or pale foot, or severe escalating pain requires urgent assessment.
Summary
Anterior hip replacement is a way of performing a total hip replacement through the front of the hip, without routinely detaching the major muscles. For suitable patients it can make early recovery easier, while long-term results are similar to other established approaches. It is usually recommended when the expected benefits outweigh the risks for that person. Please discuss your symptoms, your goals (for example walking, work or sport) and your X-rays with your hip surgeon so that the options, including the most suitable approach for your hip, are considered together.
General information only. The information on this page is general in nature and does not replace individual medical advice. All surgery carries risks, and results vary between patients. Please discuss your own circumstances with your treating practitioner.
Direct Anterior Approach Hip Replacement
Dr Alexey Borshch is a specialist orthopaedic surgeon in Brisbane with a particular clinical focus on surgery of the hip, knee and lower limb.
His practice as a Brisbane Orthopaedic Surgeon focuses on the assessment and treatment of hip arthritis and hip injuries, mainly performing hip replacement and revision hip replacement surgery.
Dr. Borshch completed his medical degree at the University of Queensland before undertaking specialist orthopaedic training in Queensland. He completed the Australian Orthopaedic Association training program and the Royal Australasian College of Surgeons Fellowship Examination in Orthopaedic Surgery. He obtained specialist registration in Orthopaedic Surgery in 2022 and is a Fellow of the Australian Orthopaedic Association.
He offers consultations in Hamilton, Brisbane, and conducts private orthopaedic surgery at Brisbane Private Hospital.