

This page provides general information for patients of Dr Borshch, an orthopaedic surgeon consulting in Hamilton, Brisbane, who are being assessed for or considering revision hip replacement surgery. New pain, instability or loosening in a previously replaced hip is a common reason to see a hip surgeon in Brisbane, and investigation comes before any decision about further surgery.
Your individual condition and treatment plan may be different, so this information should be used alongside advice from your surgeon and treating team.
What is Revision Hip Replacement Surgery?

Revision surgery replaces one or more parts of an existing hip replacement.
A revision hip replacement, also called revision total hip arthroplasty (revision THA), is an operation performed when an existing hip replacement develops a problem that requires further surgery.
A hip replacement usually consists of:
- a metal socket fixed into the pelvis
- a plastic or ceramic liner
- a metal stem inserted into the femur
- a ceramic or metal ball attached to the stem
Revision surgery does not necessarily mean replacing the entire hip replacement. Depending on the problem, surgery may involve changing:
- the ball or liner
- the acetabular component (socket)
- the femoral component (stem)
- several or all of the components
Replacing all the components is the most common type of revision. In a US national study of more than 258,000 revision hip replacements, all components were replaced in 41.8% of operations (PMID 28336249).
Revision hip replacement is generally more complex than a first hip replacement because there may be scar tissue, bone loss, infection, muscle damage, fracture or difficulty removing existing implants.
Specialised revision implants, bone graft or other reconstruction techniques may therefore be required. Where bone has been lost around the socket, modern highly porous metal cups, often combined with porous metal augments (shaped blocks that fill bone defects), can successfully reconstruct most revised sockets (PMID 38412446).
Why is Revision Hip Replacement Surgery Done?

Surgery is considered when a hip replacement has a correctable mechanical or biological problem.
Modern hip replacements can function successfully for many years, but problems can occasionally develop.
Common reasons for revision include:
- aseptic loosening – an implant becomes loose without infection
- infection around the hip replacement
- recurrent dislocation or instability
- fracture around the hip replacement
- wear of the bearing surfaces
- bone loss around the implants
- implant breakage or mechanical failure
- adverse reactions to wear debris or particular implant materials
A 2024 analysis of national joint replacement registries from seven countries found that the most common reasons for revision hip replacement were aseptic loosening (35.1%), deep infection (18.2%), dislocation or instability (15.9%) and fracture around the implant (periprosthetic fracture, 11.4%) (PMID 38795186).
Importantly, pain after hip replacement does not automatically mean that revision surgery is required.
Pain can arise from the replacement itself, but can also come from muscles, tendons, the lower back, nerves or other structures.
For example, a systematic review of iliopsoas impingement (irritation of the hip flexor tendon by the hip replacement) found that selected patients can be treated with non-operative management or iliopsoas tendon surgery rather than revision of the hip replacement (PMID 31147246).
The first objective is therefore to establish why the hip is painful or failing and whether revision surgery is likely to correct that problem. This relies on a careful clinical examination by a specialist together with modern imaging, and sometimes blood tests or a sample of fluid from the hip.
How is Revision Hip Replacement Surgery Performed?
The operation is individually planned around the implants, bone loss and reason for failure.
Every revision hip replacement is different.
Planning commonly involves X-rays and may also include CT scans, blood tests, joint aspiration or other investigations.
Anaesthetic
The operation is performed under anaesthetic, together with additional methods of pain relief. Your anaesthetist will discuss the anaesthetic with you before surgery.
Accessing and assessing the hip
The existing hip replacement is exposed and carefully assessed.
The operation may involve examining:
- fixation of the socket
- fixation of the femoral stem
- implant position
- bone loss
- hip stability
- muscles and tendons
- bearing-surface wear
- possible infection
Removing existing implants
Sometimes only the ball and liner need to be changed.
If the socket or stem is loose, it can usually be removed relatively easily. Removing a well-fixed implant can be considerably more difficult.
Specialised instruments may be required to remove the component while preserving as much healthy bone as possible.
Occasionally, the femur needs to be carefully opened to remove a well-fixed stem and then reconstructed around the new implant.
Reconstructing the hip socket
Revision surgery may reveal areas where bone has been lost around the socket.
Depending on the amount and location of remaining bone, reconstruction may involve:
- a larger acetabular component
- additional screws
- bone graft
- porous metal augments
- specialised revision cups
- more complex reconstruction systems for major bone loss
A 2024 review of acetabular bone loss in revision hip replacement describes how the amount and pattern of remaining pelvic bone guide the reconstruction required (PMID 38412446).
Reconstructing the femur
If the femoral component needs revision, a specialised stem may be required.
Revision stems are often longer than standard hip replacement stems, allowing fixation in healthy bone further down the femur.
Metal cables or other fixation may sometimes be required around the femur, particularly where bone is thin, damaged or fractured.
Improving hip stability
Instability can be an important problem following revision hip replacement.
Treatment can involve correcting implant position, restoring appropriate muscle tension, changing femoral head size or using specialised bearing surfaces.
One option in selected patients is a dual-mobility bearing, which is designed to increase the effective range before the hip can dislocate.
A 2024 systematic review and meta-analysis comparing dual-mobility and fixed-bearing implants found lower rates of revision for dislocation with dual-mobility implants, including in revision hip replacement (PMID 39157170). Longer-term comparative evidence is still developing.
Closing the hip
Once the reconstruction is complete, the deeper tissues are carefully repaired and the incision is closed in layers before a dressing is applied.
Treating an infected hip replacement

Infection may require implant removal, antibiotics and one-stage or staged reconstruction.
Periprosthetic joint infection is an important reason for revision hip replacement.
Investigation can include:
- blood tests
- aspiration of fluid from the hip
- microbiological cultures
- tissue samples taken during surgery
Treatment depends on how long the infection has been present, the organism involved, implant fixation, bone and soft-tissue condition and the patient's overall health.
One-stage revision for infection
In selected circumstances, the infected implants are removed, the hip is thoroughly cleaned and a new hip replacement is inserted during the same operation.
Two-stage revision for infection
In other situations, treatment is performed in stages.
The infected implants are removed and the hip is thoroughly cleaned. A temporary antibiotic-containing spacer may be inserted and antibiotics are given.
The definitive hip replacement is then inserted during a later operation.
An updated systematic review and meta-analysis comparing one-stage and two-stage revision for hip replacement infection found no significant difference in reinfection, mortality, aseptic loosening or overall revision rates between the two strategies in the available comparative studies (PMID 39303283).
This does not mean that both approaches are equally appropriate for every infection. Treatment is individualised according to the organism, implants, bone, soft tissues and patient.
What are the benefits of revision hip replacement?
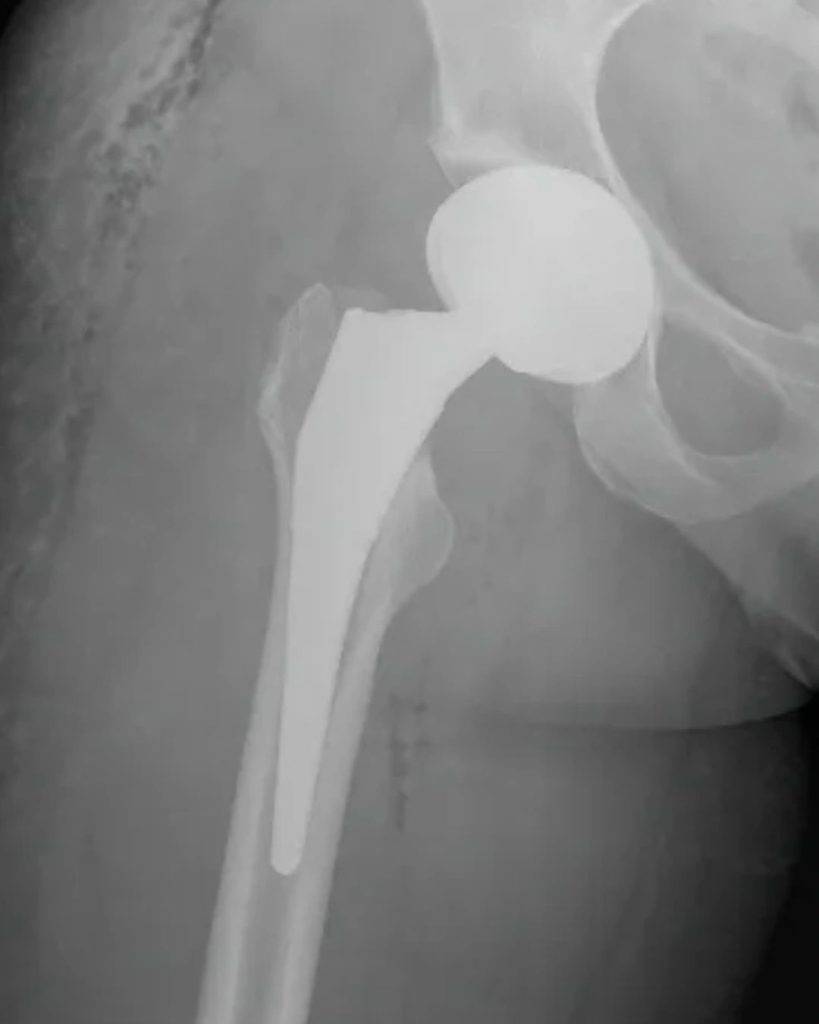
When the cause of the problem can be identified and corrected, revision surgery can relieve pain and improve walking, function and quality of life.
Revision surgery aims to correct the specific problem with the existing hip replacement, such as a loose or worn component, recurrent dislocation, infection or a fracture around the implant, and to restore a stable, well-fixed hip.
Patients having revision surgery can expect a major improvement in function, activity and quality of life (PMID 27886353). In a prospective study of 216 patients having revision for problems other than infection, average scores improved by 30.4 points for hip pain and 22.1 points for physical function one year after surgery (PMID 34554849).
In a registry study of 406 revision hip replacements, 78% of patients reported better hip function one year after surgery and 79% said they would go through the operation again. Pain when walking and moving showed the greatest improvement (PMID 34984475).
Good results are generally achieved whatever the reason for revision. In a study of 647 patients, those with the poorest hip scores before surgery showed the greatest improvement (PMID 35775171).
A revision hip replacement can also last well. In a registry study of 629 revision hip replacements done for reasons other than infection, 86.8% were still working without further revision five years after surgery (PMID 25740025).
What are the risks of revision hip replacement?
Revision surgery is more complex than a first hip replacement, carries higher risks and does not always relieve symptoms.
Complications are more common than after a first hip replacement. In a prospective study of 647 patients at a high-volume centre, the overall complication rate was 35.4%, and 9.7% needed a further revision during at least two years of follow-up (PMID 35775171).
In a large study of older patients in the US Medicare system, complications after revision hip replacement included infection (17.3%), a further revision (15.8%), a blood clot in the veins (venous thromboembolism, 11.1%), dislocation (5.43%), a blood clot in the lungs (pulmonary embolism, 3.24%) and death (2.11%) (PMID 28236550). In that study, 8.13% of patients having revision for a problem other than infection developed a new infection.
Dislocation is one of the most common problems after revision. Across 8 studies of 4,656 revision hip replacements, 9.04% dislocated after surgery, and the risk was higher in patients who had previous instability or two or more earlier revisions (PMID 28043927).
Other possible complications include fracture of the femur or pelvis during surgery, injury to nerves or blood vessels, a difference in leg length, wound-healing problems and the general risks of anaesthesia.
Revision is a major operation. In a study of 596 patients, 1.95% died within two years of revision surgery, rising to 7.45% in patients whose revision was for a fracture around the implant (PMID 33558045).
Results may be less complete than after a first hip replacement
On average, the improvement after revision is smaller, and final pain and function scores are lower, than after a first hip replacement (PMID 27886353). In one study, 24% of patients reported a clinically meaningful worsening in hip function after revision, compared with 4.4% after a first hip replacement (PMID 37271232). In another, nearly half of patients had no improvement, or a worse score, for general physical health one year after revision (PMID 34554849).
Patients often expect more improvement in walking, pain and implant lifespan than they eventually achieve (PMID 38825694). Revision surgery may also not help pain that comes from another source, such as the lower back, tendons or nerves.
Further surgery
There is no single lifespan for a revision hip replacement. Durability depends on:
- the reason for revision
- amount and quality of remaining bone
- infection
- muscle and soft-tissue condition
- implants required
- age and activity
- previous operations
In a registry study of 629 revision hip replacements, 10% needed another revision, and younger patients had a higher risk of re-revision (PMID 25740025). These figures describe groups of patients and cannot predict how long an individual revision hip replacement will last.
Preparing for Revision Hip Replacement

Optimising your health and home is particularly important before complex revision surgery.
Health preparation
Before surgery:
- stop smoking or vaping if possible
- optimise diabetes and blood sugar control
- improve general fitness where appropriate
- maintain good nutrition
- provide a complete list of medications and supplements
- tell us about blood-thinning medications
- tell us about previous infections or wound problems
- tell us about previous blood clots, heart or lung conditions and sleep apnoea
If infection is suspected, additional investigations will usually be required.
Prehabilitation
The amount of exercise possible depends on the problem with your existing hip replacement.
Maintaining general fitness, upper-body strength and strength in the unaffected leg can be particularly useful if crutches or a walking frame will be required after surgery.
Preparing your home
Revision hip replacement recovery may take longer than recovery from a first hip replacement.
Arrange help with meals, shopping and transport. Remove loose rugs and other trip hazards and consider how you will manage stairs, showering and everyday activities.
Because Brisbane has a warm and humid climate, particularly during summer, consider making sure you have access to a cool, comfortable and preferably air-conditioned environment during early recovery. Apart from making recovery more comfortable, published research has found an association between warmer weather and higher rates of surgical-site infection (PMID 34422523).
Keeping yourself comfortable and your surgical dressing clean and dry is therefore particularly important during Brisbane's warmer months.
What Should I Expect After Revision Hip Replacement?

Recovery varies greatly according to how much reconstruction was required.
In hospital
You can expect:
- several different forms of pain relief
- physiotherapy and mobilisation when appropriate
- measures to reduce blood-clot risk
- antibiotics when required
- crutches or a walking frame
Some patients can place full weight through the operated leg relatively early.
Others require restricted or protected weight-bearing while bone graft, fractures or more complex reconstruction heals.
First 2–6 weeks
Walking aids are used as instructed and swelling around the hip and leg is common.
Your early review focuses on wound healing, pain, walking and overall progress.
6 weeks–3 months
Walking, strength and confidence should progressively improve.
Rehabilitation is tailored to the reconstruction performed. Someone having a relatively straightforward ball-and-liner exchange will have a very different recovery from someone requiring extensive reconstruction of the pelvis and femur.
Driving and work should resume according to safe function, medication use and the individual operation rather than a fixed date.
3–12 months
Improvement in strength, walking, pain and confidence can continue for 12 months or longer.
Revision hip replacement often requires more patience than a first hip replacement.
What Should I Look Out for After Revision Hip Replacement?

Wound problems, severe pain, dislocation or breathing symptoms require prompt assessment.
Contact our office, your GP or seek medical attention if you develop:
Possible infection
- increasing redness or warmth around the incision
- worsening pain after initially improving
- persistent wound leakage or pus
- fever, chills or feeling significantly unwell
Possible blood clot
Seek medical attention for new calf pain or significant one-sided leg swelling.
Sudden shortness of breath, chest pain or coughing blood requires emergency assessment.
Hip dislocation
Sudden severe hip pain, inability to move the leg or a leg appearing shortened or abnormally rotated requires urgent assessment.
Wound problems
Persistent leakage, wound opening or rapidly increasing swelling should be assessed promptly.
Fracture or sudden change in function
Sudden severe pain or inability to put weight through the leg after a fall or unexpected movement should be assessed.
Nerve or circulation problems
Increasing weakness or numbness, a cold or pale foot, or severe escalating pain requires urgent medical assessment.
Summary
Revision hip replacement replaces one or more parts of an existing hip replacement that has developed a problem, such as loosening, infection, instability or a fracture around the implant. When the cause can be identified and corrected, it can relieve pain and improve walking and quality of life, although it is more complex than a first hip replacement and carries higher risks. It is usually recommended when the expected benefits outweigh the risks for that person. Please discuss your symptoms, your goals and your investigations with your hip surgeon so that the options, including whether revision is likely to help, are considered together.
General information only. The information on this page is general in nature and does not replace individual medical advice. All surgery carries risks, and results vary between patients. Please discuss your own circumstances with your treating practitioner.
Revision Hip Replacement Surgery
Dr Alexey Borshch is a specialist orthopaedic surgeon in Brisbane with a particular clinical focus on surgery of the hip, knee and lower limb.
His practice as a Brisbane orthopaedic surgeon includes primary and revision hip replacement surgery, as well as the assessment of painful or problematic existing hip replacements.
Revision hip replacement can range from changing one component of an existing replacement to complex reconstruction involving the socket, femur, bone graft, specialised revision implants or treatment of infection.
Dr. Borshch completed his medical degree at the University of Queensland before undertaking specialist orthopaedic training in Queensland. He completed the Australian Orthopaedic Association training program and the Royal Australasian College of Surgeons Fellowship Examination in Orthopaedic Surgery. He obtained specialist registration in Orthopaedic Surgery in 2022 and is a Fellow of the Australian Orthopaedic Association.
He offers consultations in Hamilton, Brisbane, and conducts private orthopaedic surgery at Brisbane Private Hospital.