

What is an MPFL reconstruction?
The medial patellofemoral ligament (MPFL) is a band of tissue on the inner side of the knee. It runs from the end of the thigh bone (femur) to the inner edge of the kneecap (patella), is about 55 mm long, and is the main restraint that stops the kneecap from sliding out towards the outer side of the knee (PMID 12893142). When the kneecap dislocates laterally (to the outside), the MPFL is torn in more than 90% of cases (PMID 26602152), and if it heals loose or does not heal, the kneecap can keep dislocating.
An MPFL reconstruction replaces the torn ligament with a new one, usually made from a tendon taken from your own leg, such as a hamstring tendon or part of the quadriceps tendon (PMID 41333627). Through small incisions on the inner side of the knee, the graft is fixed to the kneecap and to the thigh bone at the attachment points of the original ligament. It works like a rein along the inner side of the kneecap, holding it in its groove as the knee starts to bend. In laboratory studies, cutting the MPFL greatly increased how far the kneecap could be pushed outwards, and reconstructing it brought this back to the normal range (PMID 10788776). It is one of the main operations used for patella stabilisation, and it can be combined with a tibial tubercle medialising osteotomy or a tibial tubercle distalising osteotomy when the shape or alignment of the bones also contributes.
A thorough clinical examination by a specialist and modern imaging helps confirm the diagnosis and plan surgery. MRI shows the injury to the MPFL and any damage to the cartilage, and X-rays, CT or MRI show other factors that affect kneecap stability, such as the height of the kneecap, the shape of its groove and the position of the tibial tubercle (PMID 26602152; PMID 39763469). A knee arthroscopy is often done at the start of the operation to assess the joint and treat any other problems found (PMID 35347375).
What are the benefits of an MPFL reconstruction?
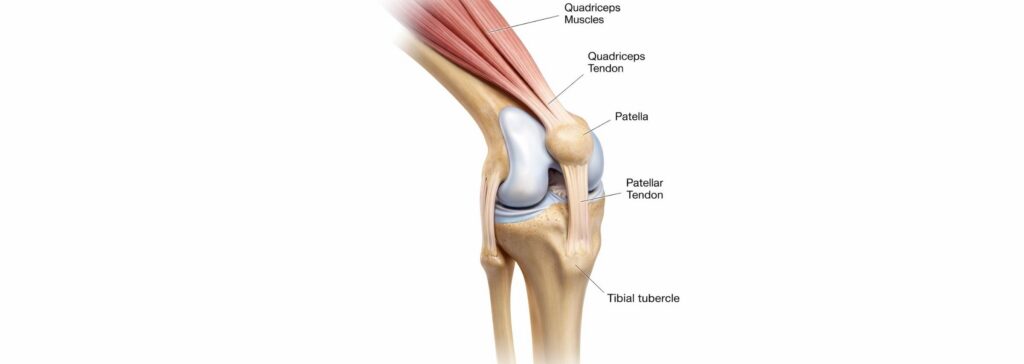
The main benefit is a more stable kneecap. In a randomised trial of young people with repeated kneecap dislocations, 16.7% of those who had an MPFL reconstruction still had a feeling of instability at three years, compared with 53.6% of those treated with rehabilitation without reconstruction (PMID 41655186). At one year, the difference was 6.7% compared with 41.9% (PMID 35347375).
Most people return to sport. A review of 930 patients found that 92.8% returned to sport, on average about 6.7 months after surgery, and 71.3% returned to the same or a higher level than before. Knee function scores improved from an average of about 60 to 90 out of 100 (PMID 33720789).
An MPFL reconstruction on its own is a soft-tissue operation. In a review of 1,389 patients, it had lower complication and failure rates than operations on the bone for kneecap instability, such as a tibial tubercle osteotomy or reshaping of the groove (trochleoplasty) (PMID 38844012). Good results have been reported with both hamstring and quadriceps tendon grafts (PMID 41333627).
What are the risks of an MPFL reconstruction?
Complications can occur. An early review of 629 knees reported complications in 26.1%, ranging from minor to major, including fracture of the kneecap, failure of the graft, ongoing instability, loss of knee bending, wound problems and pain, and 26 patients needed further surgery (PMID 22679297). More recent reviews have reported lower rates, about 8.8% overall (PMID 33720789), and between 0% and 14.7% across studies (PMID 38844012).
Fracture of the kneecap is a specific risk when tunnels or sockets are drilled into the kneecap to hold the graft. Rates of 0% to 17% have been reported with these techniques, while none were reported in studies that fixed the graft to the surface of the bone (PMID 31000392).
The kneecap can still dislocate again. In children and adolescents, instability recurred in 5.1% (PMID 34064244), and redislocation rates of up to 21% have been reported in some studies (PMID 31000392). The risk is higher when there are other anatomical factors, such as a high-riding kneecap (patella alta) or an abnormally shaped groove, which may need to be treated with an additional bony procedure (PMID 39763469).
Surgery mainly improves stability, and it does not always improve how the knee feels in everyday use. In the randomised trial, knee function scores and activity levels after reconstruction were similar to those of people treated with rehabilitation alone (PMID 41655186; PMID 35347375). Some people do not return to sport, or return at a lower level (PMID 33720789). In young patients, infection, wound problems and stiffness were each reported in fewer than 2 in 100 knees (PMID 34064244). Other risks are those of knee surgery in general, such as blood clots, discomfort where the tendon graft was taken, and numbness around the incisions.
Summary
An MPFL reconstruction replaces the torn ligament on the inner side of the kneecap with a tendon graft, so that the kneecap stays in its groove and is less likely to dislocate. It is mainly used for people with repeated kneecap dislocations, either on its own or together with a bony procedure when imaging shows other contributing factors. It is usually recommended when the expected benefits for you outweigh the risks. You should discuss your symptoms, your scans and your goals, including plans for sport and work, with your knee surgeon so that you can consider the options and indications for surgery together.
General information only. The information on this page is general in nature and does not replace individual medical advice. All surgery carries risks, and results vary between patients. Please discuss your own circumstances with your treating practitioner.