
What is a quadriceps tendon autograft ACL reconstruction?
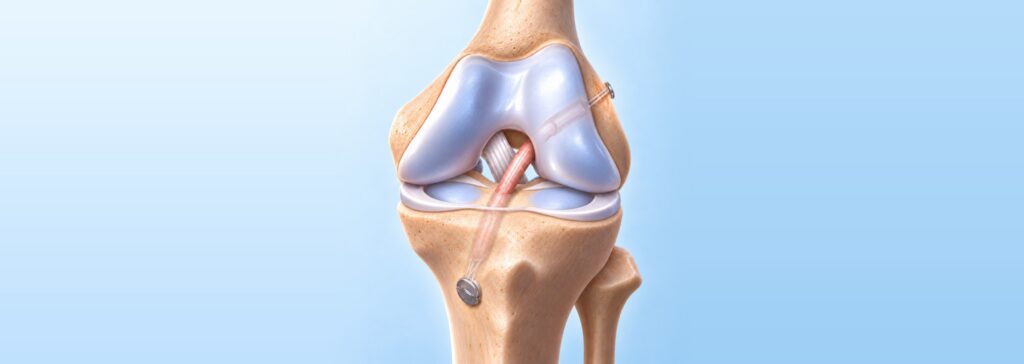
The anterior cruciate ligament (ACL) is one of the main ligaments inside the knee. It helps keep the shin bone (tibia) from sliding forwards and rotating under the thigh bone (femur), especially during pivoting and changing direction. A quadriceps tendon autograft ACL reconstruction replaces a torn ACL with a new ligament made from part of your own quadriceps tendon ("autograft" means tissue taken from your own body). The quadriceps tendon is the thick, strong tendon just above the kneecap (patella) that connects the large muscles at the front of the thigh to the kneecap. A strip from its central part is taken through an incision above the kneecap, either as tendon only (all-soft-tissue graft) or with a small block of bone from the top of the kneecap (bone-block graft) (PMID 41836005). Studies of its anatomy, structure and strength support its use as an ACL graft (PMID 25543249), and surveys of knee surgeons show a recent rise in its use for ACL reconstruction (PMID 41274559).
The operation is minimally invasive and is done with a knee arthroscopy (a camera inserted through small incisions). Tunnels are drilled in the thigh bone and the shin bone at the attachment points of the original ACL, and the graft is passed through them and fixed in place, so that it sits in the same position and orientation as the ligament it replaces. Over the following months, the graft heals into the bone tunnels. It is one of the graft options for ACL reconstruction, alongside the hamstring autograft and the patellar tendon graft, and in some knees it is combined with a lateral extra-articular tenodesis to add control of rotation.
A thorough clinical examination by a specialist and modern imaging helps confirm the diagnosis. Examination tests such as the Lachman test and the pivot shift test are accurate for detecting an ACL tear (PMID 26854045), and MRI shows the ligament and any injury to the meniscus and cartilage. Some meniscus tears are hard to see on MRI, so the arthroscopy at the start of the operation is also used to assess the joint and treat any other injuries found (PMID 31684739).
What are the benefits of a quadriceps tendon autograft ACL reconstruction?
A quadriceps tendon graft restores a stable knee with results similar to those of the other main grafts. A review of 12 randomised trials (636 patients) found no differences between quadriceps tendon, hamstring and patellar tendon grafts in graft failure, knee looseness or patient-reported knee scores (PMID 40679231). In a randomised trial of 99 adults, quadriceps tendon and hamstring grafts gave similar knee function, stability and rates of further surgery at two years (PMID 31704697).
It causes fewer problems where the graft is taken. Two years after surgery, symptoms at the graft site were present in 27% of people with a quadriceps tendon graft, compared with 50% of those with a hamstring graft (PMID 31704697). Across 24 studies, problems at the graft site, such as pain at the front of the knee or difficulty kneeling, were less common than with both patellar tendon and hamstring grafts (PMID 34494906), and a review of 21 randomised trials found 88% lower odds of these problems than with patellar tendon grafts (PMID 37000243).
The quadriceps tendon provides a thick, reliable graft. Across studies of 3,633 patients, the average graft diameter was 8.9 mm, and it was similar to or larger than a hamstring graft in most studies (PMID 39686764). Because the hamstring tendons are left in place, a review of 17 studies found stronger knee bending (flexion) strength after a quadriceps tendon graft than after a hamstring graft (PMID 41394460).
What are the risks of a quadriceps tendon autograft ACL reconstruction?
Some weakness of the quadriceps (the muscles that straighten the knee) can remain. Compared with hamstring grafts, quadriceps tendon grafts led to weaker knee straightening (extension) strength in 9 of 13 studies (PMID 41394460), and in the randomised trial, hop test symmetry between the legs was 91% after a quadriceps tendon graft compared with 97% after a hamstring graft (PMID 31704697).
The new graft can fail or tear again. In the Danish knee ligament registry, 4.7% of quadriceps tendon grafts needed revision surgery within two years, compared with 2.3% of hamstring grafts and 1.5% of patellar tendon grafts, and the knee was on average slightly looser (PMID 31641810). The revision rate was higher in clinics that performed this operation less often (6.4% compared with 2.9%) (PMID 32886156). In a high-volume centre, graft failure (re-tear or a loose graft) occurred in 9.4% of people within two years, and 5.0% needed further surgery for a cyclops lesion (a nodule of scar tissue at the front of the graft that can block full straightening of the knee) (PMID 34102074).
Other problems at the graft site can occur. Across 44 studies, pain at the front of the knee was reported in 7% to 8% of people, graft failure in 6% and infection in about 1%, with similar rates for bone-block and all-soft-tissue grafts (PMID 41836005). Much of the evidence for this graft is recent, and the certainty of some comparisons is still low (PMID 41836005). Surgery does not guarantee a return to the previous level of sport. Other risks are those of knee surgery in general, such as stiffness, blood clots, ongoing pain or swelling, numbness around the incision, and injury to the cartilage or meniscus in the future.
Summary
A quadriceps tendon autograft ACL reconstruction replaces a torn ACL with a strip of your own quadriceps tendon from just above the kneecap, placed through small tunnels in the thigh bone and shin bone, to restore stability to the knee. It is usually recommended when the expected benefits for you outweigh the risks. You should discuss your symptoms, your scans and your goals, including plans for sport and work, with your knee surgeon so that you can consider the graft options and the indications for surgery together.
General information only. The information on this page is general in nature and does not replace individual medical advice. All surgery carries risks, and results vary between patients. Please discuss your own circumstances with your treating practitioner.