
What is a one-stage revision ACL reconstruction?
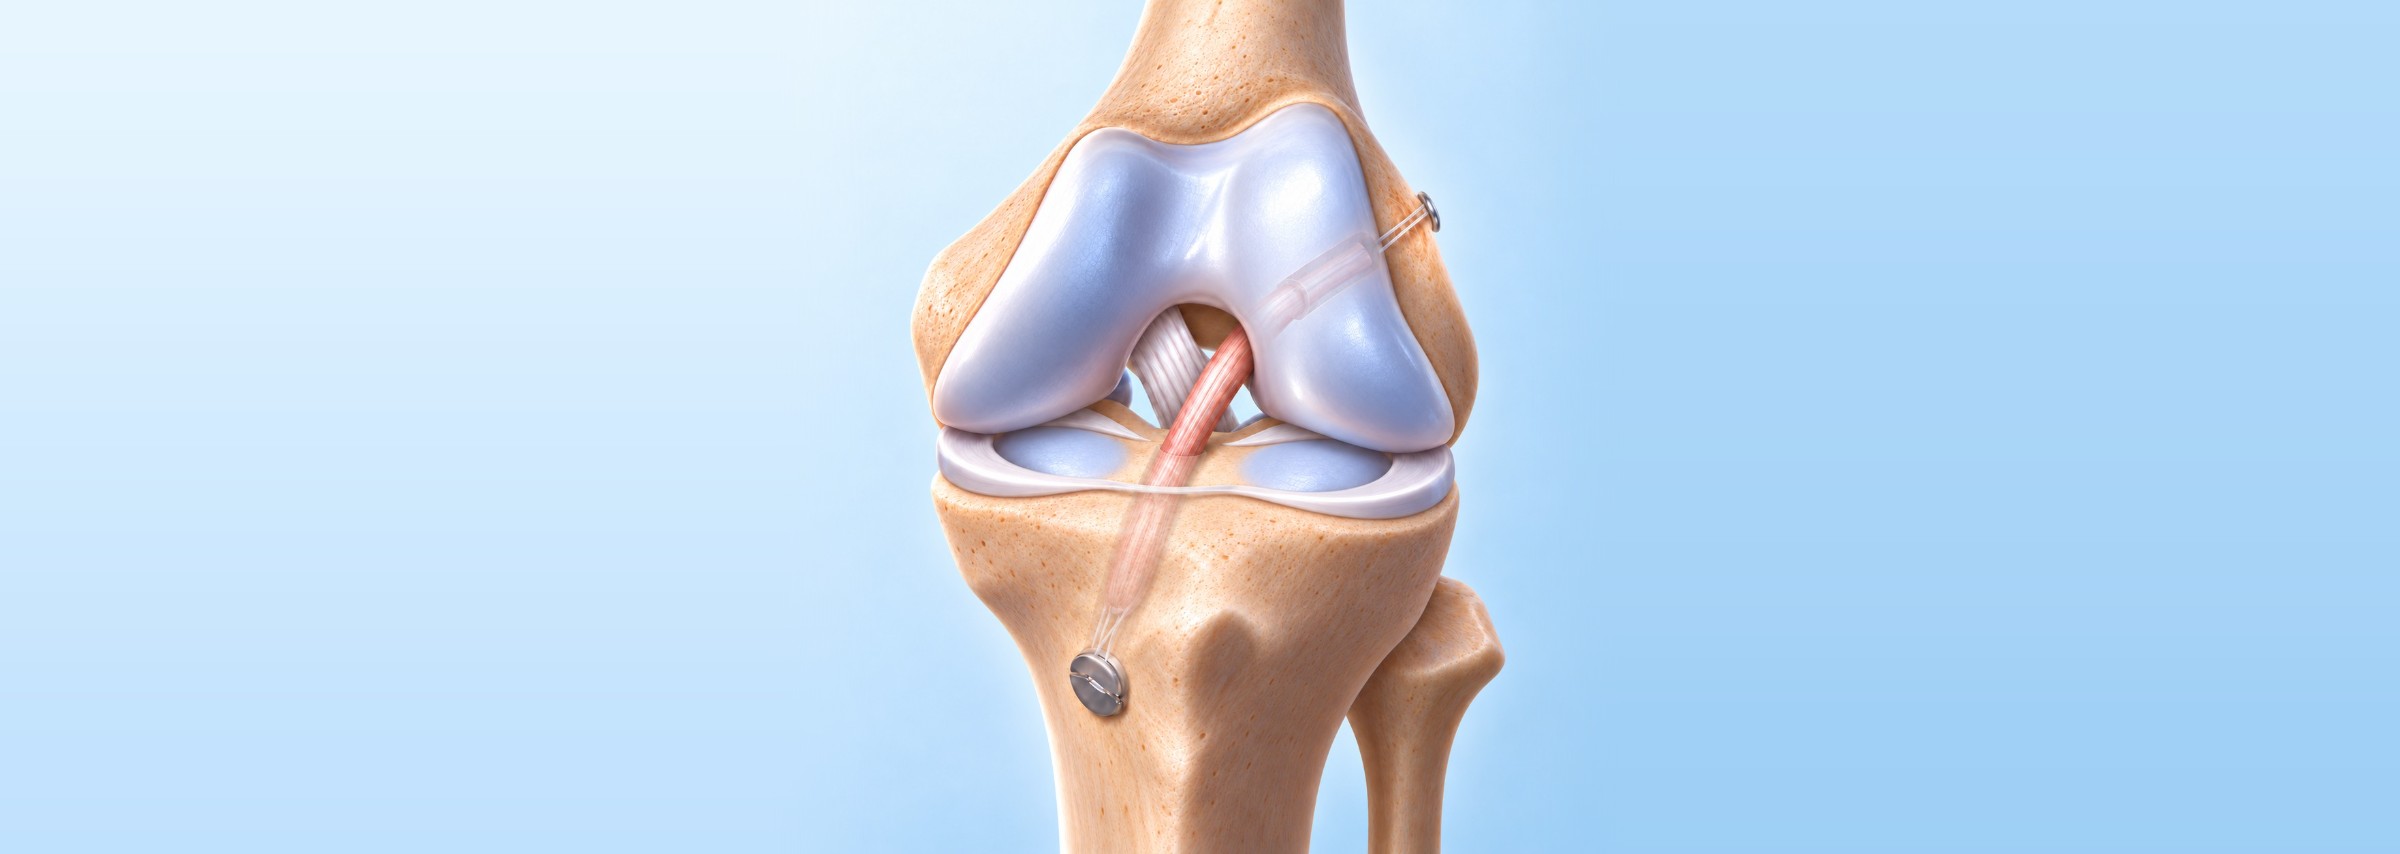
The anterior cruciate ligament (ACL) is one of the main ligaments inside the knee. It helps keep the shin bone (tibia) from sliding forwards and rotating under the thigh bone (femur). After an ACL reconstruction, the new ligament (graft) can stretch or tear again. A revision ACL reconstruction is an operation to replace the failed graft with a new one. In a one-stage (single-stage) revision, this is done in a single operation. It is possible when the bone tunnels from the first operation can be reused, or when new tunnels can be drilled in a slightly different direction that avoids them (PMID 39816950).
Like the first operation, it is minimally invasive and is done with a knee arthroscopy (a camera inserted through small incisions). The old graft and any screws that are in the way are removed, and the new graft is passed through the tunnels and fixed in place, so that it sits in the same position and orientation as the natural ACL. The new graft is often taken from your own body (autograft), such as the patellar tendon, the quadriceps tendon or the hamstring tendons, depending on which graft was used before. In some knees a lateral extra-articular tenodesis is added to help control rotation. When the old tunnels are too wide or are placed where they cannot be worked around, they are first filled with bone graft and the new ligament is placed in a second operation some months later; this is called a two-stage revision (PMID 39816950; PMID 42631105).
A graft can fail for several reasons. In a large North American study of 460 revision operations, the surgeons judged the cause to be a new injury in 32% of knees, a technical factor such as the position of the tunnels in 24%, failure of the graft to heal in 7%, and a combination of factors in 37%. Damage to the meniscus or cartilage was found in 90% of these knees (PMID 20889962).
A thorough clinical examination by a specialist and modern imaging helps confirm the diagnosis and plan the operation. Examination tests such as the pivot shift test and an MRI scan show that the graft has failed and whether the meniscus and cartilage are injured, and a CT scan shows the position and width of the old tunnels, which helps decide whether one stage is possible (PMID 42631105; PMID 39816950). The arthroscopy at the start of the operation is also used to assess the joint and treat other injuries found.
What are the benefits of a one-stage revision ACL reconstruction?
A one-stage revision restores stability to the knee and improves knee function. In a study of 1,205 people having revision ACL reconstruction, knee function and symptom scores improved significantly two years after surgery (PMID 25274353). In a series of 409 people who all had a one-stage revision, the knee became much more stable and, on average, patients reported knee scores at a level that people generally consider satisfactory (PMID 33689510).
It needs only one operation and one recovery. This avoids the extra surgery, time away from work and sport, and inconvenience of a two-stage revision (PMID 39816950). In the Danish knee ligament registry (1,574 revision operations), one-stage revision gave the same knee stability and the same low rate of further revision at two years (about 3%) as two-stage revision (PMID 38226705). In another study, people who had a one-stage revision had less pain at the front of the knee and better knee scores than those who had a two-stage revision (PMID 39815325).
Most active people return to sport. In a review of 52 studies (3,814 patients), 78% returned to sport after revision ACL reconstruction, and the return rate was higher (91%) when a lateral extra-articular procedure was added (PMID 41572915). Adding a lateral extra-articular procedure to a revision also reduced the risk of the new graft failing by about half, without increasing complications (PMID 38294248). Using your own tissue for the new graft gave better sports function and a lower risk of the graft tearing again than using donor tissue (PMID 25274353).
What are the risks of a one-stage revision ACL reconstruction?
Results are generally not as good as after a first ACL reconstruction. In a review of 21 studies (863 patients followed for at least two years), the new graft failed or the knee remained loose in 13.7% of people, three to four times the rate after a first reconstruction, and patient-reported knee scores were lower (PMID 22438002).
Not everyone returns to their previous level of sport. In the review of 3,814 patients, 48% returned to the same level of competition as before; the most common reasons for not returning were fear of another injury, knee pain and ongoing instability (PMID 41572915).
A one-stage revision is not possible in every knee. If the old tunnels are too wide or poorly placed, a two-stage revision may be needed instead (PMID 39816950). In one single-centre study, the new graft failed more often after a one-stage revision than after a two-stage revision, although the large Danish registry study found no difference in further revision between the two (PMID 39815325; PMID 38226705).
Damage to the meniscus and cartilage affects the long-term result. In a study of 1,234 people followed for six years after revision ACL reconstruction, those with meniscus or cartilage damage had poorer knee scores, especially if part of the inner (medial) meniscus had been removed or the cartilage behind the kneecap was damaged (PMID 36734487). Infection is rare: it occurred in 0.6% of 1,423 revision operations, and was more likely when donor tissue was used and in people with diabetes (PMID 33002248). Other risks are those of knee surgery in general, such as stiffness, blood clots, ongoing pain or swelling, and numbness or pain where the graft was taken.
Summary
A one-stage revision ACL reconstruction replaces a failed ACL graft with a new graft in a single operation, when the tunnels from the first operation can be reused or avoided. It is usually recommended when the expected benefits for you outweigh the risks. You should discuss your symptoms, your scans and your goals, including plans for sport and work, with your knee surgeon so that you can consider the options, including whether one or two stages are needed, and the indications for surgery together.
General information only. The information on this page is general in nature and does not replace individual medical advice. All surgery carries risks, and results vary between patients. Please discuss your own circumstances with your treating practitioner.