
What is a bone-patellar tendon-bone autograft ACL reconstruction?
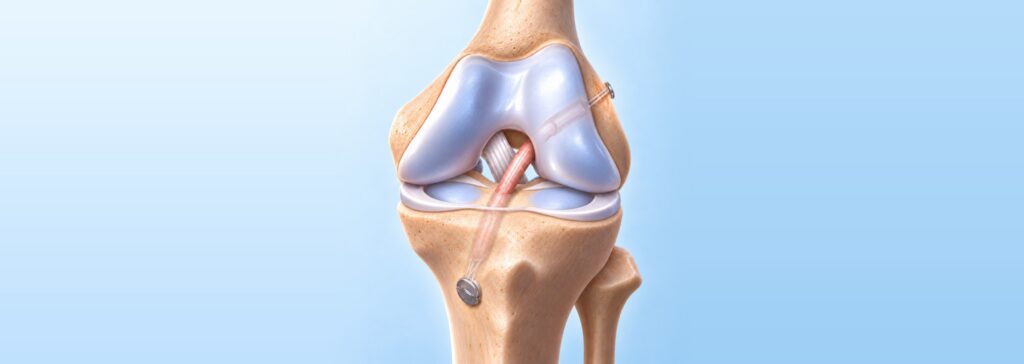
The anterior cruciate ligament (ACL) is one of the main ligaments inside the knee. It helps keep the shin bone (tibia) from sliding forwards and rotating under the thigh bone (femur), especially during pivoting and changing direction. A bone-patellar tendon-bone (BPTB) autograft ACL reconstruction replaces a torn ACL with a new ligament made from the central third of your own patellar tendon ("autograft" means tissue taken from your own body). The patellar tendon is the strong tendon just below the kneecap (patella) that connects the kneecap to the shin bone. The graft is taken through an incision at the front of the knee, together with a small block of bone at each end: one from the lower part of the kneecap and one from the top of the shin bone. It was the graft used most often by experienced knee surgeons in the early 1990s, and it remains one of the main graft choices today (PMID 33486558). Laboratory studies show that it, like the other common grafts, is at least as strong and stiff as the natural ACL (PMID 35428007).
The rest of the operation is minimally invasive and is done with a knee arthroscopy (a camera inserted through small incisions). Tunnels are drilled in the thigh bone and the shin bone at the attachment points of the original ACL, and the graft is passed through them and fixed in place, so that it sits in the same position and orientation as the ligament it replaces. Because the graft has bone at both ends, it heals into the tunnels bone to bone, which is the fastest type of graft healing (PMID 39674612). It is one of the graft options for ACL reconstruction, alongside the hamstring autograft and the quadriceps tendon autograft, and in some knees it is combined with a lateral extra-articular tenodesis to add control of rotation.
A thorough clinical examination by a specialist and modern imaging helps confirm the diagnosis. Examination tests such as the Lachman test and the pivot shift test are accurate for detecting an ACL tear (PMID 26854045), and MRI shows the ligament and any injury to the meniscus and cartilage. Some meniscus tears are hard to see on MRI, so the arthroscopy at the start of the operation is also used to assess the joint and treat any other injuries found (PMID 31684739).
What are the benefits of a bone-patellar tendon-bone autograft ACL reconstruction?
A patellar tendon graft restores a stable knee. A Cochrane review of 19 randomised trials (1,597 adults) found that all tests of knee stability consistently showed a more stable knee after a patellar tendon graft than after a hamstring graft, with similar knee function and return to activity (PMID 21901700). A review of 12 randomised trials found results comparable to the other main grafts for graft failure, knee looseness and patient-reported knee scores (PMID 40679231).
It has a low risk of needing revision (repeat) surgery. In the Scandinavian knee ligament registries (45,998 operations), the risk of revision was 37% lower with a patellar tendon graft than with a hamstring graft, in men and women and at all ages, and the difference appeared slightly greater in people injured playing pivoting sports such as soccer (PMID 25201444). In the New Zealand ACL Registry, 1.3% of patellar tendon grafts needed revision, compared with 2.7% of hamstring grafts (PMID 31730379).
Most athletes return to sport, and the results last. Across 33 studies of 4,810 athletes, 83% returned to sport after a patellar tendon graft, and the re-rupture rate was 3.2% (PMID 39836368). In randomised trials that followed patients for 10 to 17 years, knee function, stability and graft survival were similar to those after a hamstring graft (PMID 40297041).
What are the risks of a bone-patellar tendon-bone autograft ACL reconstruction?
Pain at the front of the knee, especially when kneeling, is the main downside. In a review of 21 randomised trials (1,726 patients), problems at the graft site, such as pain at the front of the knee or difficulty kneeling, were more common after a patellar tendon graft than after a hamstring or quadriceps tendon graft (PMID 37000243). Reviews of randomised trials also found more pain at the front of the knee than with hamstring grafts in the longer term (PMID 32387652), and a small loss of full straightening (extension) of the knee (PMID 21901700).
Numbness of the skin near the incision is common. A small skin nerve (the infrapatellar branch of the saphenous nerve) crosses the front of the knee and is often affected by the incision. In one study, 77% of people reported an area of reduced feeling after a patellar tendon graft, compared with 58% after a hamstring graft; about a quarter of them recovered fully within a year, and most saw it as a minor problem (PMID 28404457). Fracture of the kneecap (in about 0.6% of people) and rupture of the patellar tendon (in about 0.2%) are rare but serious complications of taking the graft (PMID 37465207).
The new graft can fail or tear again, and the other knee remains at risk. In the New Zealand registry, people with a patellar tendon graft were more likely to need an ACL reconstruction on the other knee than those with a hamstring graft (PMID 31730379). Surgery does not guarantee a return to the previous level of sport: in the review of 4,810 athletes, 56% of those with a patellar tendon graft returned to their pre-injury level (PMID 39836368). Over the long term, knees that have had an ACL reconstruction are more likely to develop arthritis than the uninjured knee, whichever graft is used (PMID 40297041). Other risks are those of knee surgery in general, such as stiffness, infection, blood clots, ongoing pain or swelling, and injury to the cartilage or meniscus in the future.
Summary
A bone-patellar tendon-bone autograft ACL reconstruction replaces a torn ACL with the central part of your own patellar tendon, with a small block of bone at each end, placed through small tunnels in the thigh bone and shin bone to restore stability to the knee. It is usually recommended when the expected benefits for you outweigh the risks. You should discuss your symptoms, your scans and your goals, including plans for sport and work and how much kneeling you do, with your knee surgeon so that you can consider the graft options and the indications for surgery together.
General information only. The information on this page is general in nature and does not replace individual medical advice. All surgery carries risks, and results vary between patients. Please discuss your own circumstances with your treating practitioner.