

Total Hip Replacement – Brisbane & Hamilton
This page provides general information for patients of Dr Borshch, an orthopaedic surgeon consulting in Hamilton, Brisbane, who are being assessed for or considering total hip replacement surgery. If hip arthritis is limiting your walking, sleep or daily activities despite non-surgical treatment, an assessment with a hip surgeon in Brisbane can clarify whether replacement is the right next step.
Your individual condition and treatment plan may be different, so this information should be used alongside advice from your surgeon and treating team.
What is a Total Hip Replacement?
The damaged ball and socket of the hip are replaced with artificial joint surfaces.
The hip is a ball-and-socket joint. The ball (femoral head) sits at the top of the thigh bone and moves within a socket (acetabulum) in the pelvis.
Both surfaces are normally covered with smooth cartilage.
A total hip replacement, also called total hip arthroplasty (THA), replaces both damaged joint surfaces.
The replacement usually consists of:
- a metal socket fixed into the pelvis
- a durable plastic or ceramic liner
- a metal stem inserted into the femur
- a ceramic or metal ball attached to the stem
The aim is to create a stable, low-friction joint that reduces pain and allows more comfortable movement.
Why is Total Hip Replacement Surgery Done?
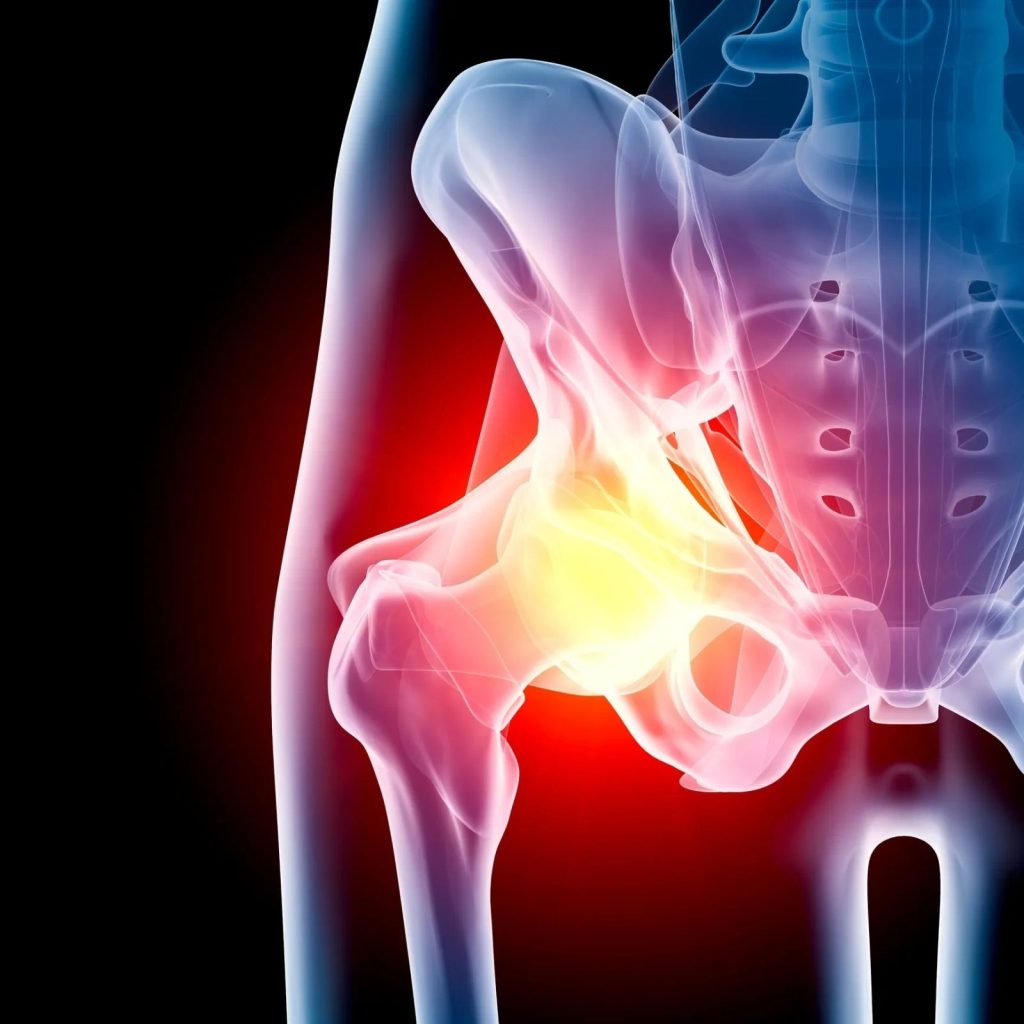
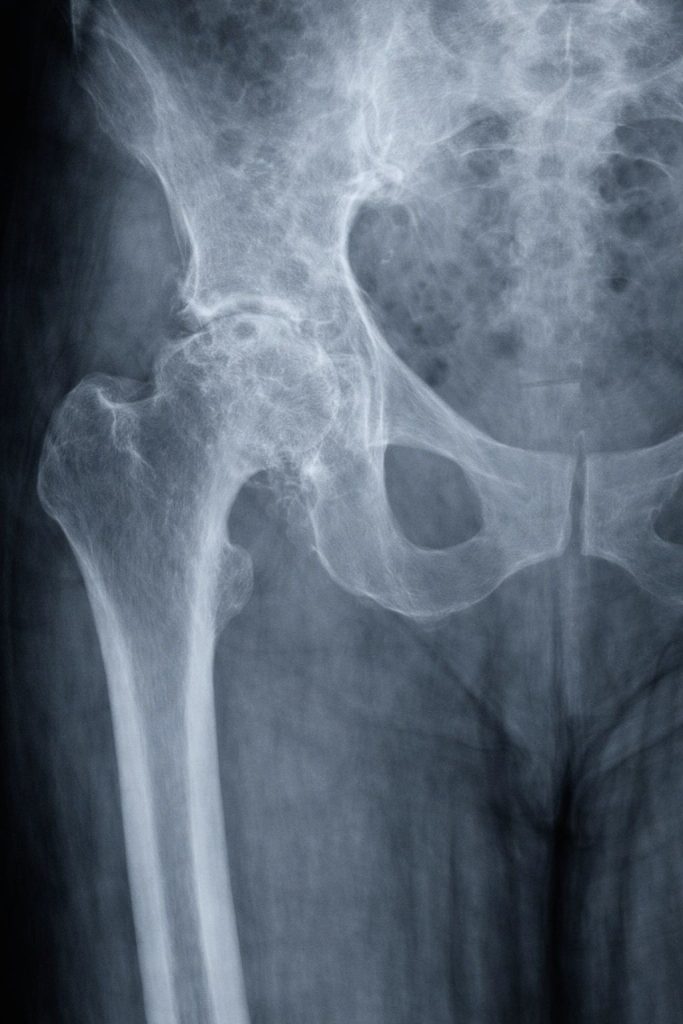
Surgery is considered when hip arthritis significantly affects quality of life.
The most common reason for hip replacement is osteoarthritis, where cartilage progressively wears away and the joint becomes painful and stiff.
Symptoms can include:
- groin, thigh or buttock pain
- difficulty walking
- pain at night
- difficulty putting on shoes and socks
- stiffness getting into cars or low chairs
- reduced ability to work, exercise or perform everyday activities
Not everyone with hip arthritis needs surgery.
Treatment can include exercise, activity modification, weight management where appropriate, medications, walking aids and sometimes injections.
Hip replacement is generally considered when symptoms are significant and appropriate non-operative treatment is no longer providing adequate relief. An evidence-based review of indications for total hip replacement similarly emphasised radiographic arthritis, substantial patient symptoms and failure of appropriate conservative treatment.
The decision should therefore be based on your symptoms and quality of life—not simply how an X-ray looks.
How is Total Hip Replacement Surgery Performed?
The arthritic surfaces are replaced while restoring hip stability and leg function.
Anaesthetic
A spinal or general anaesthetic may be used, together with additional pain relief around the hip.
Accessing the hip
There are several established approaches to hip replacement.
I use the Direct Anterior Approach (DAA) for most suitable primary hip replacements. This accesses the hip from the front through an interval between muscles, without routinely detaching the major muscles and tendons around the hip.
However, not every patient is suitable for DAA. Previous surgery, anatomy, deformity, body shape, bone loss and the complexity of the replacement may make another approach more appropriate.
A systematic review of randomised trials comparing anterior and posterior approaches found some advantages in early pain and functional recovery with DAA, but no significant difference in later functional outcomes.
The priority is therefore performing the hip replacement safely and accurately, rather than using a particular approach at all costs.
Replacing the socket
The damaged femoral head is removed and the arthritic socket is prepared.
A metal acetabular component is inserted into the pelvis, usually using a press-fit technique. A durable liner is placed inside it.
Replacing the femoral head
The femur is prepared and a metal stem is inserted.
A ceramic or metal ball is attached to the stem and placed into the new socket.
The hip is then checked for stability, movement, implant position and leg length.
What Materials Are Used in a Hip Replacement?

Modern implants combine durable materials designed for low wear and long-term fixation.
Modern hip replacements commonly use combinations of titanium or other metal alloys, ceramic or ceramicised metal and highly cross-linked polyethylene.
There is no single bearing material that is ideal for every patient.
A network meta-analysis of 64 randomised trials comparing hip bearing surfaces found good survivorship with modern highly cross-linked polyethylene and ceramic-containing bearings.
Implant selection considers factors such as:
- age
- bone quality
- anatomy
- activity
- implant fixation
- individual surgical requirements
Preparing for Hip Replacement Surgery

Improving your health and preparing your home can make early recovery easier.
Good preparation lowers risk and helps recovery.
Health optimisation (very important)
- Stop smoking/vaping if possible (smoking increases wound and infection risks).
- If you have diabetes, aim for good blood sugar control.
- Work on fitness and weight where possible—stronger muscles and better general health usually mean smoother recovery.
- Tell the team about any history of blood clots, sleep apnoea, heart/lung disease, or immune-suppressing medications.
Prehab (exercise before surgery)
Home preparation
- Arrange help for the first 1–2 weeks (meals, shopping, transport).
- Make your home safer: remove loose rugs, organise a stable chair, consider railings, and set up a bed/bathroom plan.
- Prepare icing options and comfortable walking paths.
Medications
Your team will advise what to stop or continue (for example, some blood thinners, anti-inflammatories, or supplements). Always check before changing anything.
Because Brisbane has a warm and humid climate, particularly during summer, consider having access to a cool, comfortable and preferably air-conditioned environment during recovery. A large meta-analysis found an association between warmer weather and surgical-site infection. This does not prove that air conditioning prevents infection, but keeping yourself comfortable and your dressing clean and dry is sensible during Brisbane's warmer months.
What Should I Expect After Hip Replacement?

Walking starts early, while strength and confidence continue improving for months.
In hospital (often 1–3 days, sometimes next-day discharge)
- Pain control using a multimodal plan (several types of pain relief together).
- Early walking and exercises with the help of an inpatient Physiotherapist. Learning the hip precautions that help keep the new joint from popping out.
- A blood clot prevention plan (medication and movement), guided by your risk factors.
First 2–6 weeks
- You will have your first review back in the office (usually with the nurse), this is mainly to check that the incision is healing well, make sure your pain is controlled and address any other concerns.
- Your walking improves steadily, usually with a walker/crutches early, then a stick, then independently.
- Swelling and bruising is common.
- You’ll do regular exercises to regain movement and strength with the help of an outpatient Physiotherapist. The main aim is to restore a normal gait.
- Driving is usually not safe until 6 weeks post surgery or when leg strength is close to normal.
6 weeks to 3 months
- You will have your first review in the office with me, this is mainly to check your gait and resolution of symptoms.
- Most people notice major improvements in daily activities.
- Strength and endurance continue to build.
- Some swelling can still be normal.
3 to 12 months
- Ongoing improvement in strength, balance, confidence and cosmetic appearance of the incision.
- Some people continue to notice gains up to a year (or longer).
Hip precautions
- During surgery the ball and socket are placed separately and then put together towards the end of the operation. This means that they can separate again (dislocate) in the short term while the scar tissue is forming and sometimes long term if the joint is placed into a “dangerous” position.
- For a Direct Anterior Approach hip replacement, the “dangerous” positon to avoid is usually one where the leg is turned outward, knees apart and leg towards the back.
- For a Posterior Approach hip replacement the “dangerous” position to avoid is usually one where the leg is turned inward, knee too close to the chest and knee crossed over the other leg.
- Hip precautions are ideally practiced for the first 3 months after surgery, but any “extremes” of range of motion or positions of the hip should be avoided life-long.
Will My Legs Feel the Same Length?

Temporary feelings of leg-length difference can occur while the body adjusts.
One common concern after hip replacement is that the operated leg feels longer.
The surgeon aims to restore appropriate leg length while also achieving a stable hip.
Interestingly, a perceived difference does not always mean the bones are actually different lengths. Pelvic position, muscle tightness and the way you walked before surgery can affect this sensation.
A study following perceived leg-length difference after hip replacement found that this sensation reduced substantially during the first three months after surgery.
Persistent or substantial concerns should nevertheless be assessed.
Long-Term Outcomes After Total Hip Replacement
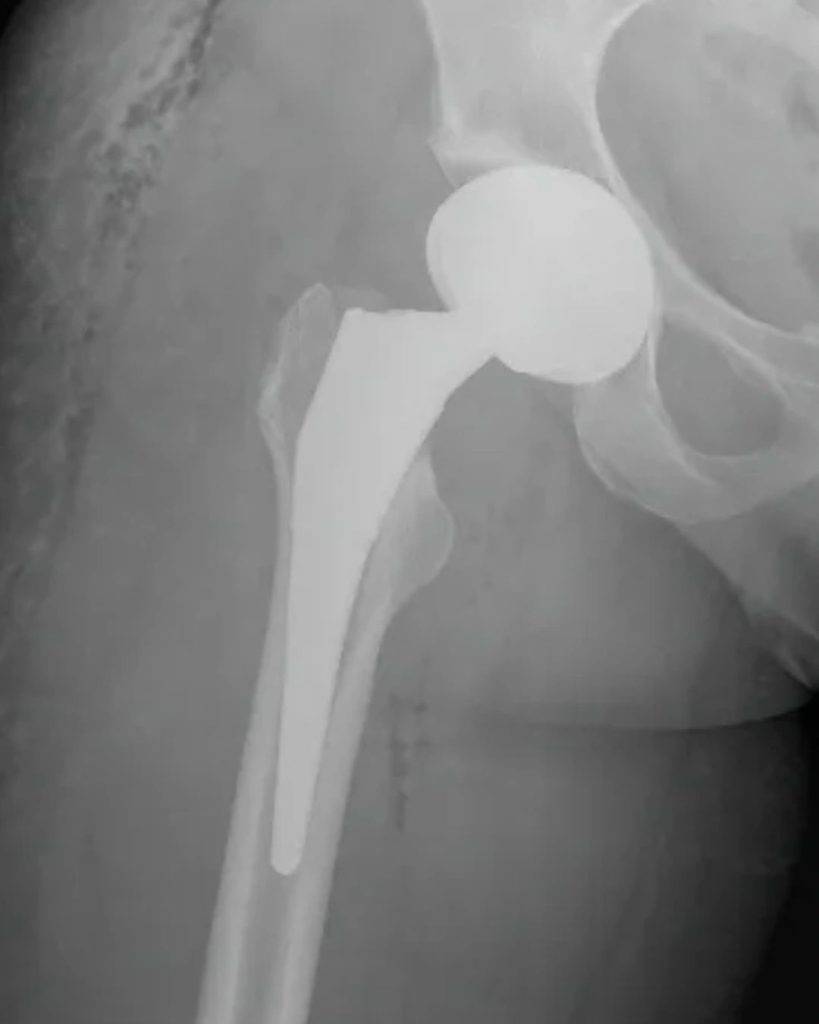
Most patients gain substantial pain relief, and modern implants can last for decades.
Hip replacement generally produces large improvements in pain, function and quality of life. A systematic review and meta-analysis of quality of life after total hip replacement found substantial and sustained improvements following surgery.
How long does a hip replacement last?
A major systematic review published inThe Lancet analysed long-term case series and national joint replacement registries.
Registry data estimated approximately:
- 89% survival at 15 years
- 70% survival at 20 years
- 58% survival at 25 years
These are population estimates rather than an expiry date for an individual hip replacement.
Can I return to sport?
Most patients can return to recreational activity.
A 2023 systematic review and meta-analysis reported an overall return-to-sport rate of approximately 85%, with particularly high return rates for lower-intensity activities.
Walking, cycling, swimming and similar lower-impact activities are generally easier to return to than repetitive high-impact sport.
Things to Look Out for After Hip Replacement

Increasing pain, wound problems or sudden changes in function should be assessed.
Contact our office, your GP, or go to hospital urgently if you notice:
Possible infection
- increasing redness, warmth, or swelling around the wound
- worsening pain after initial improvement
- pus or bad-smelling discharge
- fevers or feeling very unwell
(Periprosthetic joint infection after primary hip replacement is uncommon—around 1–2%—but very serious.) (Study of infection rates after joint replacement)
Blood clot warning signs
- new calf pain or tenderness, increasing swelling in one leg
- sudden shortness of breath, chest pain, coughing blood (call emergency services)
Dislocation symptoms (uncommon)
- sudden severe hip pain
- inability to move the leg normally
- leg appearing shortened or rotated
This requires urgent assessment.
Wound problems
- leaking through dressings
- opening wound edges
- rapidly increasing bruising or swelling
Nerve or circulation concerns (rare)
- worsening numbness or weakness in the leg or foot
- cold or pale foot
- severe escalating pain
Total Hip Replacement
Dr Alexey Borshch is a specialist orthopaedic surgeon in Brisbane with a particular clinical focus on surgery of the hip, knee and lower limb.
His practice as a Brisbane orthopedic surgeon focuses on the assessment and treatment of hip arthritis, along with performing hip replacement and revision hip replacement surgery.
Dr. Borshch completed his medical degree at the University of Queensland before undertaking specialist orthopaedic training in Queensland. He completed the Australian Orthopaedic Association training program and the Royal Australasian College of Surgeons Fellowship Examination in Orthopaedic Surgery. He obtained specialist registration in Orthopaedic Surgery in 2022 and is a Fellow of the Australian Orthopaedic Association.
Dr. Borshch offers consultations in Hamilton, Brisbane, and performs private orthopaedic surgery at Brisbane Private Hospital.