
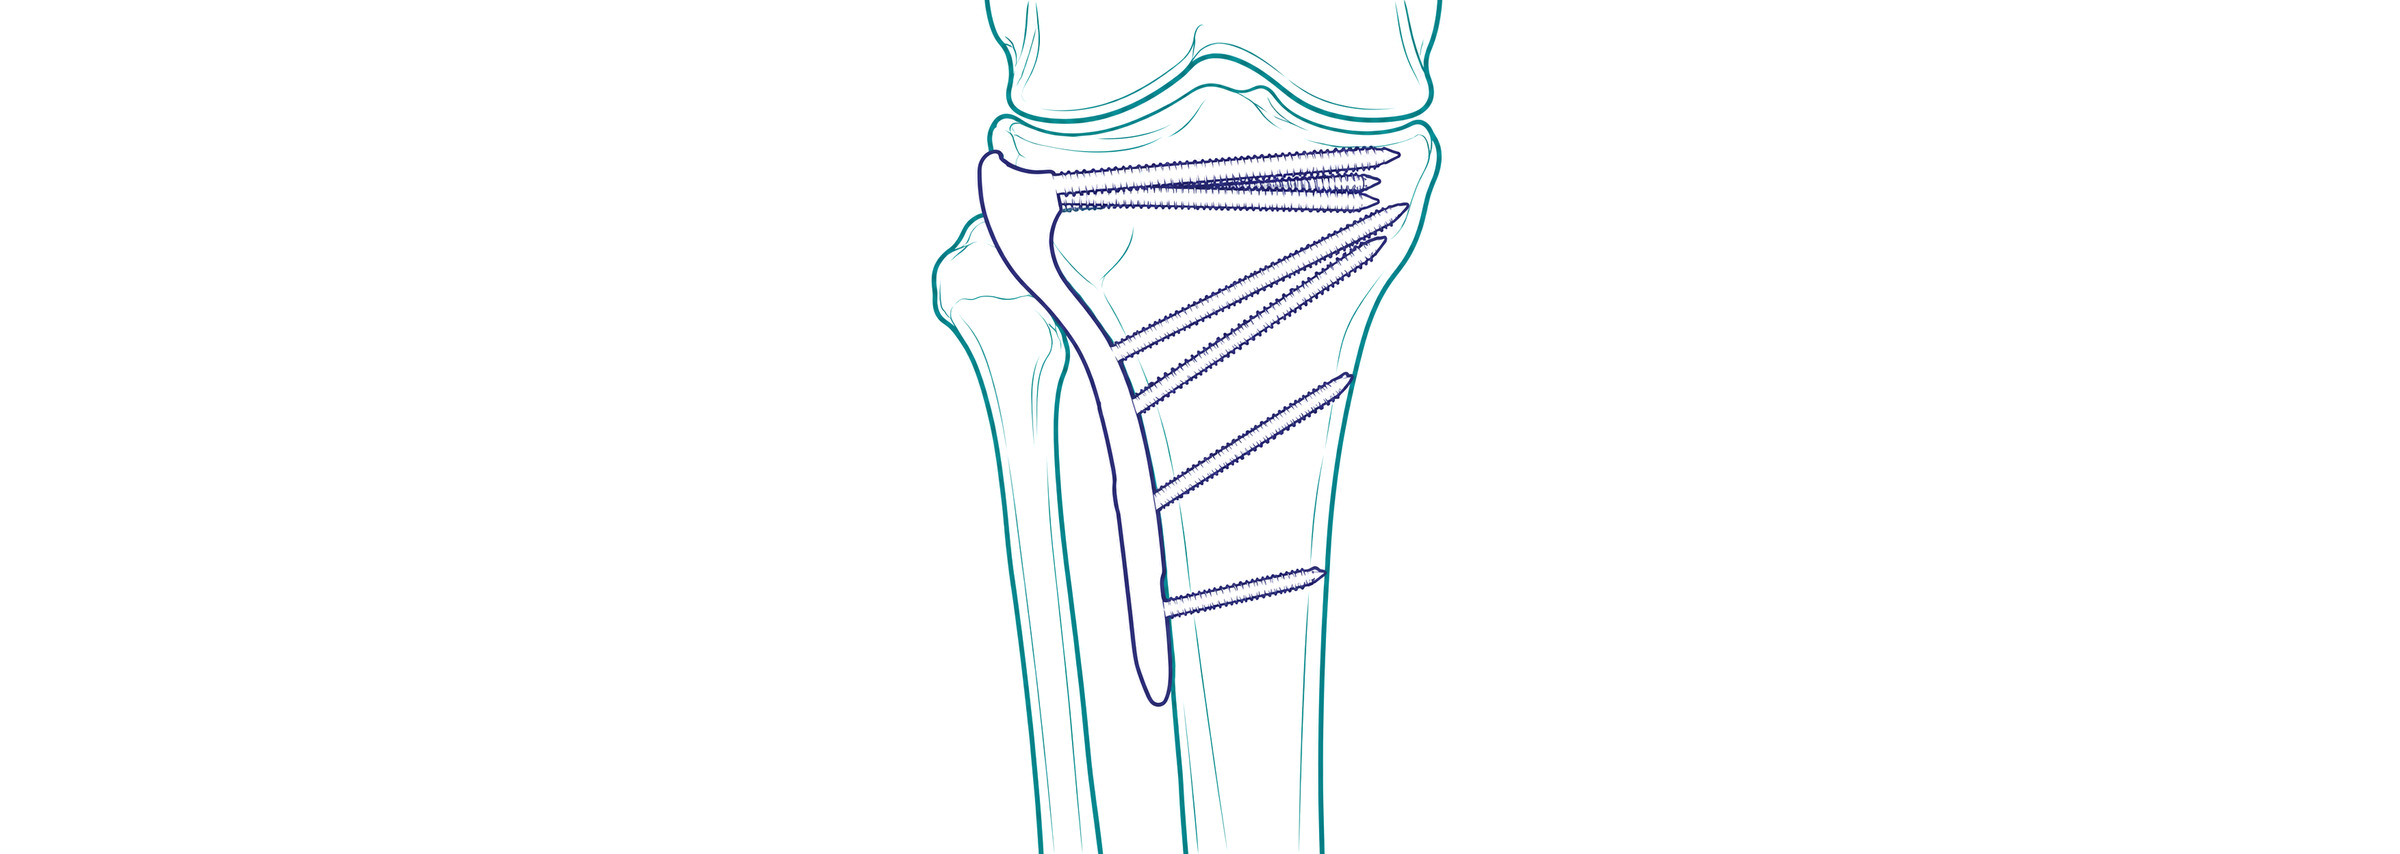
What is tibial plateau fracture surgery?
The tibial plateau is the flat top of the shin bone (tibia), which forms the lower half of the knee joint. A tibial plateau fracture is a break in this part of the bone, and it usually extends into the knee joint. In a large population study, these fractures occurred in about 10 in every 100,000 people each year, most often between the ages of 40 and 60 (PMID 26375535). They can follow a lower-energy injury, such as a fall, or a high-energy injury, such as a road accident, and the soft tissues around the knee are often injured as well (PMID 28461952).
Surgery aims to restore the smooth joint surface and the alignment of the leg, and to hold the bone fragments firmly enough to allow early knee movement (PMID 28461952). The most common operation is open reduction and internal fixation: the surgeon makes one or more incisions, puts the bone fragments back in position and holds them with a plate and screws (PMID 28461952). Where part of the joint surface has been pushed down (depressed), it is lifted back up, and the gap left underneath may be filled with bone graft or a bone substitute (PMID 39171616).
Some fractures that involve only part of the joint can be treated with minimally invasive methods, such as screws placed through small incisions. A knee arthroscopy (keyhole camera) can be used at the same time to check that the joint surface has been restored and to treat injuries to the meniscus or ligaments (PMID 28461952; PMID 39603523). For high-energy fractures with severe swelling, treatment is often staged: a temporary frame on the outside of the leg (external fixator) is placed across the knee to stabilise the bones while the soft tissues settle, and the definitive fixation is done later (PMID 16056075; PMID 39603523).
A thorough clinical examination by a specialist and modern imaging help confirm the diagnosis and plan treatment. A CT scan, and sometimes an MRI scan, shows the fracture pattern more accurately than plain X-rays, and surgical plans are often changed after these scans (PMID 19325067). Not every tibial plateau fracture needs an operation; the decision depends on the fracture pattern, the condition of the skin and soft tissues, and the person's health and activities.
What are the benefits of tibial plateau fracture surgery?
Surgery puts the joint surface back together. People whose joint surface healed with only a small step had better knee movement, less pain and better knee function than those whose joint surface healed with a larger step (PMID 27984441). Accurate reduction of the joint surface and alignment of the leg also lowers the chance of later arthritis and of needing a knee replacement (PMID 39454244; PMID 17211262).
Long-term results are often good. In a study of 202 people who had surgery, 95% of fractures had healed without problems at one year; in the 109 people followed for an average of 14 years, knee movement was well preserved and function scores were good, regardless of age (PMID 17211262).
Many people return to sport. In a review of 27 studies, about 7 in 10 people returned to sport after surgery, and about 8 in 10 after arthroscopically assisted fixation (PMID 28808629). For suitable fractures of the outer (lateral) side of the plateau, arthroscopically assisted fixation has been associated with better knee movement, less blood loss and a shorter hospital stay than traditional open surgery, with good or excellent results in more than 90% of patients in the studies that reported them (PMID 35867167).
What are the risks of tibial plateau fracture surgery?
Tibial plateau fractures are difficult injuries with a high rate of complications, including early arthritis, and there is not enough evidence to say which method of fixation is best (PMID 39171616). Arthritis can develop even after successful surgery: in a long-term study, 31% of people developed arthritis in the knee, although most tolerated it well, and it was more common when the leg had healed out of alignment (PMID 17211262). In a population study of more than 8,400 people, 7.3% had a total knee replacement within 10 years of surgery, about five times the rate in the general population; the risk was higher in older people and in fractures involving both sides of the plateau (PMID 24430414). In another study, a remaining step in the joint surface, widening of the top of the shin bone and age over 50 were linked with needing a knee replacement (PMID 39454244).
Infection is one of the most important risks. In a review of eight studies (2,214 people), about 1 in 10 developed an infection where the surgery was done; the risk was higher with open fractures (where the skin is broken), compartment syndrome, longer operations, smoking and use of an external fixator (PMID 28385655). Infection can have lasting effects: in one study, people who developed an infection had worse knee function and were less likely to return to work (39% compared with 81%) (PMID 39666150).
The injury can cause a dangerous rise in pressure in the muscles of the lower leg (compartment syndrome), which needs urgent surgery to release the pressure (fasciotomy); in one large series this happened in about 2 in every 100 tibial plateau fractures (PMID 39251201). Fractures of the inner (medial) side of the plateau, which can occur with a dislocation of the knee, are more likely to injure the nerve on the outer side of the knee (peroneal nerve) or the main blood vessels behind the knee (PMID 19325067).
Other possible problems include knee stiffness, the bone healing slowly or not healing (non-union), and the need for further surgery. In a series of complex high-energy fractures, 16% of people needed further surgery related to their injury (PMID 16056075). Not everyone returns to their previous sport: in the review of 27 studies, about 3 in 10 people did not (PMID 28808629). Plates and screws can sometimes irritate and need to be removed once the bone has healed. There are also risks of blood clots, wound problems, numbness around the incision and risks from the anaesthetic, which your anaesthetist will discuss with you.
Summary
Tibial plateau fracture surgery aims to restore the joint surface and alignment of the knee, and to hold the bone steady while it heals so that the knee can start moving early. Depending on the fracture, this may involve a plate and screws, screws placed through small incisions with the help of arthroscopy, or a staged approach with a temporary external frame. Surgery is usually recommended when the fracture is displaced or unstable and the expected benefits for you outweigh the risks. You should discuss your injury, your scans and your goals, including work and sport, with your fracture surgeon or knee surgeon so that you can consider the options and the indications for treatment together.
General information only. The information on this page is general in nature and does not replace individual medical advice. All surgery carries risks, and results vary between patients. Please discuss your own circumstances with your treating practitioner.