
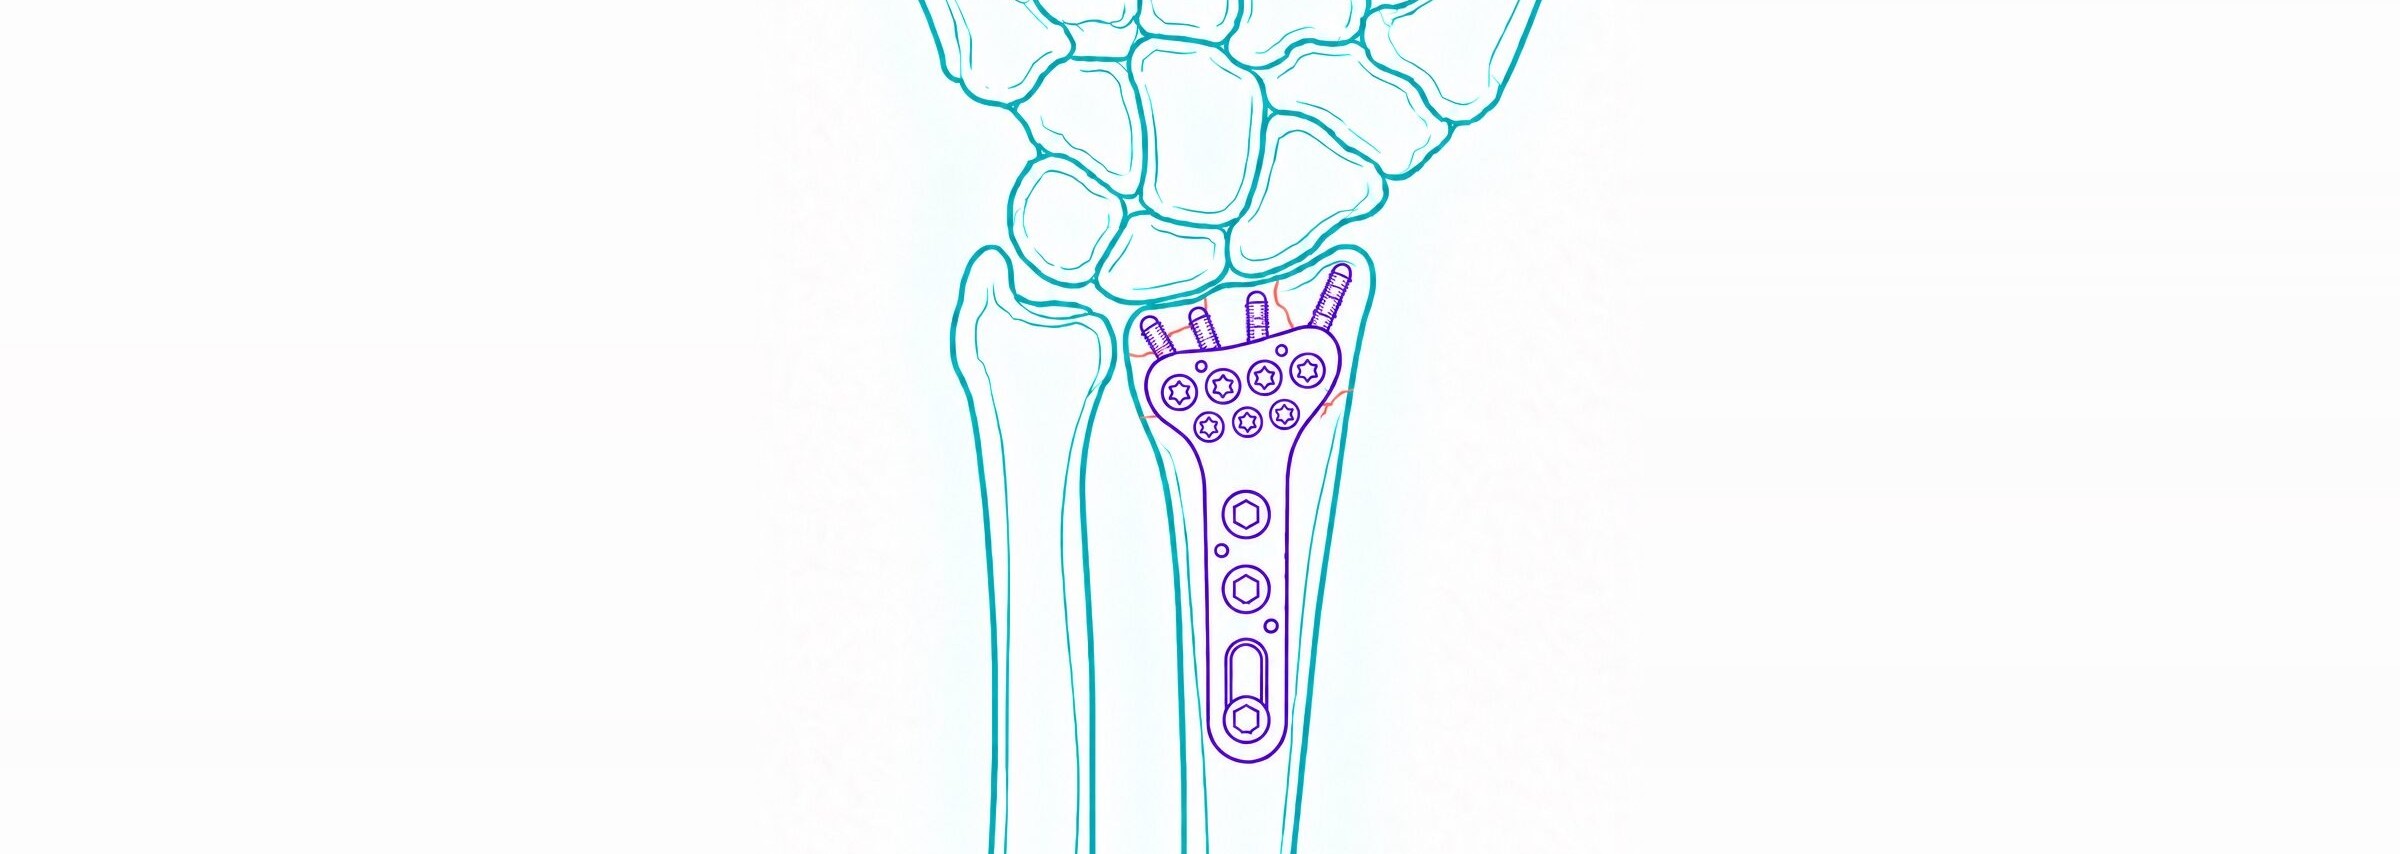
What is distal radius fracture surgery?
The radius is the larger of the two bones of the forearm, on the thumb side. A distal radius fracture is a break at its lower end, just above the wrist joint. It is one of the most commonly treated fractures, and in older people it is second only to hip fractures (PMID 29499822). In a Danish population study of 5,426 adult fractures of the lower forearm, 77% occurred in women, the rate rose markedly in women after the age of 50, the most common type did not involve the joint surface (69%), and 76% were caused by a fall from standing height (PMID 35856325).
Many wrist fractures can be treated without an operation, by moving the bone back into position without an incision if needed (closed reduction) and holding it in a cast or splint. Surgery is mainly considered for fractures in which the bone ends have moved (displaced) and are unlikely to stay in a good position in a cast (unstable) (PMID 22159849; PMID 34137830).
The most common operation is open reduction and internal fixation with a volar locking plate: through an incision on the palm side (volar side) of the wrist, the bone pieces are put back in position and held with a plate and screws that lock into the plate (PMID 25096595). Other options include thin wires passed through the skin into the bone (Kirschner wires or K-wires) and an external fixator, which is a frame outside the wrist attached to the bone with pins (PMID 25096595; PMID 34137830).
A thorough clinical examination by a specialist and modern imaging help confirm the diagnosis. X-rays show where the fracture is, how far the bone has moved and whether the joint surface is involved, and a CT scan may be used for more complex fractures.
What are the benefits of distal radius fracture surgery?
Surgery restores the shape and alignment of the end of the radius and holds the bone steady while it heals. In a meta-analysis of 23 studies including 2,254 adults, surgery improved arm function scores in the first year and improved grip strength compared with non-surgical treatment, with the greatest improvement in function in studies that included younger adults (PMID 32324239).
In a randomised trial of 73 people aged 65 and over, volar plate fixation gave better wrist function in the early period after surgery, better grip strength at every time point and better alignment of the bone (PMID 22159849). In the WRIST trial of adults aged 60 and over, the bone healed in a poor position (malunion) in 8.0% of people after volar plating, compared with 59.1% after casting (PMID 34137830).
Surgery also stops the fracture from slipping out of position while it heals. In the DRAFFT2 trial of 500 adults, 13% of people treated in a cast needed an operation in the first six weeks because the fracture moved, compared with one person after K-wire fixation (PMID 35045969).
What are the risks of distal radius fracture surgery?
Surgery mainly improves the position of the bone and early recovery; it may not improve long-term wrist function, especially in older people. In the meta-analysis, surgery did not improve arm function scores in studies of people aged 60 or over (PMID 32324239). In the WRIST trial, hand and wrist function and pain at 24 months did not differ meaningfully between volar plating, external fixation, K-wires and casting (PMID 34137830), and in DRAFFT2, K-wire fixation did not improve wrist function at 12 months compared with a cast (PMID 35045969). In the trial of people aged 65 and over, function at six and twelve months was similar with or without surgery, and complications were more common after surgery (13 compared with 5) (PMID 22159849).

In a systematic review of 35 randomised trials including 1,419 people treated with a volar plate, complications occurred in 30.8%, and 12.4% were major complications. The most common were problems with the median nerve, the main nerve to the hand (7.1%), and removal of the plate (6.8%). Others included irritation of the tendons (tenosynovitis, 3.4%), complex regional pain syndrome, a painful condition with swelling and stiffness (2.4%), superficial wound infection (1.9%), tendon rupture (1.3%) and the bone healing in a poor position (1.3%) (PMID 37552141). In the WRIST trial, 18.5% of people who had a plate reported compression of the median nerve (carpal tunnel symptoms), and pin site infection was the most common problem after K-wires, affecting 23.2% (PMID 30657531).
Some people need a further operation to remove the plate. In a review of 52 studies, an average of 9% of plates were removed, most often as a routine, for tendon irritation, because of a problem with the implant or at the patient's request (PMID 29031822). Other possible problems include stiffness, a visible scar and the risks of the anaesthetic, which your anaesthetist will discuss with you.
Summary
Distal radius fracture surgery aims to restore the shape and alignment of the end of the radius and hold the bone steady while it heals. Depending on the fracture, this may involve a plate and screws, wires or an external fixator. Many wrist fractures heal well in a cast, and surgery is usually recommended when the expected benefits for you outweigh the risks. You should discuss your injury, your X-rays and your goals, including your work, sport and other activities, with your fracture surgeon so that you can consider the options and the indications for treatment together.
General information only. The information on this page is general in nature and does not replace individual medical advice. All surgery carries risks, and results vary between patients. Please discuss your own circumstances with your treating practitioner.