
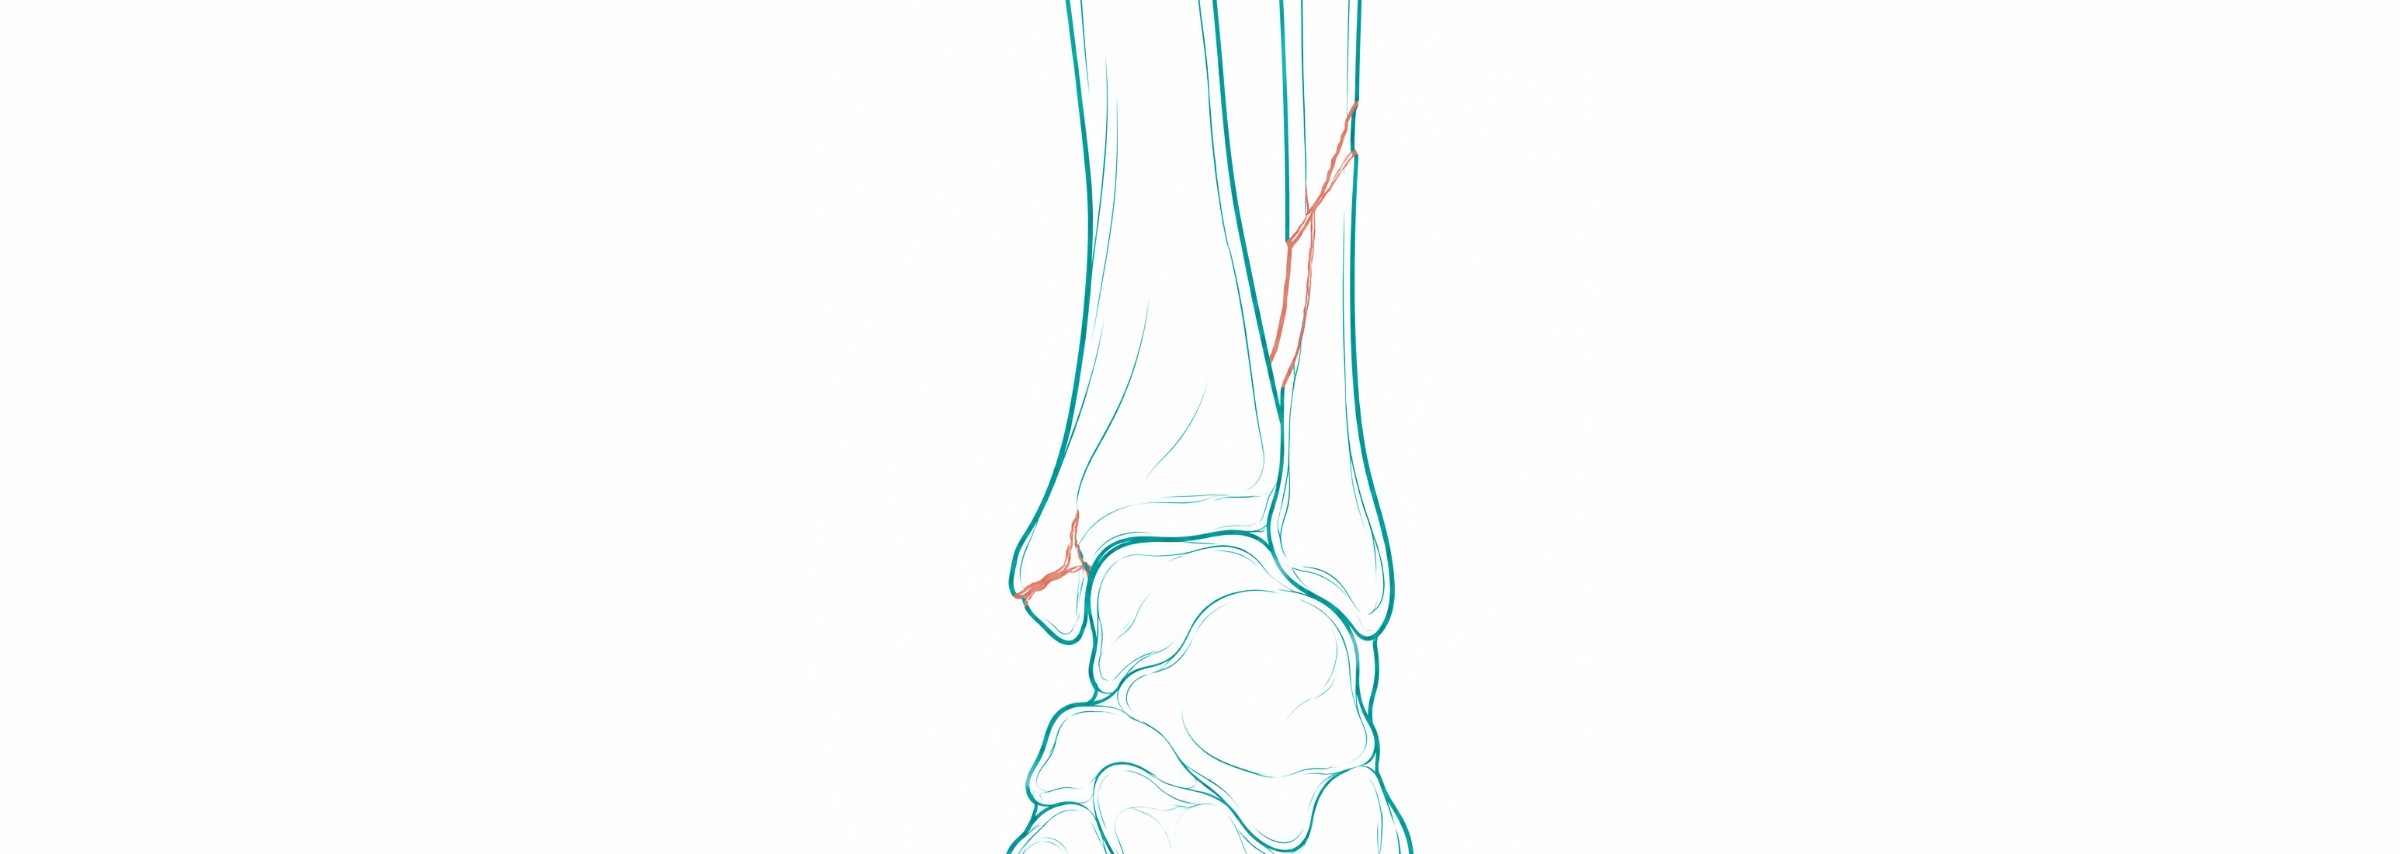
What are ankle fracture fixation options?
When an unstable ankle fracture needs an operation, the broken bones are put back into position and held with implants while they heal. The general steps, recovery and risks of the operation are described on the ankle fracture surgery page. This page explains the different ways each part of the ankle can be fixed. The choice depends on which bones are broken, the fracture pattern, the bone quality, the condition of the skin and your general health.
A thorough clinical examination by a specialist and modern imaging help confirm the diagnosis and plan the fixation. X-rays, and often a CT scan, show which bones are broken, how far the pieces have moved and the size of any fragment at the back of the shin bone.
The fibula (the outer ankle bone) is most often fixed with a plate and screws through an incision over the bone. Locking plates, in which the screws lock into the plate, may be chosen for weaker (osteoporotic) bone or fractures in several pieces (PMID 29681437). A minimally invasive alternative is a fibular nail: a rod placed inside the fibula through a small incision at the tip of the outer ankle and locked with screws. It is mainly used when the skin and soft tissues are at risk or the person has other medical conditions (PMID 30583773; PMID 41583220).
The medial malleolus (the inner ankle bone) is usually fixed with screws or with tension band wiring (fine wires with a figure-of-eight wire loop), chosen according to the fracture type, the size of the fragment and the bone quality (PMID 36270443). Screws can often be placed through small incisions. The posterior malleolus (the back of the lower shin bone) is fixed when the fragment is large or displaced, either with screws placed from the front of the ankle through small incisions, or through an incision at the back of the ankle with a buttress plate or screws (PMID 38824055; PMID 38278653). If the ligaments between the tibia and fibula (the syndesmosis) are unstable, they are also stabilised, as explained on the ankle fracture surgery page.
What are the benefits of ankle fracture fixation options?
Having more than one option means the fixation can be matched to the fracture, the bone and the skin. Fixing the back of the shin bone directly can restore the joint surface accurately. In a review of 6 studies with 386 patients, fixation with a plate through an incision at the back of the ankle was more likely to achieve an excellent anatomical reduction (the pieces put back in their normal position) and gave better foot and ankle function scores than screws placed from the front (PMID 38824055). In a review of 53 studies with 3,757 patients, plate fixation of the posterior malleolus was linked with better function, faster bone healing, earlier full weight-bearing, less pain and lower rates of malunion and arthritis than screw fixation (PMID 38278653).
Fixing the posterior malleolus can also stabilise the ligaments between the tibia and fibula. In a study of 85 unstable ankle fractures, only 4.7% of ankles with a fixed posterior malleolus needed separate syndesmosis fixation, compared with 81.0% when this fragment was not fixed (PMID 34552413).

A fibular nail needs only small incisions, which lowers the risk of wound problems. In a review of 26 studies with 1,710 patients, fibular nailing had significantly fewer wound complications, implant removals and nonunions (bones that did not heal) than plate fixation (PMID 30583773). In a randomised trial of 100 people over 65 with unstable ankle fractures, there were significantly fewer wound infections with a fibular nail, function at one year was similar, and overall treatment cost less than with a plate (PMID 27587528). A review of randomised trials estimated that 14% fewer patients would have a complication with a fibular nail (PMID 35339374), and a 2025 review also found shorter operations and fewer problems caused by the implants (PMID 41583220).
Both common methods of fixing the inner ankle bone give reliable results. In a review of 10 studies with 512 medial malleolus fractures, screws and tension band wiring achieved bone healing and function equally well, with similar rates of infection and fixation failure (PMID 36270443).
What are the risks of ankle fracture fixation options?
Every fixation method carries risks. Plates are placed through a longer incision over the bone, so wound healing problems and infection can occur; in one study of 145 patients with plate fixation of the fibula, 2.8% needed a further operation to wash out an infection, with no difference in complications between locking and conventional plates (PMID 29681437). Plate fixation of the posterior malleolus takes longer and causes more blood loss than screws (PMID 38278653). Whether the back of the shin bone is fixed from the front or the back, problems such as arthritis, nerve pain, wound healing problems and implant failure can occur at similar rates (PMID 38824055).
Implants sometimes need to be removed in a later operation. In a study of 997 patients, 17% had their implants removed after ankle fracture fixation, most often because of discomfort, and 2.6% because of infection (PMID 27262772). In a Finnish national study of 68,865 patients, 27% had a later operation to remove implants (PMID 32106732).
A fibular nail is not suitable for every fracture. In a randomised trial of 71 patients, nailing was technically impossible in 19.4% of those allocated to it and plate fixation was used instead, and the technique was recommended for fractures that are not in many pieces and have no syndesmosis injury (PMID 24709304). In a study of 55 older patients with other medical conditions, the fibula healed out of its normal alignment on X-rays more often after nailing (46% compared with 13%), and loosening of the lower locking screws was more common (80% compared with 11%), although mostly without symptoms (PMID 41729233). In a study of 48 ankle fractures fixed with a fibular nail, 23% had a complication and 21% needed the implant removed because of symptoms (PMID 33717942). Function up to 12 months is likely to be similar to plate fixation rather than better (PMID 35339374), and the studies comparing the two methods are small with short follow-up (PMID 41583220).
Other possible problems after any ankle fracture fixation include irritation of the small nerves around the ankle causing numbness, stiffness, ongoing swelling, blood clots, arthritis of the ankle, a visible scar and the risks of the anaesthetic, which your anaesthetist will discuss with you.
Summary
Ankle fracture fixation options include plates and screws or a minimally invasive nail for the fibula, screws or tension band wiring for the inner ankle bone, and screws or a plate for the back of the shin bone. Each option has benefits and risks, and the choice depends on the fracture pattern, the bone quality, the condition of the skin and your general health. Fixation is usually recommended when the expected benefits for you outweigh the risks. You should discuss your injury, your scans, your general health and your goals, including your work, sport and other activities, with your fracture surgeon so that you can consider the options and the indications for treatment together.
General information only. The information on this page is general in nature and does not replace individual medical advice. All surgery carries risks, and results vary between patients. Please discuss your own circumstances with your treating practitioner.