
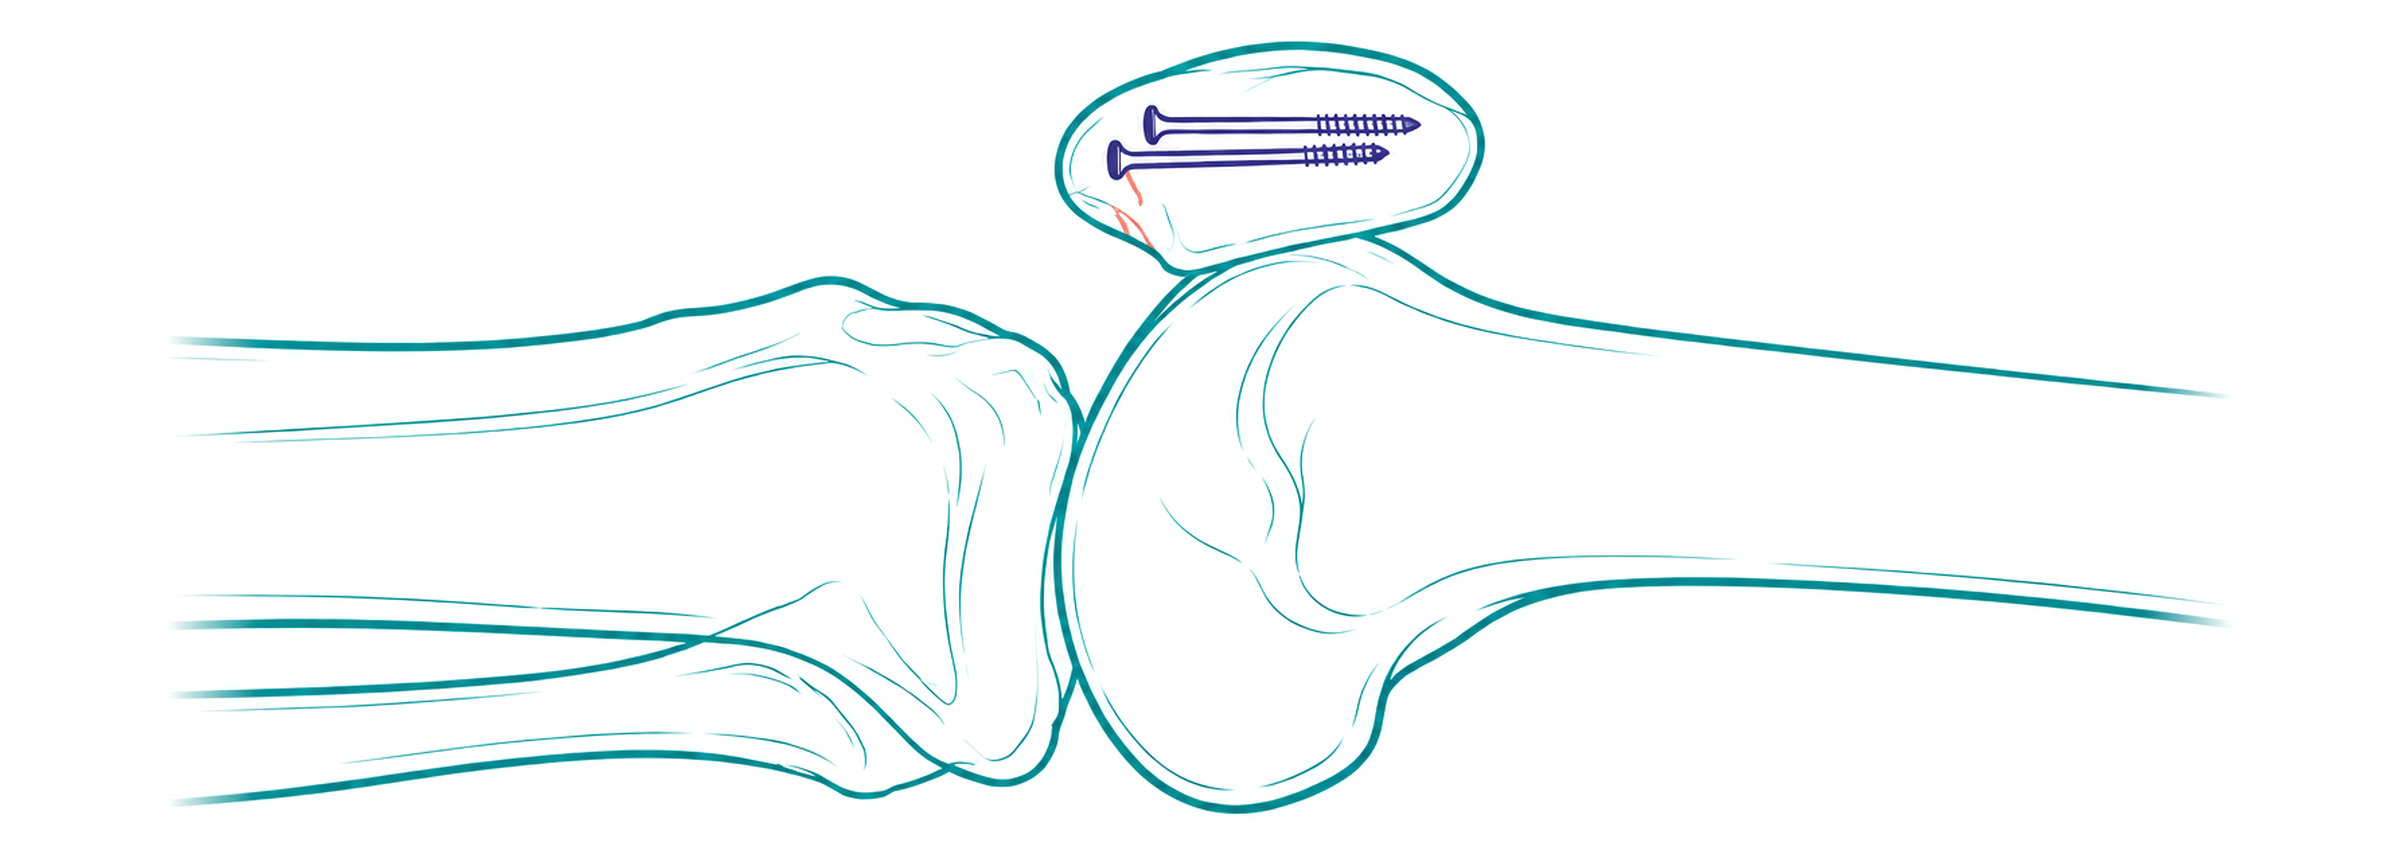
What is patella fracture surgery?
The patella (kneecap) is a small bone at the front of the knee that sits within the tendon of the quadriceps (front thigh) muscles. It acts as a lever that makes these muscles more efficient at straightening the knee, and it glides in a groove at the lower end of the thigh bone (PMID 21464213; PMID 31940427). A patella fracture is a break in this bone, caused either by a direct blow, such as a fall onto the knee, or by excessive pull through the quadriceps and its tendons (PMID 21464213). Patella fractures account for around 1% of all fractures (PMID 33625743). In a population study they occurred in about 13 in every 100,000 people each year, and they were most common in women aged 60 to 80 (PMID 27536953). In people aged 60 and over, they more often follow a low-energy injury, such as a fall from standing height, and are increasingly regarded as fragility fractures (PMID 31627900).
Not every patella fracture needs surgery. A fracture in which the pieces have not moved apart and the person can still actively straighten the knee (an intact extensor mechanism) can usually be treated without an operation. Surgery is recommended when the fracture stops the knee from straightening, or when the pieces have separated or left a step in the joint surface (PMID 21464213; PMID 31940427). Surgery aims to bring the pieces back together, restore a smooth joint surface and hold the bone firmly enough to allow early knee movement.
Several methods are used, depending on the fracture. A long-established method is the tension-band technique, in which wires or hollow (cannulated) screws are placed across the fracture and combined with a wire or strong suture over the front of the kneecap (PMID 21464213; PMID 34570740). Small, low-profile plates and screws are increasingly used, including for fractures with several pieces and for fractures of the lower tip (pole) of the kneecap (PMID 34664117; PMID 31627900). For suitable fractures, the bone can be fixed in a minimally invasive way, through small incisions with screws, wires or sutures passed through the skin (percutaneous fixation) (PMID 34404423; PMID 37198050).
A thorough clinical examination by a specialist and modern imaging help confirm the diagnosis and plan treatment. A CT scan often shows fracture lines that are hard to see on plain X-rays: in one study, adding a CT scan changed the surgeons’ treatment plan in 49% of cases (PMID 22955333; PMID 34570740).
What are the benefits of patella fracture surgery?
Surgery restores the extensor mechanism (the quadriceps muscle, kneecap and patellar tendon that work together to straighten the knee) and allows the bone to heal in the correct position. Bone healing rates after surgery are high: in large reviews, the bone healed in more than 98% of people (PMID 38980395; PMID 22902732). Accurately restoring the joint surface is the most important way of reducing the risk of arthritis behind the kneecap later in life (PMID 31940427).
Newer fixation methods have improved results. In a 2026 randomised trial of 122 adults with a displaced patella fracture, fixation with a locking plate gave better patient-reported symptoms, sport and recreation function, and quality of life at 12 months than traditional tension-band wiring (PMID 42674573). Reviews have found good knee movement and function with low pain levels after plate fixation (PMID 37286819; PMID 34664117), and better function and fewer complications when cannulated screws are used, with or without a tension band, compared with tension-band wiring with wires alone (PMID 40601089).
For suitable fractures, minimally invasive fixation offers a faster early recovery. In a review of six studies (304 patients), it was associated with less pain in the first three months, better knee bending and function at two years, fewer complications and less need for implant removal than open surgery (PMID 34404423). In another study of transverse (straight across) fractures, knee bending and straightening recovered faster after minimally invasive fixation than after open surgery (PMID 37198050).

What are the risks of patella fracture surgery?
A patella fracture is a significant injury, and some weakness and discomfort often remain even after successful surgery. In one study all the fractures healed, but at 12 months the muscles that straighten the knee were 41% weaker on the injured side than on the other side, and 80% of people had pain at the front of the knee during daily activities (PMID 23864187). In another study of 113 surgically treated fractures, knee-related quality of life was often reduced, particularly after more complex fractures (PMID 28965219).
Because the kneecap lies just under the skin, the most common problem is irritation from the implants. In a review of 5,659 patients, 29.6% had an operation to remove painful implants; the fixation failed in 5.2%, infection occurred in 3.1%, and the bone failed to heal in 1.7% (PMID 38980395). Having the implants removed improved pain and quality of life, but did not reliably improve knee function scores (PMID 29185046).
Each method has its own limitations. Tension-band wiring was associated with more implant removal, fixation failure and reoperation than locking plates (PMID 42674573). Minimally invasive fixation is mainly used for simpler fracture patterns and, in one study of transverse fractures, took longer to perform than open surgery (PMID 37198050). The quality of the trials comparing different methods is low, so it remains uncertain which method is best for each type of fracture (PMID 33625743).
Older people have a higher risk of complications. In people aged 65 and over, complications were more frequent than in younger patients despite similar fractures and treatment, straightening of the knee was more limited at six months, and 11% needed a further operation (PMID 40228553; PMID 31627900). Patella fractures can also lead to knee stiffness, weakness when straightening the knee and arthritis behind the kneecap (PMID 21464213; PMID 31940427). Other possible problems include wound problems, blood clots and numbness around the incision. There are also risks from the anaesthetic, which your anaesthetist will discuss with you.
Summary
Patella fracture surgery aims to restore the knee’s ability to straighten, recreate a smooth joint surface and hold the bone steady while it heals, so that you can start moving the knee early. Depending on the fracture, this may involve wires, screws, strong sutures or a small plate, and for suitable fractures it may be done through small incisions. Surgery is usually recommended when the expected benefits for you outweigh the risks. You should discuss your injury, your scans and your goals, including your work, sport and other activities, with your fracture surgeon or knee surgeon so that you can consider the options and the indications for treatment together.
General information only. The information on this page is general in nature and does not replace individual medical advice. All surgery carries risks, and results vary between patients. Please discuss your own circumstances with your treating practitioner.