
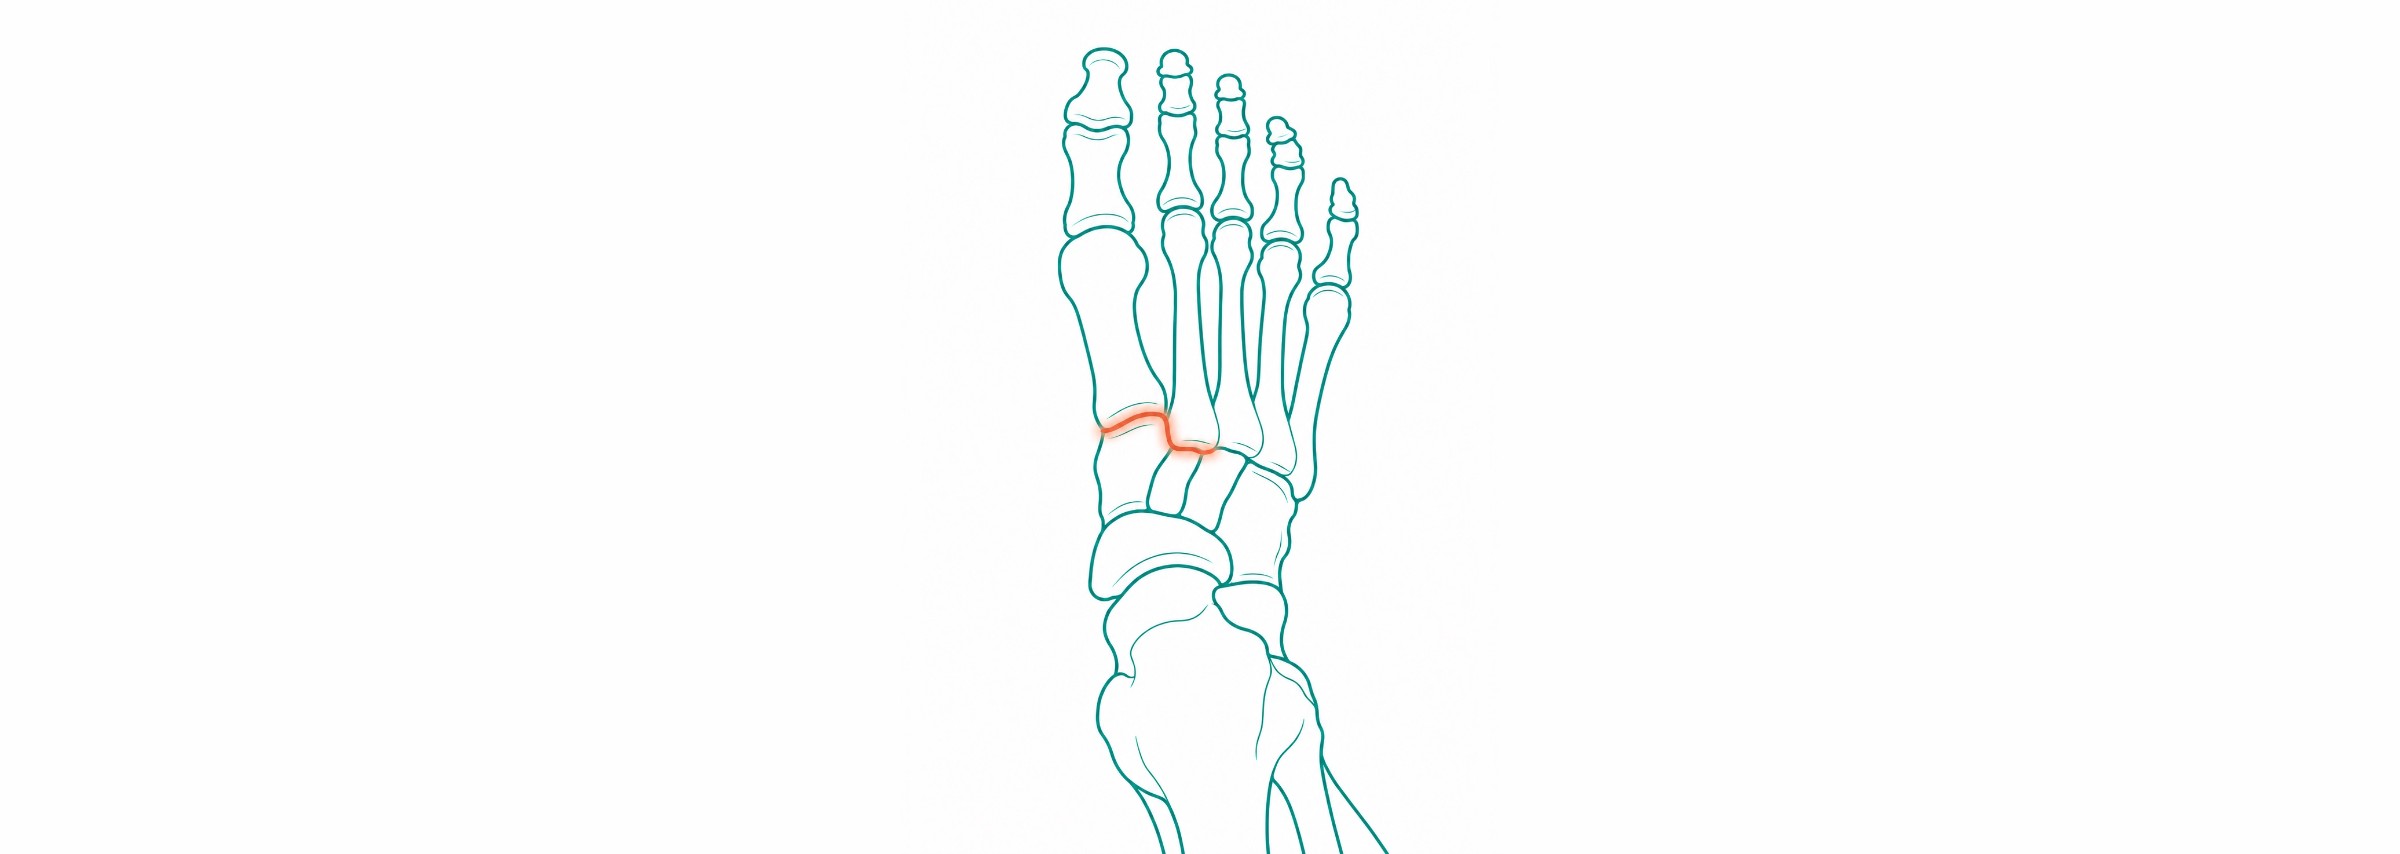
What is Lisfranc injury surgery?
The Lisfranc joint complex is in the middle of the foot (midfoot), where the five long bones of the foot (metatarsals) meet the small bones of the arch. These joints are called the tarsometatarsal joints. A strong ligament, the Lisfranc ligament, joins the base of the second metatarsal to the bone on the inner side of the arch (medial cuneiform) and helps hold the arch of the foot together. A Lisfranc injury is a sprain, fracture or dislocation of these joints. In one study it occurred in 14 in every 100,000 people each year, and only 31% of injuries were caused by high-energy trauma (PMID 31257042). In a national register of 2,084 injuries, the most common cause was a simple fall or trip (31%), and 39% of patients had surgery (PMID 39626601).
A thorough clinical examination by a specialist and modern imaging help confirm the diagnosis. These injuries can be subtle and are missed in about 20% of cases when people first present (PMID 27013521). CT scans, weight-bearing X-rays and sometimes MRI scans can show whether the joints have moved apart. Injuries that are stable, with no displacement, can often be treated without an operation in a boot or cast (PMID 30321929; PMID 36841140).
Surgery is considered when the joints are unstable or displaced. The aim is to put the bones back in their normal position (anatomical reduction) and hold them there while the ligaments and bones heal. This is usually done through one or more incisions on the top of the foot, using screws placed across the joints or plates that bridge the joints on their upper surface (open reduction and internal fixation) (PMID 11097452; PMID 35459613). Some injuries can be fixed through small incisions, with screws placed through the skin (percutaneous fixation) (PMID 30321929). Another option is to join (fuse) the injured inner joints so that they heal as one solid bone, called primary partial arthrodesis (PMID 16510816; PMID 39680239).
What are the benefits of Lisfranc injury surgery?
Restoring the normal position of the joints gives the best chance of a good long-term result. In a study of 48 patients followed for an average of 52 months after open reduction and screw fixation, anatomical reduction was the main factor linked with a good outcome, with less arthritis and better foot function scores (PMID 11097452). In a review of comparative studies, plates bridging the joints were associated with better foot function scores and less arthritis than screws across the joints (PMID 35459613).
Most people return to sport and physical activity. In a study of 33 recreational athletes treated with screws and bridge plates, 94% returned to some form of sport and 66% returned at or above their pre-injury level (PMID 29606024). In a review of 17 studies, 98% of people returned to sport after percutaneous fixation, 78% after open fixation and 85% after primary partial arthrodesis (PMID 30321929).
Fusion of the injured joints can give good function with fewer further operations. In a randomised trial of 41 patients with mainly ligament injuries, people treated with primary arthrodesis rated their activity level at 92% of their pre-injury level and had higher foot scores at two years (PMID 16510816). In another randomised trial, further operations were needed in 16.7% of patients after fusion (PMID 19796583), and in a review of 18 studies, arthritis of the midfoot was reported in 2.8% of patients after fusion (PMID 39680239).
What are the risks of Lisfranc injury surgery?
A Lisfranc injury can cause lasting problems even after successful surgery. In the study of 48 patients, 25% developed arthritis of the midfoot joints and six of them needed a fusion operation, and people with purely ligament injuries tended to have poorer results despite anatomical reduction (PMID 11097452). In the study of 33 athletes, 33% had some ongoing pain and 33% played less sport than before their injury (PMID 29606024).
Further surgery is common after fixation with screws or plates. Some surgeons routinely remove the screws or plates once the injury has healed. In a review of 18 studies, 64.1% of patients had a further operation after fixation, including planned hardware removal, compared with 17.6% after fusion. Unplanned reoperations occurred in 38.3% after fixation and 14.7% after fusion, and arthritis of the midfoot was reported in 17.3% after fixation (PMID 39680239). In a randomised trial, planned and unplanned further operations were needed in 78.6% of patients after fixation, without a difference in function between the groups (PMID 19796583). Another review found a higher risk of metalwork removal and later fusion after fixation, with similar overall complication rates (PMID 31103276). In a study of 61 patients whose screws were left in place, 19.7% had a failure of fixation within 12 months; older age was linked with loss of position, higher body weight with hardware failure, and diabetes with infection (PMID 30850094).
Fusion permanently stiffens the foot. Its long-term effects are largely unknown and may include arthritis in neighbouring joints, pain and the need for further surgery, especially in young and active people (PMID 39680239). In the same review, complications other than reoperation occurred in 10.6% of patients after fusion and 12.6% after fixation (PMID 39680239). Other possible problems include wound healing problems, nerve irritation causing numbness on the top of the foot, stiffness, swelling, a visible scar and the risks of the anaesthetic, which your anaesthetist will discuss with you.
Summary
Lisfranc injury surgery aims to restore the normal position of the midfoot joints and hold them steady while they heal, using screws, plates or, for some injuries, fusion of the injured joints. Many people return to sport and their usual activities, but ongoing pain, arthritis and further surgery are possible. Surgery is usually recommended when the expected benefits for you outweigh the risks. You should discuss your injury, your scans and your goals, including your work, sport and other activities, with your fracture surgeon so that you can consider the options and the indications for treatment together.
General information only. The information on this page is general in nature and does not replace individual medical advice. All surgery carries risks, and results vary between patients. Please discuss your own circumstances with your treating practitioner.